Skin Care During Pelvic and Vulval Radiation Therapy: Preventing Radiation Dermatitis

Dr Mathangi Radiation Oncology

Did you know? Up to 95% of patients receiving pelvic and vulval radiation therapy experience some degree of skin reaction, making Radiation dermatitis treatment an essential aspect of cancer care. Under the expert guidance of Dr Mathangi, Senior Consultant & In-charge of Radiation Oncology at Gleneagles Cancer Institute, Bangalore, you gain access to international best practices and compassionate care tailored for your unique needs.

What Is Radiation Dermatitis And Why Is It A Concern During Pelvic And Vulval Radiation Therapy?

Radiation dermatitis is a common side effect of radiotherapy, particularly in sensitive areas like the pelvis and vulva. It manifests as redness, irritation, peeling, and sometimes painful ulceration of the skin. If not managed proactively, radiation dermatitis can lead to discomfort, infection, treatment interruptions, and a diminished quality of life.

Dr Mathangi’s vast experience—treating more than 12,000 patients—ensures that each patient receives a personalized plan focused on pelvic radiation skin care and effective strategies for preventing and managing skin reactions.

How To Prevent And Manage Radiation Dermatitis During Pelvic And Vulval Radiation Therapy?

The key to effective radiation dermatitis treatment is early intervention, consistent skin care, and close monitoring. Here is a step-by-step guide recommended by Dr Mathangi for optimal outcomes:

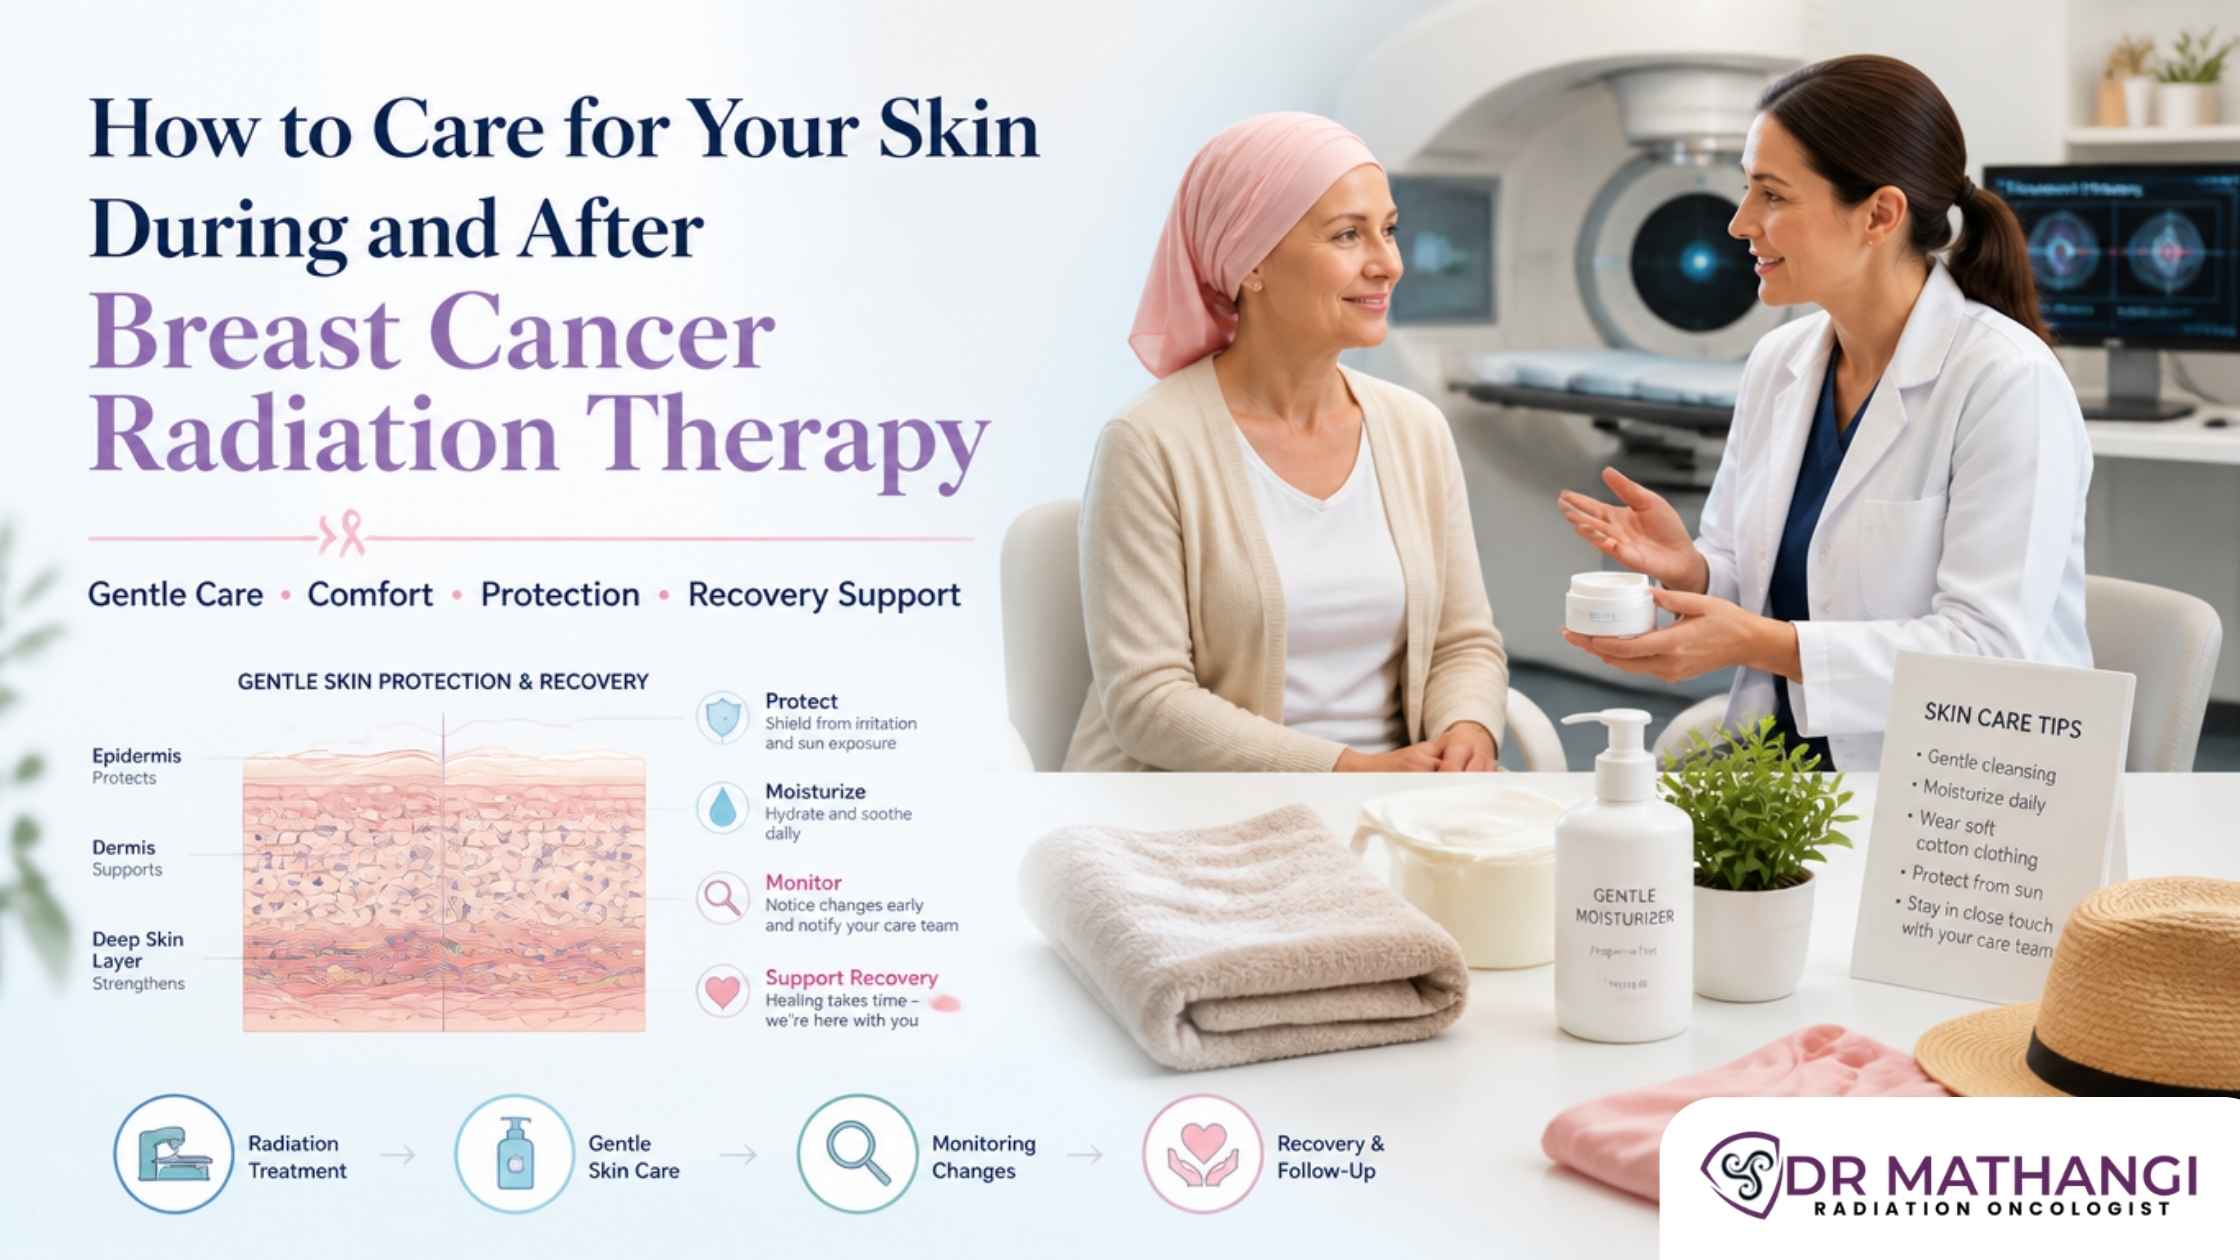
  1. Gentle cleansing: Use lukewarm water and mild, fragrance-free soap to clean the treated area. Avoid scrubbing or rubbing.
  2. Moisturization: Apply non-irritating, non-alcoholic moisturizers regularly. This forms a protective barrier and reduces dryness.
  3. Clothing: Wear loose, soft, and breathable garments—preferably cotton—to reduce friction and heat retention.
  4. Avoid irritants: Refrain from using talcum powders, perfumes, or harsh deodorants on the treatment area.
  5. Sun protection: Keep the area shielded from direct sunlight, as irradiated skin is more susceptible to burns.

Why Is Moist Desquamation Prevention Crucial?

Moist desquamation refers to the peeling and weeping of the skin, a severe form of radiation dermatitis. Preventing this condition is vital, as it can cause intense pain, secondary infections, and may force interruptions in radiation therapy.

  • Moist desquamation prevention strategies include early and regular skin assessments, using barrier creams, and implementing advanced wound care techniques as soon as any skin breakdown is detected.
  • Dr Mathangi utilizes global protocols and evidence-based techniques for early detection and intervention, ensuring that patients rarely progress to severe skin reactions.

What Role Do Hydrogel Dressings Play In Radiation Dermatitis Treatment?

Hydrogel dressings are highly effective in managing and soothing radiation-induced skin injuries. These dressings provide a moist healing environment, reduce pain, and accelerate skin regeneration.

  • They are non-adhesive and gentle, making them ideal for sensitive areas like the vulva and perineum.
  • Dr Mathangi recommends hydrogel dressings for both moist desquamation prevention and for active radiation skin burns treatment.

How Does Radiation Skin Burns Treatment Differ In Sensitive Areas?

Radiation skin burns treatment in the pelvic and vulval region requires special attention due to the high moisture, sensitivity, and risk of infection in these areas.

  1. Prompt wound care: Immediate management with gentle cleansing, followed by hydrogel or hydrocolloid dressings as guided by Dr Mathangi.
  2. Infection prevention: Use of topical antibiotics or antifungals if there are signs of infection.
  3. Pain control: Appropriate analgesics and topical anesthetics to manage discomfort.
  4. Ongoing assessment: Regular follow-ups and RTOG toxicity grading to monitor healing and adjust treatment as necessary.

What Is Vulval Radiation Care And Why Is It Specialized?

Vulval radiation care is a specialized aspect of oncology, as the skin in this area is extremely delicate and prone to rapid breakdown under radiation. Dr Mathangi’s unique expertise in vulval radiation care ensures:

  • Customized shielding and dose modulation to minimize skin exposure.
  • Rigorous skin care regimens, including barrier ointments and protective dressings.
  • Emotional and psychological support, addressing the sensitive nature of vulval cancers.

How Is RTOG Toxicity Grading Used To Monitor Skin Reactions?

RTOG toxicity grading is a standardized system used to assess and document the severity of radiation-induced skin reactions. This grading helps in tailoring interventions and ensuring patient safety.

RTOG Skin Toxicity Grading System
Grade Description
0 No change from baseline
1 Faint erythema or dry desquamation
2 Moderate to brisk erythema; patchy moist desquamation, mostly in skin folds
3 Confluent moist desquamation (not confined to skin folds); bleeding induced by minor trauma
4 Skin necrosis or ulceration of full thickness dermis; spontaneous bleeding

By employing RTOG toxicity grading during every follow-up, Dr Mathangi ensures that any skin reaction is detected early and treated with the most appropriate intervention.

Why Choose Dr Mathangi For Pelvic And Vulval Radiation Therapy?

Dr Mathangi is a leader in radiation oncology, renowned for her patient-centric approach and global training in advanced radiotherapy techniques. Her expertise covers a broad spectrum of cancers that need RT, including:

  • Head and neck cancers
  • Brain tumors
  • Spine tumors
  • Esophagus and rectal cancers
  • Lung cancers
  • Liver cancers
  • Breast cancers
  • Bladder cancers
  • Prostate cancers
  • Uterine cancers
  • Cervical cancer
  • Vulval cancers
  • Anal canal cancers
  • Penile cancers

Her advanced training in Stereotactic techniques, IGRT/RapidArc, and Intraoperative Radiotherapy (IORT) from renowned European centers translates to safer, more effective treatments for her patients in Bangalore and beyond.

How Do You Book A Consultation With Dr Mathangi?

If you or a loved one are undergoing pelvic or vulval radiation therapy, proactive skin care can make a world of difference. Don’t compromise your treatment outcomes or quality of life. Submit your contact information on the appointment form on Dr Mathangi’s website. Her dedicated team will promptly schedule your appointment and guide you through the next steps.

About Dr Mathangi

Dr Mathangi J is the Senior Consultant & In-charge of Radiation Oncology at Gleneagles Cancer Institute, Bangalore. With over 20 years of experience and more than 12,000 patients treated, she specializes in the treatment of complex cancers using cutting-edge technology. Her achievements include installing the first TrueBeam STx Machine in Asia Pacific and leading the Fellowship in Advanced Radiotherapy techniques at RGUHS. Dr Mathangi’s compassionate care, technical expertise, and commitment to patient well-being make her the preferred choice for advanced cancer therapy in South and North India.

Don’t wait until skin reactions disrupt your treatment. Choose the expert care of Dr Mathangi and experience the difference that world-class, patient-focused oncology can make.

Frequently Asked Questions

What is radiation dermatitis, and why does it occur during pelvic and vulval radiation therapy?

Radiation dermatitis is a skin reaction caused by exposure to radiation during cancer treatment, such as pelvic and vulval radiation therapy. It typically presents as redness, irritation, or peeling of the skin in the treated area. This occurs because radiation damages both cancerous and healthy skin cells, leading to inflammation and breakdown of the skin barrier. The sensitive nature of the pelvic and vulval regions makes them especially prone to these effects. Dr. Mathangi offers comprehensive radiation dermatitis treatment protocols to minimize discomfort and support skin healing throughout your therapy.

How can I take care of my skin during pelvic radiation to prevent severe reactions?

Pelvic radiation skin care is crucial for reducing the risk of severe skin reactions. Dr. Mathangi recommends gentle cleansing with lukewarm water, avoiding harsh soaps and scrubbing, patting the area dry, and wearing loose, breathable clothing. Moisturizing with approved, non-perfumed creams and following your oncologist’s instructions is essential. Early intervention and regular monitoring help prevent escalation of symptoms and ensure optimal skin health during therapy.

What is moist desquamation, and how can it be prevented during radiation therapy?

Moist desquamation refers to the breakdown of the top layer of skin, resulting in weeping, open, and sometimes painful areas. It is a common side effect in regions exposed to high doses of radiation, such as the vulva and pelvic area. Preventing moist desquamation involves proactive skin care—regular moisturization, early identification of skin changes, and the use of protective dressings. Dr. Mathangi emphasizes the importance of patient education and individualized skin care regimens to reduce the likelihood of this complication.

Are hydrogel dressings effective for managing radiation-induced skin issues?

Yes, hydrogel dressings are highly effective in managing radiation-induced skin reactions, especially when moist desquamation or open wounds occur. These dressings provide a moist environment that promotes healing, reduces pain, and protects the area from further trauma or infection. Dr. Mathangi often incorporates hydrogel dressings into her radiation skin burns treatment protocol to support faster and more comfortable recovery for her patients.

What are the recommended strategies for radiation skin burns treatment in the pelvic and vulval area?

Effective radiation skin burns treatment includes gentle cleansing, application of doctor-recommended moisturizers or barrier creams, and the use of advanced wound dressings like hydrogels when necessary. Pain relief, infection prevention, and close monitoring by your healthcare team are also key. Dr. Mathangi provides a tailored approach to ensure each patient receives the right combination of treatments based on their skin type and the severity of their reaction.

How should vulval skin be cared for during and after radiation therapy?

Vulval radiation care requires extra attention due to the sensitivity and moisture of the region. Dr. Mathangi advises gentle cleansing with water, avoiding irritants such as scented soaps, and wearing soft, loose undergarments. Moisturizers should be applied as prescribed, and patients should report any discomfort or changes to their care team promptly. Regular follow-up ensures any issues are addressed early, minimizing long-term skin problems.

What is RTOG toxicity grading, and how does it help in managing radiation dermatitis?

RTOG toxicity grading is a standardized scale used by oncologists to assess the severity of skin reactions during radiation therapy. It ranges from mild redness (Grade 1) to ulceration or necrosis (Grade 4). This grading helps clinicians, like Dr. Mathangi, to monitor progress, adjust treatment plans, and intervene appropriately to prevent worsening of skin toxicity. Accurate grading ensures each patient receives the most effective and timely care.

When should I contact Dr. Mathangi about skin changes during pelvic or vulval radiation?

You should contact Dr. Mathangi promptly if you notice increased redness, pain, blistering, open sores, or signs of infection in the treated area. Early intervention is key to effective radiation dermatitis treatment and preventing complications such as moist desquamation. Regular communication with your care team ensures the best possible outcomes throughout your radiation therapy journey.

What are some best practices for moist desquamation prevention during pelvic and vulval radiation therapy?

Moist desquamation prevention involves a combination of gentle skin care, early moisturization, avoiding friction and irritants, and using protective dressings as recommended by your care team. Dr. Mathangi encourages patients to start preventive measures before visible skin changes occur. Consistent follow-up, patient education, and adherence to a daily skin regimen are vital for effective moist desquamation prevention during radiation therapy to the pelvic and vulval regions.

Can my daily routine help with moist desquamation prevention?

Yes, your daily routine plays a significant role in moist desquamation prevention. Maintaining clean, dry, and moisturized skin, wearing loose clothing, and promptly reporting any new symptoms to your radiation oncology team can greatly reduce your risk. Dr. Mathangi recommends following all medical advice on skin care products and practices to maximize moist desquamation prevention during your treatment.
Concurrent Chemoradiation for Stage III NSCLC: Treatment Timeline and Expectations

Dr Mathangi J Radiation Oncologist Gleneagles Bangalore

Quick Answer: Concurrent chemoradiation for lung cancer, especially in stage III NSCLC, is a carefully coordinated treatment combining chemotherapy and radiotherapy, typically delivered over six to seven weeks. This approach offers the best chance at long-term control and survival, but requires expert management for optimal outcomes. Under the care of Dr Mathangi, a leading radiation oncologist in Bangalore, patients receive personalized treatment plans, state-of-the-art technology, and dedicated support—maximizing both safety and effectiveness.

Did you know that lung cancer remains the leading cause of cancer-related deaths worldwide, with non-small cell lung cancer (NSCLC) accounting for approximately 85% of cases? Stage III NSCLC treatment is particularly challenging, often requiring a multi-modal approach for the best outcomes. In this context, concurrent chemoradiation for lung cancer stands out as the standard of care for patients who are not immediate candidates for surgery. Yet, the complexity of combining chemotherapy and radiotherapy means that only the most experienced and skilled teams—like that led by Dr Mathangi at Gleneagles Cancer Institute, Bangalore—can deliver optimal results with the highest safety.

Don't compromise on your care.
To book a consultation with Dr Mathangi, visit this appointment form and our team will promptly schedule your visit.

What Is Concurrent Chemoradiation For Lung Cancer?

Concurrent chemoradiation for lung cancer refers to the simultaneous administration of chemotherapy and radiotherapy. This approach is especially pivotal in stage III NSCLC treatment, where the cancer is locally advanced but not suitable for immediate surgical resection. By delivering both treatments together, the cancer cells are attacked on multiple fronts:

  • Chemotherapy (such as the cisplatin etoposide radiation regimen) sensitizes tumor cells to radiation, increasing the likelihood of cell death.
  • Radiotherapy targets the tumor and involved lymph nodes, aiming for local control.
  • The combination has been shown to improve both progression-free and overall survival compared to sequential therapy.

Dr Mathangi emphasizes that concurrent chemoradiotherapy requires meticulous planning, advanced imaging, and precise delivery techniques to maximize benefits while minimizing side effects.

How Is Stage III NSCLC Treatment Planned?

Stage III NSCLC treatment is highly individualized. The planning process involves several critical steps:

  1. Comprehensive Staging: PET-CT and MRI scans to define the exact extent of disease.
  2. Multidisciplinary Team Review: Input from medical oncologists, radiation oncologists, pulmonologists, and radiologists.
  3. Personalized Protocol Selection: Factors such as patient health, tumor size, and location influence whether definitive radiotherapy for lung cancer with concurrent chemotherapy is chosen.
  4. Technology Integration: Advanced radiotherapy techniques like IGRT, RapidArc, and gated treatments are selected by Dr Mathangi for their precision.

Early and accurate planning is crucial for maximizing the chances of long-term control and minimizing risks.

What Is The Typical Treatment Timeline For Concurrent Chemoradiotherapy?

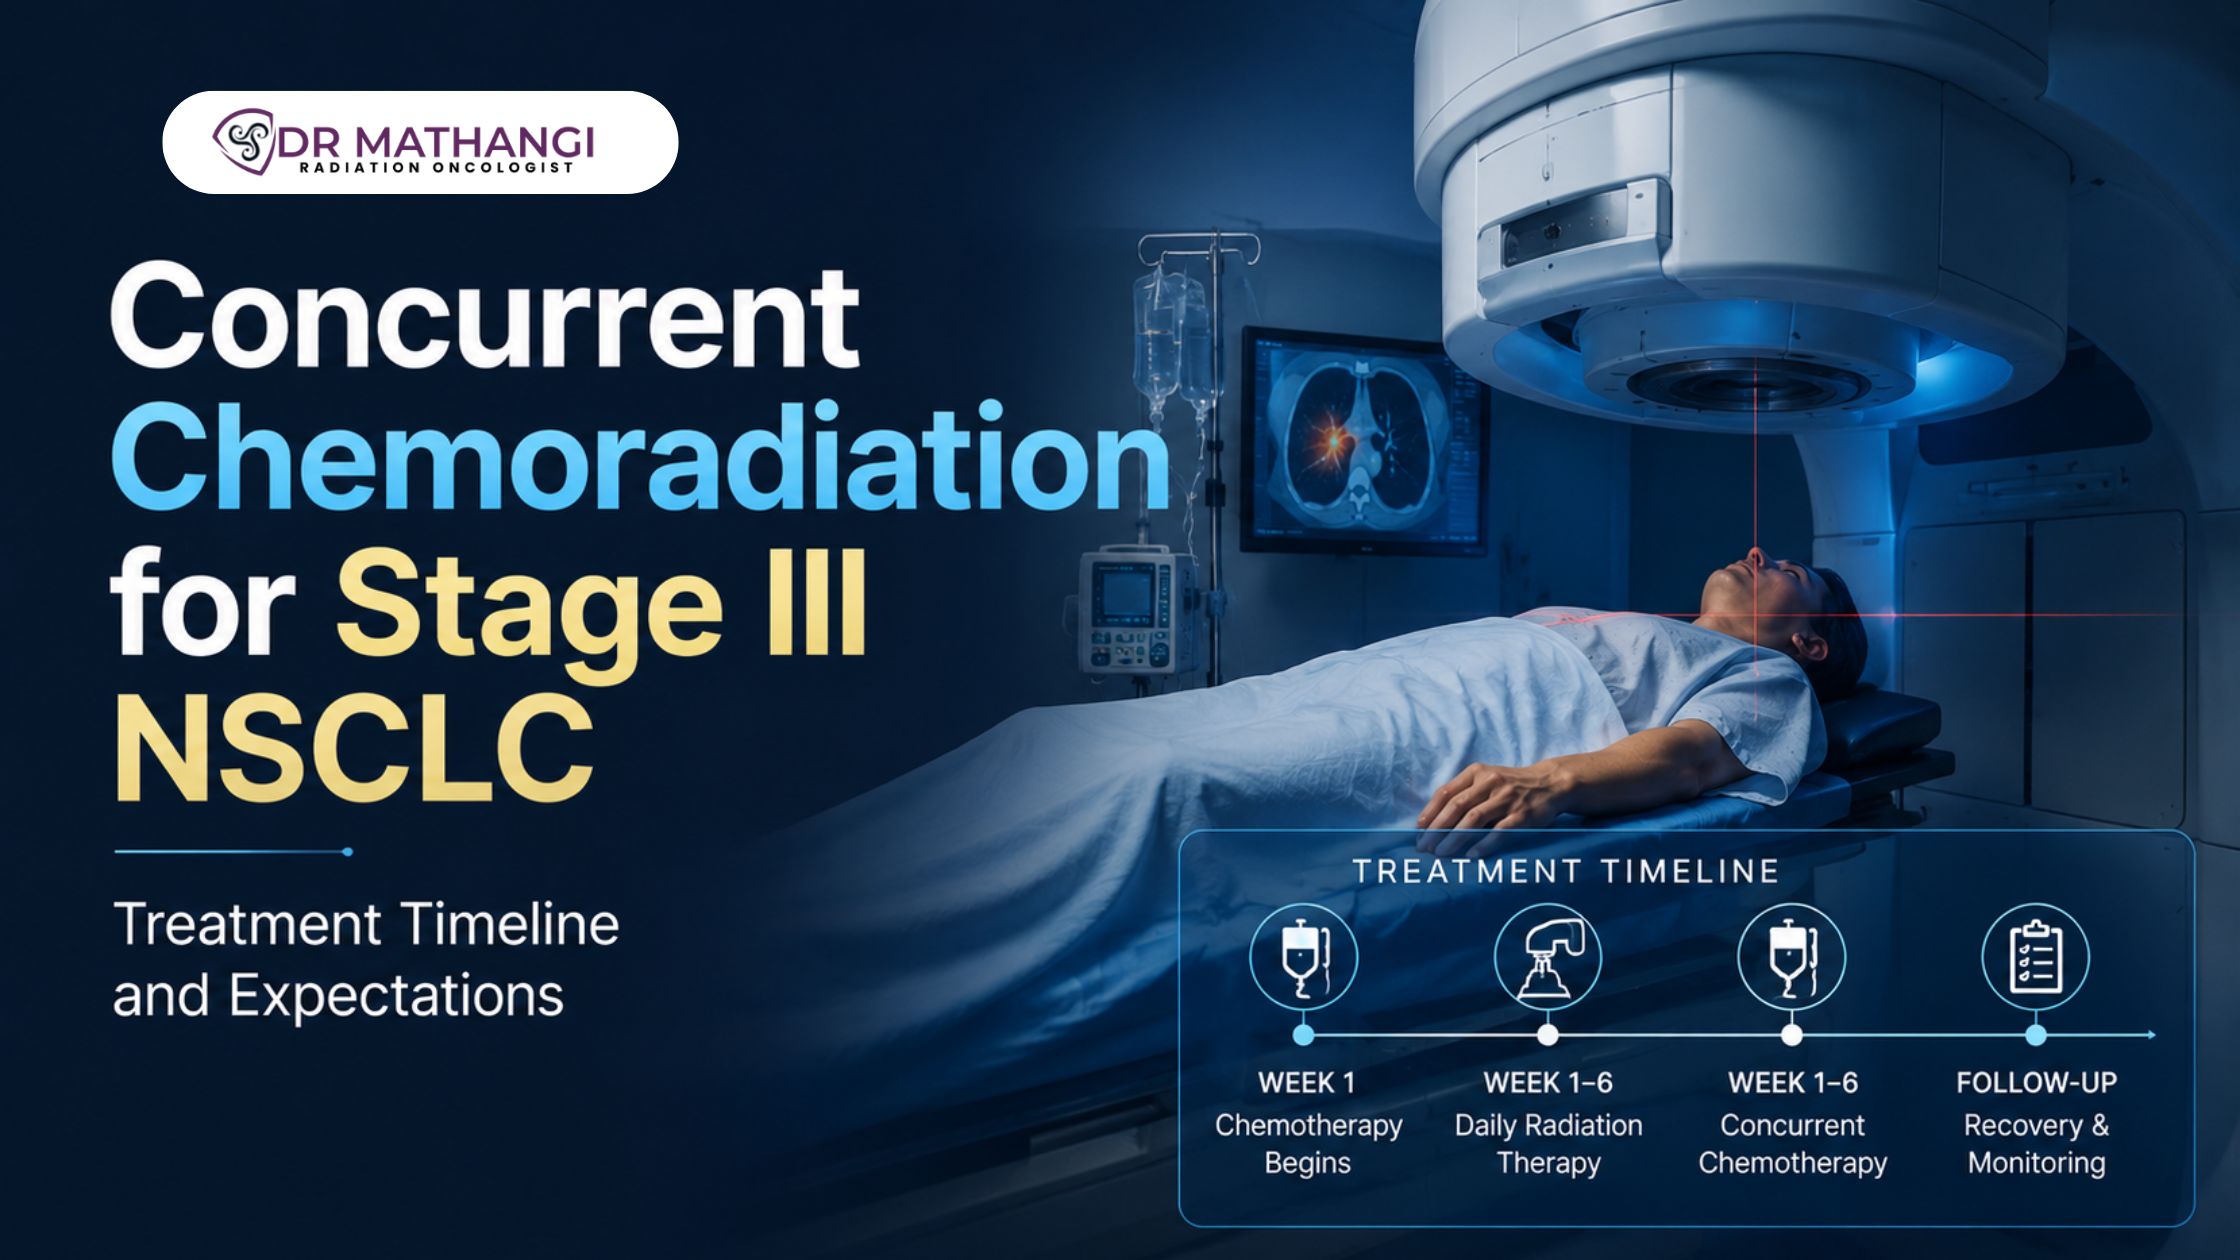
The standard timeline for concurrent chemoradiotherapy in stage III NSCLC is as follows:

  • Initial Evaluation & Simulation: 1-2 weeks (includes staging, baseline tests, mask/mold creation for radiotherapy).
  • Chemoradiation Phase: 6-7 weeks (daily radiotherapy, with chemotherapy administered on specific days).
  • Rest Period: 2-4 weeks post-chemoradiation (for patient recovery and reassessment).
  • Durvalumab Consolidation: Up to 12 months, as per eligibility and response (see below for details).
  • Follow-Up & Monitoring: Every 2-3 months in the first year, then at increasing intervals.

Sample Timeline Table

Phase Duration Activities
Evaluation 1-2 weeks Imaging, staging, planning, consent
Chemoradiation 6-7 weeks Daily radiotherapy, scheduled chemotherapy (e.g., cisplatin etoposide radiation)
Rest/Recovery 2-4 weeks Symptom management, labs, reassessment
Consolidation Up to 12 months Durvalumab immunotherapy (if indicated)
Follow-up Ongoing Imaging, clinical review, supportive care

What To Expect During Chemoradiation For Lung Cancer

Undergoing chemoradiation for lung cancer is a physically and emotionally demanding journey. Here is what you can expect:

  • Daily Radiotherapy Sessions: Typically 28-35 fractions over 6-7 weeks. Each session lasts about 15-20 minutes.
  • Chemotherapy Cycles: Administered concurrently, most often using cisplatin etoposide radiation regimen. Chemotherapy is delivered on specific days (usually weeks 1 and 5).
  • Regular Monitoring: Weekly blood tests, consultations, and toxicity assessments.
  • Side Effects Management: Fatigue, difficulty swallowing, cough, skin reactions, and lowered immunity are common but can be effectively managed by an experienced team.

Why Is Expertise Critical For Definitive Radiotherapy For Lung Cancer?

Definitive radiotherapy for lung cancer aims for cure, not just palliation. Achieving this goal depends on:

  • Technology: Dr Mathangi employs the latest tools—such as Stereotactic Ablative Body Radiotherapy (SBRT), Gated RapidArc, and DIBH gating—for precise dose delivery, sparing healthy tissue.
  • Experience: With over 20 years in the field and more than 12,000 patients treated, Dr Mathangi’s protocols are benchmarked to international standards.
  • Personalized Care: Each plan is tailored, factoring in patient comorbidities, tumor characteristics, and tolerance to treatment.
  • Continuous Monitoring: Early detection and management of complications, such as esophagitis or pneumonitis, are essential for safety and success.

Choosing the right oncologist can mean the difference between long-term remission and avoidable complications.

How Does The PACIFIC Trial Influence Modern Lung Cancer Care?

The PACIFIC trial revolutionized stage III NSCLC treatment by demonstrating that adding durvalumab consolidation immunotherapy after concurrent chemoradiotherapy significantly improves both disease-free and overall survival. The key findings were:

  • Durvalumab, a PD-L1 inhibitor, is given for up to one year following completion of chemoradiation.
  • Eligible patients see a notable reduction in the risk of recurrence and death.
  • This has become the new standard of care for patients without disease progression after chemoradiotherapy.

Dr Mathangi’s team ensures each patient is evaluated for durvalumab consolidation based on clinical and molecular criteria, offering access to the most advanced treatments in line with global best practices.

What Is The Role Of Cisplatin Etoposide Radiation In Concurrent Chemoradiotherapy?

The cisplatin etoposide radiation regimen remains a cornerstone in the concurrent treatment of stage III NSCLC. Here's why:

  • Cisplatin: A platinum-based chemotherapy that enhances the effectiveness of radiation on tumor cells.
  • Etoposide: Disrupts cancer cell DNA replication, working synergistically with cisplatin and radiotherapy.
  • Concurrent Use: This combination, given with radiotherapy, maximizes tumor kill but requires expert management due to potential side effects (nausea, low blood counts, etc.).

Dr Mathangi’s protocols incorporate pre-emptive supportive care, advanced antiemetics, and close monitoring, ensuring patients complete therapy with minimal interruptions.

Durvalumab Consolidation: The New Frontier In Stage III NSCLC

For patients who complete concurrent chemoradiotherapy without progression, durvalumab consolidation immunotherapy is now the gold standard. Key points:

  • Eligibility: Stable disease or better after chemoradiation, adequate organ function, and no autoimmune contraindications.
  • Administration: Intravenous infusion every 2 weeks, up to 12 months.
  • Benefits: Improved survival, reduced recurrence, minimal additional toxicity for most patients.

The integration of PACIFIC trial findings into routine practice at Gleneagles Cancer Institute under Dr Mathangi’s care places patients at the forefront of global oncology advances.

Why Choose Dr Mathangi For Concurrent Chemoradiation For Lung Cancer?

Dr Mathangi J is one of South India’s most accomplished radiation oncologists, offering unparalleled expertise in chemoradiation for lung cancer. Her credentials include:

  • Senior Consultant & In-charge of Radiation Oncology, Gleneagles Cancer Institute, Bangalore
  • Over 20 years of experience and 12,000+ successful cancer treatments
  • Advanced international training in Stereotactic techniques, IGRT, RapidArc, and IORT
  • Pioneering installation of Asia Pacific’s first TrueBeam STx Machine
  • Specialist in Head & Neck, Brain, Prostate, Lung, and Women’s Cancers
  • Director of Fellowship in Advanced Radiotherapy Techniques, RGUHS
  • Personalized care, evidence-based protocols, and a compassionate approach

Choosing Dr Mathangi means entrusting your care to one of India’s foremost experts, whose commitment to safety, innovation, and patient support is second to none.

Ready to take the next step?
Secure your expert consultation with Dr Mathangi by submitting your contact details here.

What Cancers Benefit Most From Advanced Radiotherapy?

According to Dr Mathangi, cancers that need RT (radiation therapy) include:

  • Head and neck cancers
  • Brain tumors
  • Spine tumors
  • Esophagus and rectal cancers
  • Lung cancers
  • Liver cancers
  • Breast cancers
  • Bladder cancers
  • Prostate cancers
  • Uterine cancers
  • Cervical cancer
  • Vulval cancers
  • Anal canal cancers
  • Penile cancers

About Dr Mathangi

Dr Mathangi J is a renowned Senior Radiation Oncologist and In-charge at Gleneagles Cancer Institute, Bangalore. With MBBS, DMRT, and DNB qualifications, and advanced training from leading institutes worldwide, her expertise in cutting-edge radiotherapy places her among India’s top cancer specialists. Her leadership, compassion, and patient-centric approach ensure that every patient receives world-class care tailored to individual needs.

For those seeking the best in concurrent chemoradiation for lung cancer, Dr Mathangi’s services are unmatched in both South and North India, with patients traveling from across the country for her expert care.

Frequently Asked Questions

What is concurrent chemoradiation for lung cancer and why is it preferred for stage III NSCLC?

Concurrent chemoradiation for lung cancer refers to the simultaneous administration of chemotherapy and radiotherapy. For patients with stage III NSCLC treatment, this approach maximizes the effectiveness of both therapies, as chemotherapy can sensitize tumor cells to radiation. Dr. Mathangi recommends this for eligible patients because studies show it improves local control and overall survival compared to sequential treatment, especially when definitive radiotherapy for lung cancer is indicated.

What is the typical treatment timeline for concurrent chemoradiotherapy in stage III NSCLC?

The standard timeline for concurrent chemoradiotherapy usually spans about 6-7 weeks. Chemotherapy cycles, such as cisplatin etoposide radiation, are coordinated with daily radiation sessions (Monday to Friday). After completing chemoradiation, many patients are evaluated for further therapies like durvalumab consolidation, depending on their response and tolerability.

What can I expect during the chemoradiation phase in terms of side effects and support?

Common side effects during concurrent chemoradiotherapy include fatigue, skin changes, difficulty swallowing, cough, mild fever, or changes in blood counts. Dr. Mathangi and her multidisciplinary team offer extensive support with symptom management, nutritional counseling, and regular monitoring to ensure safety and comfort throughout the stage III NSCLC treatment process.

How do cisplatin etoposide and radiation therapy work together in this setting?

Cisplatin and etoposide are chemotherapy agents that not only attack cancer cells, but also make them more sensitive to radiation damage. Radiation therapy targets the tumor and regional lymph nodes with precise doses. Administering these together, as Dr. Mathangi does, increases the effectiveness of definitive radiotherapy for lung cancer while aiming to control the cancer locally and prevent spread.

What is durvalumab consolidation and when is it recommended after chemoradiation?

Durvalumab consolidation is an immunotherapy given after successful completion of concurrent chemoradiation for lung cancer, provided there is no progression or significant residual toxicity. Based on results from the PACIFIC trial, Dr. Mathangi often recommends durvalumab for up to 12 months to further reduce the risk of recurrence and improve long-term outcomes in eligible patients.

What role did the PACIFIC trial play in changing the standard of care for stage III NSCLC?

The PACIFIC trial was a landmark study that showed adding durvalumab consolidation after concurrent chemoradiotherapy significantly improved survival for patients with stage III NSCLC. As a result, this approach is now the standard of care, and Dr. Mathangi incorporates it into her treatment protocols for suitable patients.

How is treatment response monitored during and after concurrent chemoradiation for lung cancer?

Dr. Mathangi utilizes periodic physical exams, blood tests, and imaging studies (like CT or PET scans) to monitor treatment response and side effects. After chemoradiation for lung cancer, follow-up visits are scheduled to assess recovery, detect any early signs of recurrence, and determine eligibility for durvalumab consolidation.

What are the main goals of definitive radiotherapy for lung cancer in stage III NSCLC?

The primary goal of definitive radiotherapy for lung cancer is to achieve maximum tumor control in the chest, reduce cancer spread, and improve survival. For stage III NSCLC treatment, combining this with chemotherapy and, if eligible, durvalumab consolidation, offers the best chance for long-term remission according to current evidence and Dr. Mathangi’s clinical practice.


SRS vs Surgery for Brain Metastases: Choosing the Right Treatment

Quick Answer: When considering SRS for brain metastases versus traditional surgery, the choice depends on tumor size, location, patient health, and desired outcomes like neurocognitive preservation. Stereotactic radiosurgery (SRS) offers a non-invasive approach with high intracranial control rates, while surgical resection for brain metastasis may be preferred for larger or symptomatic tumors. Consult with an expert, such as Dr Mathangi J at Gleneagles Cancer Institute, for personalized guidance.

What Is SRS For Brain Metastases And How Does It Work?

SRS for brain metastases, or stereotactic radiosurgery, is a highly precise, non-invasive radiation therapy technique used to treat cancerous tumors that have spread to the brain. With up to 30% of adults with cancer developing brain metastases during their illness, according to leading oncology research, timely and accurate treatment is vital for survival and quality of life.

  • Precision: SRS delivers focused, high-dose radiation beams to the tumor, sparing surrounding healthy tissue.
  • Non-invasive: No incisions; the procedure is often completed in a single outpatient session.
  • Rapid Recovery: Minimal downtime, with most patients resuming normal activities within a day or two.

Dr Mathangi J, Senior Consultant & In-charge of Radiation Oncology at Gleneagles Cancer Institute, Bangalore, specializes in advanced SRS techniques, ensuring optimal outcomes for patients with brain metastases.

How Does Stereotactic Radiosurgery Compare With Surgical Resection For Brain Metastasis?

In brief: Stereotactic radiosurgery is best for small to medium-sized tumors and patients seeking non-invasive treatment, while surgical resection for brain metastasis is often preferred for larger, accessible tumors causing significant symptoms or requiring rapid relief of intracranial pressure.

Comparison: SRS For Brain Metastases vs Surgical Resection For Brain Metastasis
Factor SRS (Stereotactic Radiosurgery) Surgery (Surgical Resection)
Invasiveness Non-invasive Invasive (requires craniotomy)
Ideal Tumor Size <3-4 cm >3-4 cm or symptomatic
Hospital Stay Outpatient/Same day 2–7 days
Neurocognitive Preservation Excellent Variable (depends on tumor location)
Immediate Symptom Relief No Yes
Intracranial Control Rates High for small/medium tumors High for single, large tumors

By leveraging her advanced training from renowned institutions in Germany and Denmark, Dr Mathangi ensures each patient receives a tailored approach, maximizing the benefits of both options as appropriate.

What Are Gamma Knife Alternatives For Treating Brain Metastases?

Gamma knife alternatives like TrueBeam STx, CyberKnife, and other linear accelerator-based SRS platforms are revolutionizing treatment. These systems match or surpass gamma knife in accuracy, while offering greater flexibility in treating multiple or irregularly shaped tumors.

  • TrueBeam STx: First in Asia Pacific installed by Dr Mathangi's team, enables dynamic beam shaping and rapid treatment delivery.
  • CyberKnife: Robotic arm delivers radiation from hundreds of angles, ideal for challenging locations.
  • LINAC-based SRS: Versatile, widely available, and often cost-effective.

Dr Mathangi’s expertise in these gamma knife alternatives ensures that patients at Gleneagles Cancer Institute receive world-class care with access to the best technology available today.

Why Is Neurocognitive Preservation Important In Brain Metastases Treatment?

Neurocognitive preservation refers to protecting patients’ memory, attention, and executive function during cancer treatment. SRS for brain metastases, as practiced by Dr Mathangi, is designed to minimize radiation exposure to healthy brain tissue, significantly reducing the risk of long-term cognitive decline.

  • Selective targeting: SRS focuses only on tumor tissue, sparing vital brain regions involved in cognition.
  • Contrast with whole brain radiotherapy: Traditional whole brain radiotherapy (WBRT) exposes the entire brain to radiation, increasing neurocognitive side effects.
  • Quality of life: Preserved cognition translates to better independence and emotional well-being.

Neurocognitive preservation is now a cornerstone of modern cancer care, and Dr Mathangi’s advanced protocols set new standards in the region.

How Do Intracranial Control Rates Differ Between SRS And Surgery?

Intracranial control rates refer to the effectiveness of a treatment in preventing tumor recurrence or growth within the brain. For patients with a limited number of metastases (typically 1–4), SRS for brain metastases offers control rates comparable to surgical resection for brain metastasis, especially for tumors less than 3 cm.

  • SRS: Up to 85-90% local control at 1 year for small lesions.
  • Surgery: Excellent local control for larger, solitary tumors, especially when followed by SRS to the surgical cavity.
  • Combined Approach: Surgery plus adjuvant SRS yields the best results for select patients, particularly when immediate symptom relief is needed.

With Dr Mathangi’s multidisciplinary team, patients get individualized plans to achieve the highest possible intracranial control rates.

What Are Whole Brain Radiotherapy Alternatives And When Are They Preferred?

Whole brain radiotherapy alternatives such as SRS, fractionated stereotactic radiotherapy (FSRT), and hippocampal-sparing techniques are now preferred for most patients with a limited number of brain metastases.

  • SRS: Standard of care for up to 10 metastases, avoids cognitive side effects of WBRT.
  • FSRT: Used for larger tumors or those close to critical structures.
  • Hippocampal-sparing WBRT: When WBRT is necessary, sparing the hippocampus can help preserve memory.

Dr Mathangi’s center is a pioneer in offering these whole brain radiotherapy alternatives, supporting better long-term outcomes and quality of life.

How To Choose The Right Treatment For Brain Metastases?

Choosing the right treatment for brain metastases involves evaluating:

  • Number, size, and location of metastases
  • Patient’s overall health and neurological status
  • Primary cancer type and systemic disease control
  • Previous treatments and patient preferences
  • Desire for neurocognitive preservation

Dr Mathangi employs advanced imaging, multidisciplinary evaluation, and evidence-based protocols to tailor the best approach for each patient—whether SRS for brain metastases, surgical resection for brain metastasis, or a combination strategy.

Why Choose Dr Mathangi For SRS Or Surgery For Brain Metastases In Bangalore?

  • Experience: Over 20 years, 12,000+ patients successfully treated
  • Expertise: Advanced training in stereotactic radiosurgery, IGRT, RapidArc, and more
  • Technology: Asia Pacific’s first TrueBeam STx, latest in gamma knife alternatives
  • Comprehensive Care: Dedicated neuro-oncology team, holistic patient support
  • Personalized Plans: Every case is reviewed in detail to optimize outcomes and neurocognitive preservation

Dr Mathangi J leads Gleneagles Cancer Institute’s Radiation Oncology Department in Bangalore, recognized as a leading center for cancer care in South India and beyond.

About Dr Mathangi

Dr. Mathangi J is a Senior Consultant and In-charge of Radiation Oncology at Gleneagles Cancer Institute, Bangalore. With credentials from Madras Medical College, Apollo Cancer Specialty Hospital, and advanced international fellowships, she is an expert in SRS for brain metastases, gamma knife alternatives, and neuro-oncology. Her focus on evidence-based, patient-centered care has earned her a reputation as one of the most trusted cancer specialists in India.

To book an appointment, submit your contact details here. Dr Mathangi’s team will schedule your consultation and notify you promptly.

Gleneagles Cancer Institute, Bangalore — Your partner in advanced cancer care.
Facebook | Instagram


Frequently Asked Questions

What are the main differences between SRS for brain metastases and surgical resection?

SRS for brain metastases (Stereotactic Radiosurgery) is a non-invasive treatment that uses focused radiation to target tumors with high precision, while surgical resection for brain metastasis involves physically removing the tumor through an operation. SRS is often preferred for smaller, well-defined lesions or when surgery poses higher risks, while surgery may be chosen for large or symptomatic tumors causing mass effect. Dr. Mathangi offers both options and will recommend the most appropriate approach based on individual patient factors.

When is stereotactic radiosurgery preferred over surgery for brain metastases?

Stereotactic radiosurgery is typically preferred for patients with a limited number of small brain metastases, especially when the tumors are in locations that are difficult or risky to access surgically. It is also suitable for patients who may not tolerate surgery due to other medical conditions. Dr. Mathangi carefully assesses each patient’s situation to recommend SRS as an effective and minimally invasive option when appropriate.

What are the gamma knife alternatives available for treating brain metastases?

Gamma Knife is a popular form of SRS, but there are several gamma knife alternatives, including CyberKnife and advanced linear accelerator-based systems. These technologies also deliver high-dose, targeted radiation and can be used for a variety of brain metastases. Dr. Mathangi’s practice offers access to the latest stereotactic radiosurgery platforms, allowing for personalized treatment plans tailored to patient needs and tumor characteristics.

How do SRS and surgery compare in terms of neurocognitive preservation?

Neurocognitive preservation is an important consideration when choosing a treatment. SRS for brain metastases is generally associated with a lower risk of cognitive decline compared to whole brain radiotherapy and may also reduce risks compared to surgery for tumors located near critical brain regions. Surgical resection may be more impactful for larger or symptomatic tumors but can carry higher risks of affecting cognitive function depending on tumor location. Dr. Mathangi prioritizes treatments that maximize tumor control while minimizing neurocognitive impact.

What determines the intracranial control rates for these treatments?

Intracranial control rates are influenced by factors such as the number, size, and location of metastases, as well as the type of primary cancer. Both SRS and surgery offer high local control rates for appropriately selected patients. Combining surgery with adjuvant SRS to the surgical cavity can further improve control. Dr. Mathangi uses evidence-based protocols to optimize intracranial control rates and patient outcomes.

Are there whole brain radiotherapy alternatives for patients concerned about cognitive side effects?

Yes, there are whole brain radiotherapy alternatives such as SRS for brain metastases or focused treatments like hippocampal-sparing techniques. These approaches aim to control tumor growth while minimizing exposure to healthy brain tissue and thereby preserve cognitive function. Dr. Mathangi specializes in offering these advanced alternatives to ensure the best possible quality of life for her patients.

How does Dr. Mathangi help patients choose between surgery and SRS for brain metastases?

Dr. Mathangi conducts a thorough evaluation, including imaging, neurological assessment, and a review of overall health and treatment goals. She discusses the risks, benefits, and expected outcomes of both surgical resection for brain metastasis and stereotactic radiosurgery, guiding patients and their families to make informed decisions that align with their preferences and clinical needs.

Can multiple brain metastases be treated with SRS?

Yes, recent advances in technology allow SRS for brain metastases to be used for patients with multiple lesions, not just single or limited metastases. Dr. Mathangi uses state-of-the-art systems capable of treating several tumors in a single session, offering patients an effective, non-invasive alternative to whole brain radiotherapy.

What is the recovery like after SRS or surgical resection for brain metastasis?

Recovery after SRS is typically quick, with most patients resuming normal activities within a day or two. There may be mild headaches or fatigue, but serious side effects are rare. Surgical resection for brain metastasis involves a hospital stay and a longer recovery period, depending on the complexity of the surgery and overall health. Dr. Mathangi provides comprehensive support and follow-up care for both treatment options.


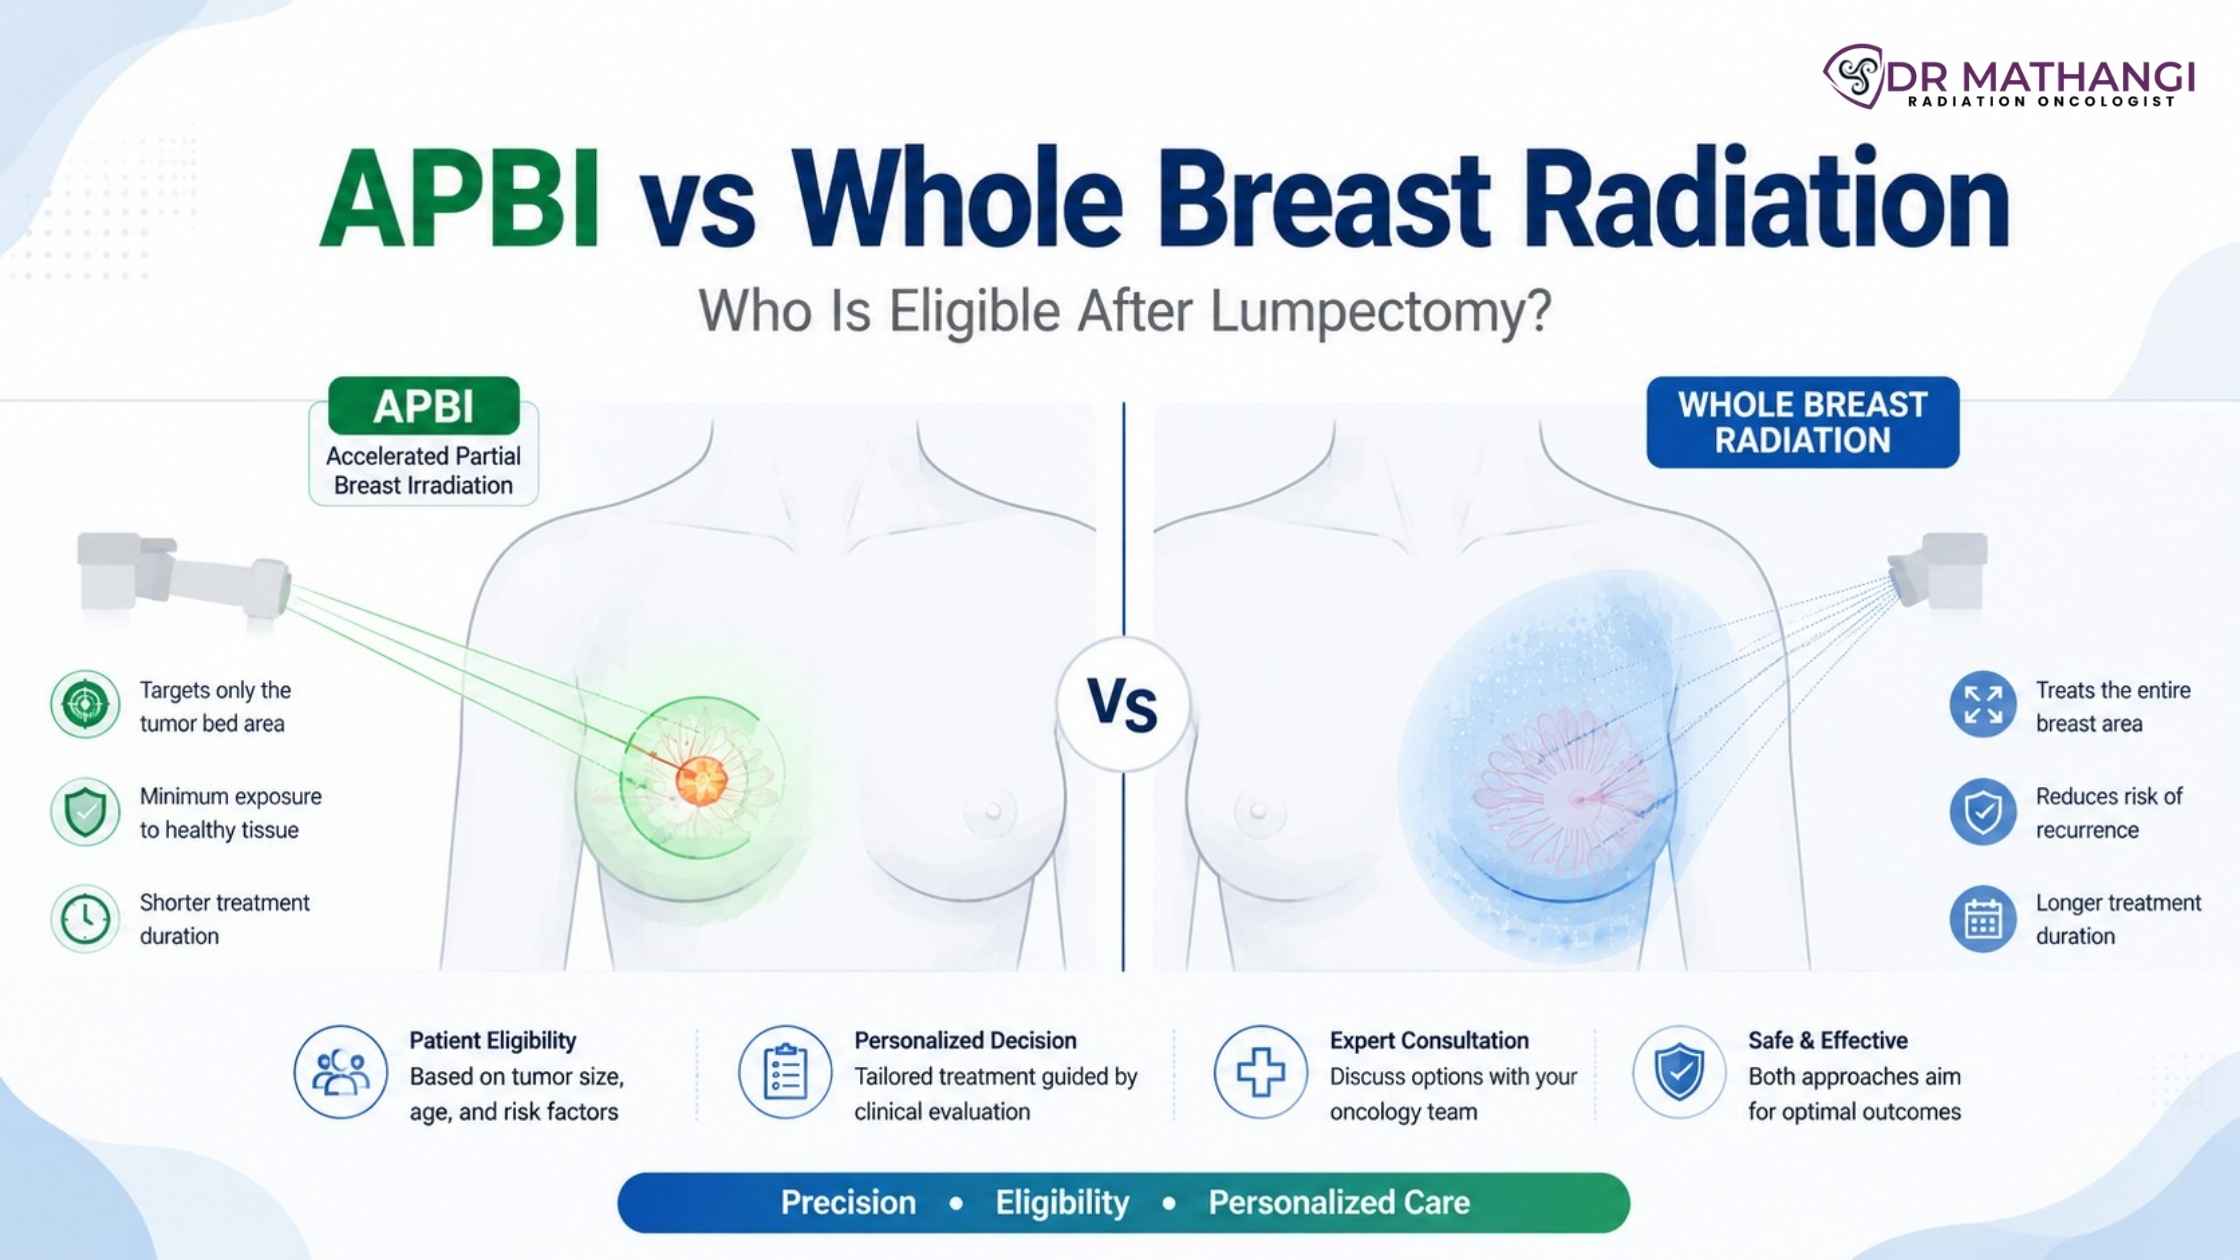
APBI vs Whole Breast Radiation After Lumpectomy: Who Is Eligible?

What Is The Difference Between APBI And Whole Breast Radiation?

APBI vs whole breast radiation is a crucial consideration for patients who have undergone a lumpectomy for breast cancer. According to recent studies, nearly 70% of early-stage breast cancer patients are eligible for breast-conserving surgery, making post-lumpectomy radiation therapy decisions highly relevant. In this comprehensive guide, Dr. Mathangi J, Senior Consultant & In-charge - Radiation Oncology at Gleneagles Cancer Institute, Bangalore, unravels the nuances of these two approaches, ensuring you are empowered to make the best choice for your health and future.

Why Is Post-Lumpectomy Radiation Important?

After a successful lumpectomy, radiation therapy is essential to eliminate any microscopic cancer cells that may remain in the breast tissue, thereby reducing the risk of recurrence. Standard options include whole breast radiation (WBRT) and accelerated partial breast irradiation (APBI). The choice between these two can significantly influence your treatment experience, recovery time, and long-term outcomes.

How Does APBI Work Compared To Whole Breast Radiation?

APBI targets only the area surrounding the original tumor site—the most common area for recurrence—while WBRT treats the entire breast. APBI delivers a higher dose of radiation over a shorter period (typically 5-10 days), whereas WBRT can take 3-6 weeks. For patients who meet specific eligibility criteria, APBI may offer cosmetic outcomes that are as good as or better than WBRT, with fewer side effects and greater convenience.

What Is Accelerated Partial Breast Irradiation (APBI)?

Accelerated partial breast irradiation is a form of lumpectomy radiation in which only a portion of the breast (where the tumor was removed) is treated. This approach is tailored for women with early-stage, low-risk breast cancer. APBI can be delivered using techniques such as:

  • Interstitial brachytherapy (placing radioactive sources in the tissue)
  • Intracavitary brachytherapy (using a balloon catheter in the lumpectomy cavity)
  • External beam radiation therapy (EBRT)

Dr. Mathangi is a leader in image-guided interstitial brachytherapy, offering her patients precise and highly effective APBI solutions.

What Is Whole Breast Radiation?

Whole breast radiation (WBRT) involves treating the entire breast, typically over 3-6 weeks. This method is suitable for a broader range of patients, including those with higher-risk features or larger tumors. In recent years, hypofractionated breast radiotherapy—which delivers higher doses per session over a shorter time (usually 3 weeks)—has become the standard of care in many settings due to similar efficacy and improved convenience.

Who Is Eligible For APBI Vs Whole Breast Radiation?

The ASTRO guidelines provide a framework for determining eligibility for APBI vs whole breast radiation. The ideal candidates for APBI are:

  • Age 50 years or older
  • Invasive ductal carcinoma or ductal carcinoma in situ (DCIS) ≤ 3 cm
  • Node-negative disease (no cancer in lymph nodes)
  • Clear surgical margins (no cancer cells at the edge of the tissue removed)
  • No extensive lymphovascular invasion
  • Unifocal disease (single tumor, not multiple sites in the breast)

Patients who do not meet these criteria are generally advised to undergo WBRT, which remains the gold standard for many, especially those with higher-risk features. Dr. Mathangi meticulously evaluates each patient’s pathology, imaging, and clinical profile to ensure the safest and most effective treatment pathway.

What Are The Cosmetic Outcomes And Side Effects?

Cosmetic outcomes are a top priority, especially for women seeking breast conservation therapy. APBI is associated with:

  • Less skin darkening and thickening
  • Lower risk of breast shrinkage and fibrosis
  • Similar or improved breast appearance compared to WBRT

WBRT, especially with modern techniques like deep inspiration breath-hold and prone positioning, also achieves excellent cosmetic results. Dr. Mathangi utilizes advanced technologies such as TrueBeam STx and gated RapidArc to minimize exposure of healthy tissues, further optimizing outcomes.

How Do ASTRO Guidelines Influence Treatment Choices?

The ASTRO guidelines (American Society for Radiation Oncology) are widely accepted by oncology professionals and form the basis of evidence-based decision-making in lumpectomy radiation. They stratify patients into "suitable," "cautionary," and "unsuitable" groups for APBI, considering factors such as age, tumor type, and margin status. Dr. Mathangi strictly adheres to these guidelines while adding her two decades of clinical experience to personalize recommendations for each patient.

Why Choose Dr Mathangi For Breast Cancer Radiation Therapy?

Dr. Mathangi J is renowned for her expertise in radiation oncology, having treated over 12,000 patients with cutting-edge techniques. Her credentials include advanced fellowships in stereotactic and image-guided radiotherapy from leading centers in Europe. At Gleneagles Cancer Institute, she offers the entire spectrum of radiation therapy for breast cancer, including:

  • APBI and WBRT
  • Hypofractionated breast radiotherapy
  • Image-guided interstitial brachytherapy
  • Intraoperative radiotherapy (IORT)

Her approach is patient-centric, focusing on minimizing side effects, enhancing cosmetic outcomes, and ensuring the highest standards of safety and effectiveness. Dr. Mathangi’s patients benefit from personalized counseling, state-of-the-art technology, and a compassionate team dedicated to supporting you through every step of your breast conservation therapy journey.

How To Book An Appointment With Dr Mathangi?

Don’t let uncertainty or delay impact your health and quality of life. If you or a loved one is considering APBI vs whole breast radiation after lumpectomy, schedule a consultation with Dr. Mathangi today. Simply submit your contact information using the appointment form on her website, and her team will promptly schedule your session and notify you.

About Dr Mathangi

Dr. Mathangi J is a Senior Consultant and In-charge of Radiation Oncology at Gleneagles Cancer Institute, Bangalore. With over 20 years of experience and 12,000+ patients treated, she is a leader in advanced radiotherapy for a wide range of cancers, including breast, head and neck, brain, lung, prostate, and gynecologic cancers. She is a pioneer in bringing Asia Pacific’s first TrueBeam STx machine to India and heads the fellowship in advanced radiotherapy techniques at her center. Her commitment to clinical excellence, patient safety, and compassionate care makes her the preferred choice for cancer patients in South and North India.

What Are The Cancers That Need Radiation Therapy?

According to Dr. Mathangi, the following cancers often require radiation therapy as part of their treatment protocol:

  • Head and neck cancers
  • Brain tumors
  • Spine tumors
  • Esophagus and rectal cancers
  • Lung cancers
  • Liver cancers
  • Breast cancers
  • Bladder cancers
  • Prostate cancers
  • Uterine cancers
  • Cervical cancer
  • Vulval cancers
  • Anal canal cancers
  • Penile cancers

For each of these cancers, Dr. Mathangi develops personalized, evidence-based treatment plans, ensuring the highest standards of care using the latest radiotherapy technologies.

Frequently Asked Questions

What is the difference between APBI and whole breast radiation after lumpectomy?

The main difference is the area of the breast treated with radiation. In APBI vs whole breast radiation, APBI (Accelerated Partial Breast Irradiation) targets only the area around where the tumor was removed, while whole breast radiation treats the entire breast. APBI is delivered over a shorter time, and may be suitable for select patients after lumpectomy.

Who is eligible for accelerated partial breast irradiation (APBI) after lumpectomy?

Eligibility for accelerated partial breast irradiation is determined by factors such as age, tumor size, margins, and lymph node status. According to ASTRO guidelines, APBI is generally recommended for women aged 50 or older with early-stage, low-risk breast cancer, negative margins, and no lymph node involvement. Dr. Mathangi evaluates each patient individually to ensure the best approach for breast conservation therapy.

What are the benefits of hypofractionated breast radiotherapy?

Hypofractionated breast radiotherapy delivers a higher dose of radiation per session over a shorter period compared to conventional schedules. Benefits include convenience, reduced treatment time, and similar efficacy and safety profiles. Dr. Mathangi uses evidence-based protocols to offer hypofractionated breast radiotherapy for eligible patients after lumpectomy radiation.

How do ASTRO guidelines impact the choice between APBI and whole breast radiation?

ASTRO guidelines provide evidence-based recommendations on which patients are suitable for APBI vs whole breast radiation. These guidelines consider tumor characteristics, age, and surgical factors to ensure optimal outcomes. Dr. Mathangi follows these standards to personalize lumpectomy radiation plans and maximize safety and effectiveness for her patients.

Are cosmetic outcomes better with APBI compared to whole breast radiation?

Cosmetic outcomes can be excellent with both approaches, but many studies show that APBI may lead to slightly better cosmetic outcomes due to the smaller treated area and lower overall dose to healthy tissue. Dr. Mathangi discusses potential cosmetic outcomes with each patient as part of her breast conservation therapy consultations.

What is the typical duration of APBI and whole breast radiation treatments?

APBI is usually completed in 5 to 10 days, while hypofractionated whole breast radiation typically takes 3 to 4 weeks. Traditional whole breast radiation may take up to 6 weeks. Dr. Mathangi offers tailored schedules to minimize disruption to your daily life while ensuring effective cancer control.

Can lumpectomy radiation be omitted if APBI is used?

No, APBI is a form of lumpectomy radiation. It is not an omission of radiation, but a targeted way to deliver it. Radiation after lumpectomy—whether APBI or whole breast—is an important part of breast conservation therapy to reduce recurrence risk. Dr. Mathangi helps patients understand the role of each modality in their treatment plan.

How does Dr. Mathangi help patients choose between APBI and whole breast radiation?

Dr. Mathangi carefully reviews your pathology, imaging, and personal preferences. She discusses the pros and cons of APBI vs whole breast radiation, referencing ASTRO guidelines and the latest research. Her patient-centered approach ensures you receive safe, effective, and individualized breast conservation therapy.


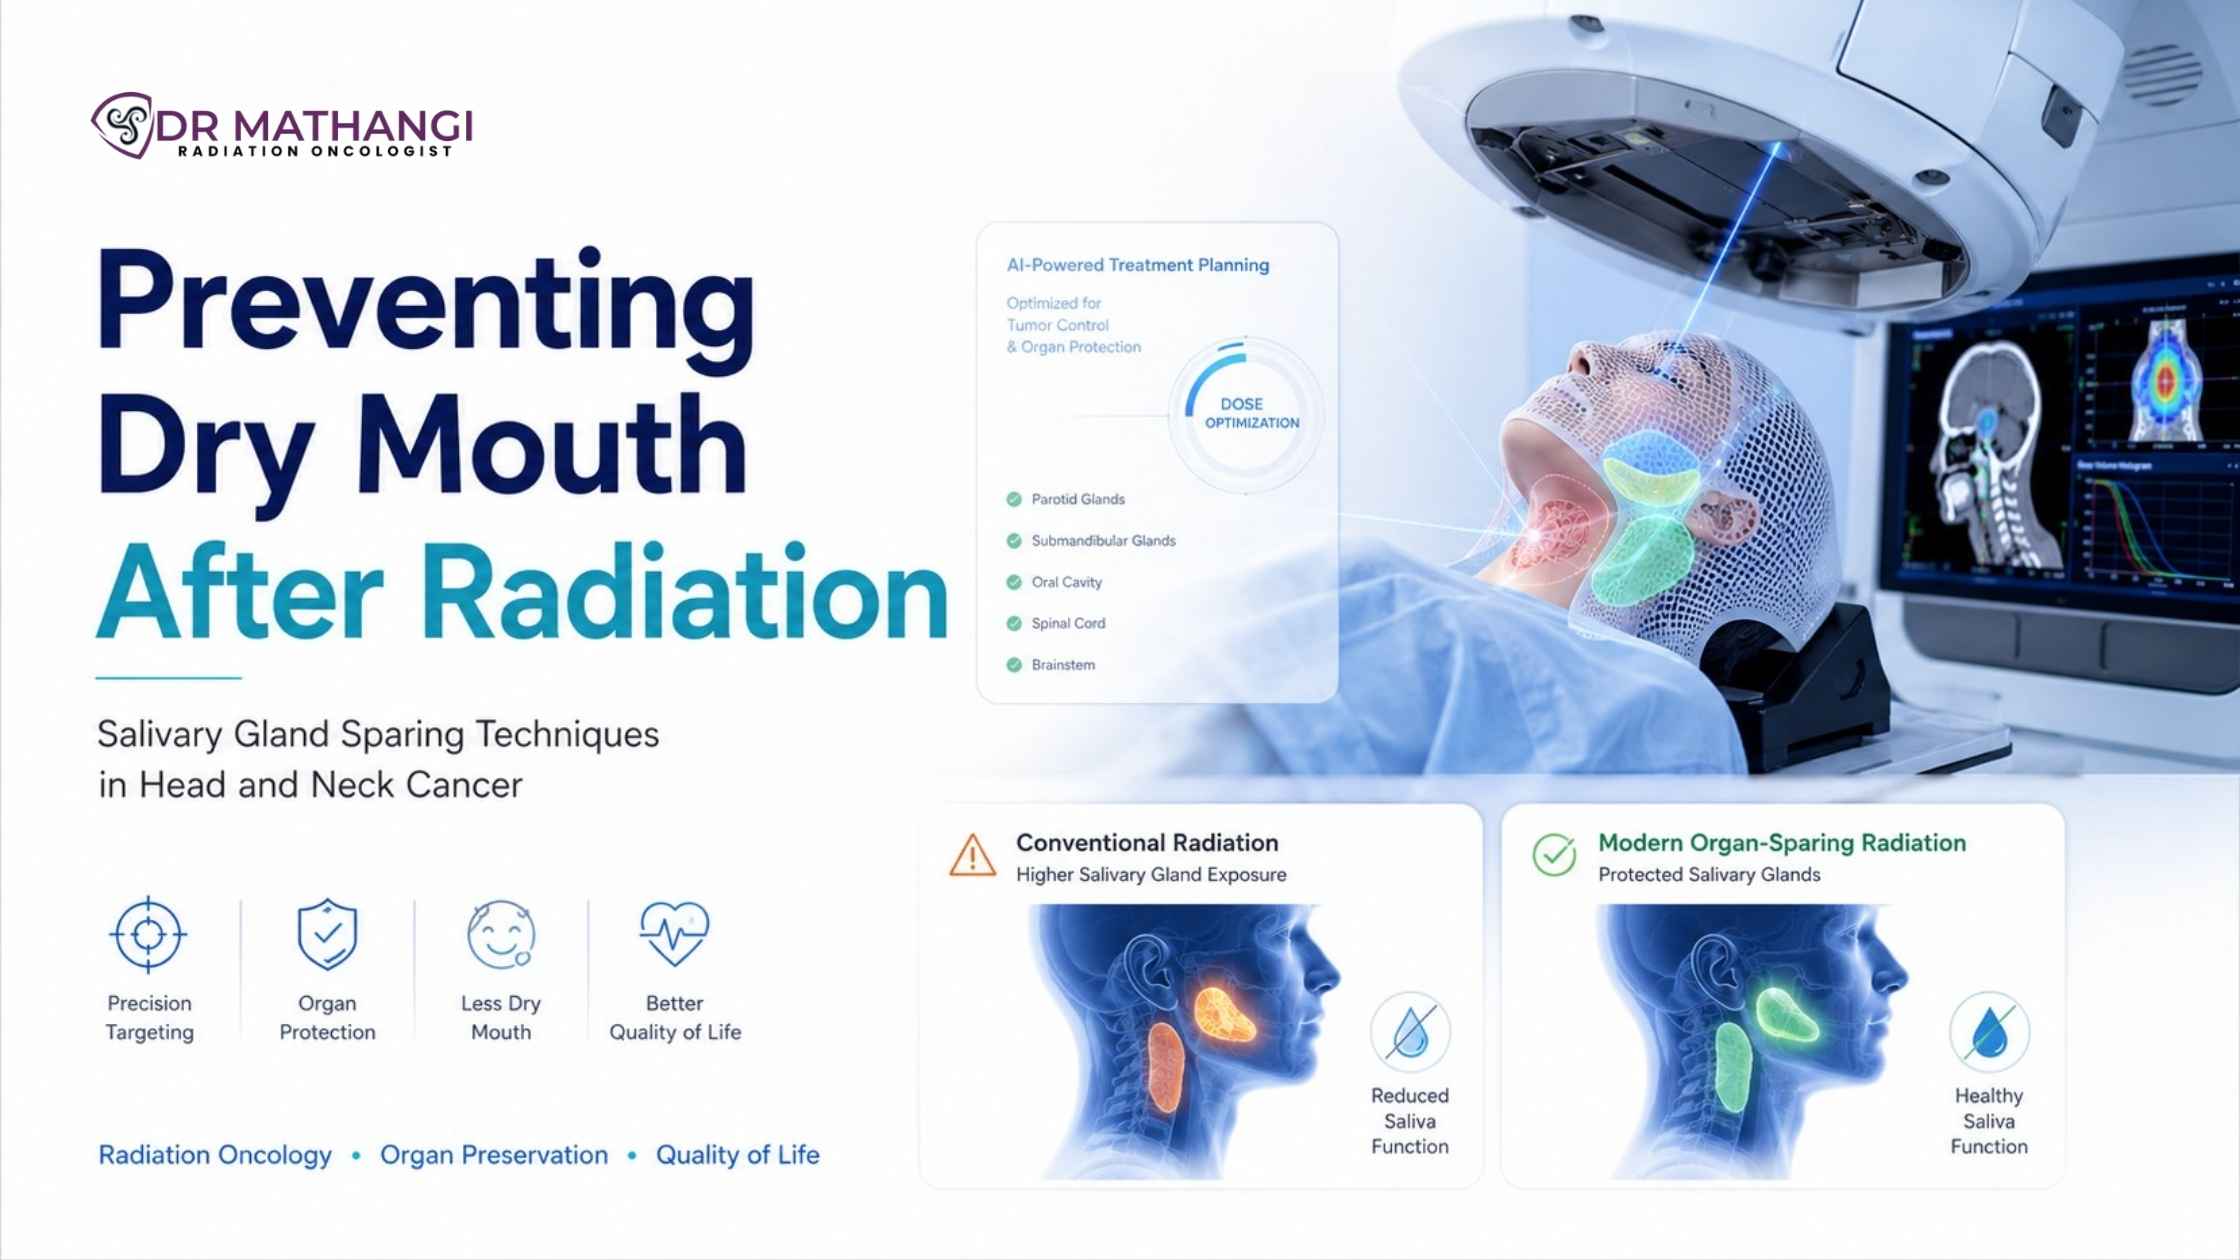
Preventing Dry Mouth After Radiation: Salivary Gland Sparing Techniques in Head and Neck Cancer

How can you prevent dry mouth after radiation therapy? The most effective way to prevent dry mouth after radiation therapy is through advanced salivary gland sparing radiation techniques, which precisely target cancer while minimizing exposure to salivary glands. This significantly reduces the risk of xerostomia, a common and life-altering side effect in head and neck cancer patients. According to recent studies, up to 80% of patients receiving head and neck radiotherapy experience some degree of dry mouth, impacting their quality of life, nutrition, and overall health. Understanding and implementing modern solutions is crucial for optimal cancer care outcomes.

What Is Salivary Gland Sparing Radiation And Why Is It Important?

Salivary gland sparing radiation is a cutting-edge approach in radiation oncology specifically designed to reduce radiation-induced damage to the major salivary glands during treatment of head and neck cancers. By utilizing highly focused radiation delivery systems, this technique ensures that essential glands such as the parotid and submandibular glands receive the lowest possible dose, thereby preserving their function.

  • Reduces the risk of dry mouth after radiation therapy (xerostomia)
  • Improves patients’ speech, taste, oral health, and swallowing
  • Promotes better nutrition and overall well-being

The significance of salivary gland sparing radiation cannot be overstated. Saliva is vital for oral hygiene, digestion, and comfort. When its production is compromised, patients face increased risk of dental decay, infections, and a marked decrease in their quality of life. For these reasons, leading centers like Gleneagles Cancer Institute, under the expertise of Dr Mathangi, have pioneered the adoption of these advanced techniques, setting new standards in cancer care.

How Does Head And Neck Radiotherapy Affect Salivary Glands?

Head and neck radiotherapy is essential for treating cancers of the oral cavity, pharynx, larynx, and related regions. However, traditional radiation techniques often expose the delicate salivary glands to high doses of radiation, leading to irreversible damage and reduced saliva production.

The effects can include:

  • Persistent dry mouth (xerostomia)
  • Difficulty swallowing and speaking
  • Altered sense of taste
  • Increased dental and gum problems
  • Higher susceptibility to oral infections

To address these challenges, Dr Mathangi utilizes advanced planning and delivery methods such as parotid sparing IMRT and submandibular gland contouring, which are designed to protect the salivary glands while effectively targeting the tumor.

What Is Xerostomia And How Can Prevention Strategies Help?

Xerostomia is the medical term for dry mouth caused by reduced or absent saliva flow. This side effect is particularly common after radiation therapy for head and neck cancers. Xerostomia prevention is critical, as persistent dry mouth can hinder basic functions such as chewing, swallowing, speaking, and even sleeping.

Prevention strategies implemented by Dr Mathangi include:

  1. Precision-targeted radiation with modern technology
  2. Implementation of salivary gland dose constraints during treatment planning
  3. Careful submandibular gland contouring to avoid unnecessary exposure
  4. Patient-specific protocols, adjusting treatment to minimize risk

These measures collectively reduce the incidence of xerostomia, leading to better treatment tolerance and improved patient satisfaction.

How Does Parotid Sparing IMRT Work In Head And Neck Cancer?

Parotid sparing IMRT (Intensity-Modulated Radiation Therapy) is a sophisticated form of radiotherapy that allows for precise modulation of radiation beams. By shaping the dose distribution and optimizing angles, IMRT targets cancer cells while minimizing exposure to the parotid glands, which are major producers of saliva.

Key benefits of parotid sparing IMRT include:

  • Significantly lower rates of dry mouth after radiation therapy
  • Preservation of saliva production, taste, and oral comfort
  • Less need for lifelong saliva substitutes or medications

Dr Mathangi’s expertise with IMRT, backed by her international training and technology leadership, ensures that every patient receives individualized care with the highest chance of preserving salivary gland function.

What Is Submandibular Gland Contouring And Why Is It Vital?

Submandibular gland contouring is a specialized technique in radiation planning where the submandibular glands are carefully mapped and delineated on imaging scans. This allows clinicians to set precise boundaries and avoid unnecessary radiation exposure to these glands.

The importance of submandibular gland contouring includes:

  • Enhancing the accuracy of salivary gland sparing radiation
  • Reducing the risk of dry mouth after radiation therapy
  • Protecting both major and minor salivary glands for optimal oral health

At Gleneagles Cancer Institute, Dr Mathangi utilizes advanced imaging and planning software to achieve optimal contouring, ensuring comprehensive cancer treatment without compromising quality of life.

What Are Salivary Gland Dose Constraints And How Do They Help?

Salivary gland dose constraints are scientifically established limits on the amount of radiation that salivary glands can safely receive during head and neck radiotherapy. By adhering to these constraints, the risk of permanent xerostomia is greatly minimized.

Typical dose constraints include:

Salivary Gland Recommended Dose Constraint Clinical Benefit
Parotid <26 Gy (mean dose) Preserves saliva secretion
Submandibular <39 Gy (mean dose) Reduces severe dry mouth

Dr Mathangi’s advanced planning protocols incorporate these dose constraints into every treatment plan, maximizing cancer control while minimizing side effects.

Why Choose Dr Mathangi For Head And Neck Radiotherapy?

Dr Mathangi J is a Senior Consultant & In-charge of Radiation Oncology at Gleneagles Cancer Institute, Bangalore. With over 20 years of experience and more than 12,000 patients successfully treated, she is a recognized authority in head and neck cancer management. Her commitment to excellence is reflected in her adoption of the latest technologies, including Stereotactic techniques (SRS/SBRT), Gated RapidArc, DIBH gated Radiotherapy, and image-guided Interstitial Brachytherapy.

Key reasons to trust Dr Mathangi with your care:

  • Pioneer in salivary gland sparing radiation techniques
  • Internationally trained in modern radiotherapy methods
  • Director of Fellowship in Advanced Radiotherapy
  • Leader in installing Asia Pacific’s first TrueBeam STx Machine
  • Personalized patient-centric approach

Choosing Dr Mathangi means opting for a future where head and neck cancer treatment does not come at the cost of your quality of life. Her expertise ensures every patient benefits from state-of-the-art care, meticulous planning, and compassionate support.

Who Needs Radiation Therapy?

According to Dr Mathangi, cancers that need radiation therapy (RT) include:

  • Head and neck cancers
  • Brain tumors
  • Spine tumors
  • Esophagus and rectal cancers
  • Lung cancers
  • Liver cancers
  • Breast cancers
  • Bladder cancers
  • Prostate cancers
  • Uterine cancers
  • Cervical cancer
  • Vulval cancers
  • Anal canal cancers
  • Penile cancers

If you or a loved one are facing any of these diagnoses, timely consultation with a radiation oncology expert is crucial. Advanced techniques in head and neck radiotherapy can make a significant difference in both cancer control and post-treatment quality of life.

How To Book A Consultation With Dr Mathangi?

Don’t let the fear of dry mouth after radiation therapy prevent you from seeking the best cancer care. With proven methods in salivary gland sparing radiation, parotid sparing IMRT, and submandibular gland contouring, Dr Mathangi is dedicated to both curing your cancer and preserving your quality of life.

Take the first step: Submit your contact information on the appointment form at https://drmathangi.com/contact/. Dr Mathangi’s team will promptly schedule your consultation and guide you through every step of your treatment journey.

About Dr Mathangi

Dr Mathangi J is a leading Radiation Oncologist based in Bangalore, heading the department at Gleneagles Cancer Institute. Renowned for her proficiency in advanced radiation techniques and her patient-centric philosophy, she has earned a reputation for delivering world-class cancer care. Her achievements, leadership roles, and commitment to ongoing education make her a trusted name for head and neck cancer treatment in South and North India.

Frequently Asked Questions

What is salivary gland sparing radiation and how does it help prevent dry mouth after radiation therapy?

Salivary gland sparing radiation is an advanced technique used during head and neck radiotherapy to minimize radiation exposure to the salivary glands. By carefully planning the treatment to avoid or limit radiation to these glands, the risk of developing dry mouth after radiation therapy—also known as xerostomia—can be significantly reduced. Dr. Mathangi specializes in using these approaches to protect your quality of life during and after cancer treatment.

Why is xerostomia prevention important for patients undergoing head and neck radiotherapy?

Xerostomia, or persistent dry mouth, is a common side effect of head and neck radiotherapy that can affect speech, taste, swallowing, and dental health. Preventing xerostomia is crucial because it improves comfort, nutrition, and overall well-being. Dr. Mathangi’s protocols focus on xerostomia prevention as a key part of comprehensive cancer care, using advanced planning and precision techniques.

How does parotid sparing IMRT work?

Parotid sparing IMRT (Intensity Modulated Radiation Therapy) is a method that shapes radiation beams to avoid the parotid glands, which are major sources of saliva. By precisely targeting tumors while sparing these glands, this technique significantly lowers the chances of severe dry mouth. Dr. Mathangi frequently uses parotid sparing IMRT to optimize both cancer control and quality of life outcomes for her patients.

What is submandibular gland contouring and why is it important?

Submandibular gland contouring involves accurately identifying and outlining the submandibular glands during radiation planning. This enables clinicians to limit the radiation dose these glands receive, preserving their function and reducing xerostomia. Dr. Mathangi emphasizes the importance of submandibular gland contouring as part of her comprehensive approach to salivary gland preservation.

What are salivary gland dose constraints, and how are they determined?

Salivary gland dose constraints are specific limits set on the amount of radiation that salivary glands should receive during treatment planning. These constraints are based on research evidence and international guidelines, aiming to balance effective tumor control with minimizing side effects. Dr. Mathangi meticulously applies these constraints in each patient’s plan to ensure the best possible salivary gland function after treatment.

Can all patients benefit from salivary gland sparing techniques?

Most patients with head and neck cancer can benefit from salivary gland sparing techniques, but the suitability depends on the tumor’s location and stage. Dr. Mathangi assesses each case individually to determine how best to apply these methods for maximum benefit without compromising cancer control.

What additional strategies does Dr. Mathangi offer for managing dry mouth after radiation therapy?

In addition to advanced radiotherapy planning, Dr. Mathangi offers supportive measures such as saliva substitutes, oral care guidance, and regular follow-up to monitor and manage dry mouth after radiation therapy. Her holistic approach ensures that patients receive comprehensive care throughout their treatment journey.

How can I discuss salivary gland sparing options with Dr. Mathangi before starting treatment?

Dr. Mathangi encourages open communication and shared decision-making. During your consultation, she will explain all available options, including salivary gland sparing radiation, and answer any questions you may have about side effect prevention and quality of life after treatment.

Are these salivary gland sparing techniques available for all types of head and neck radiotherapy?

While most modern head and neck radiotherapy treatments can incorporate salivary gland sparing approaches, the feasibility will depend on your individual case. Dr. Mathangi uses the latest evidence-based techniques, including advanced imaging and planning, to maximize the use of these strategies whenever appropriate.


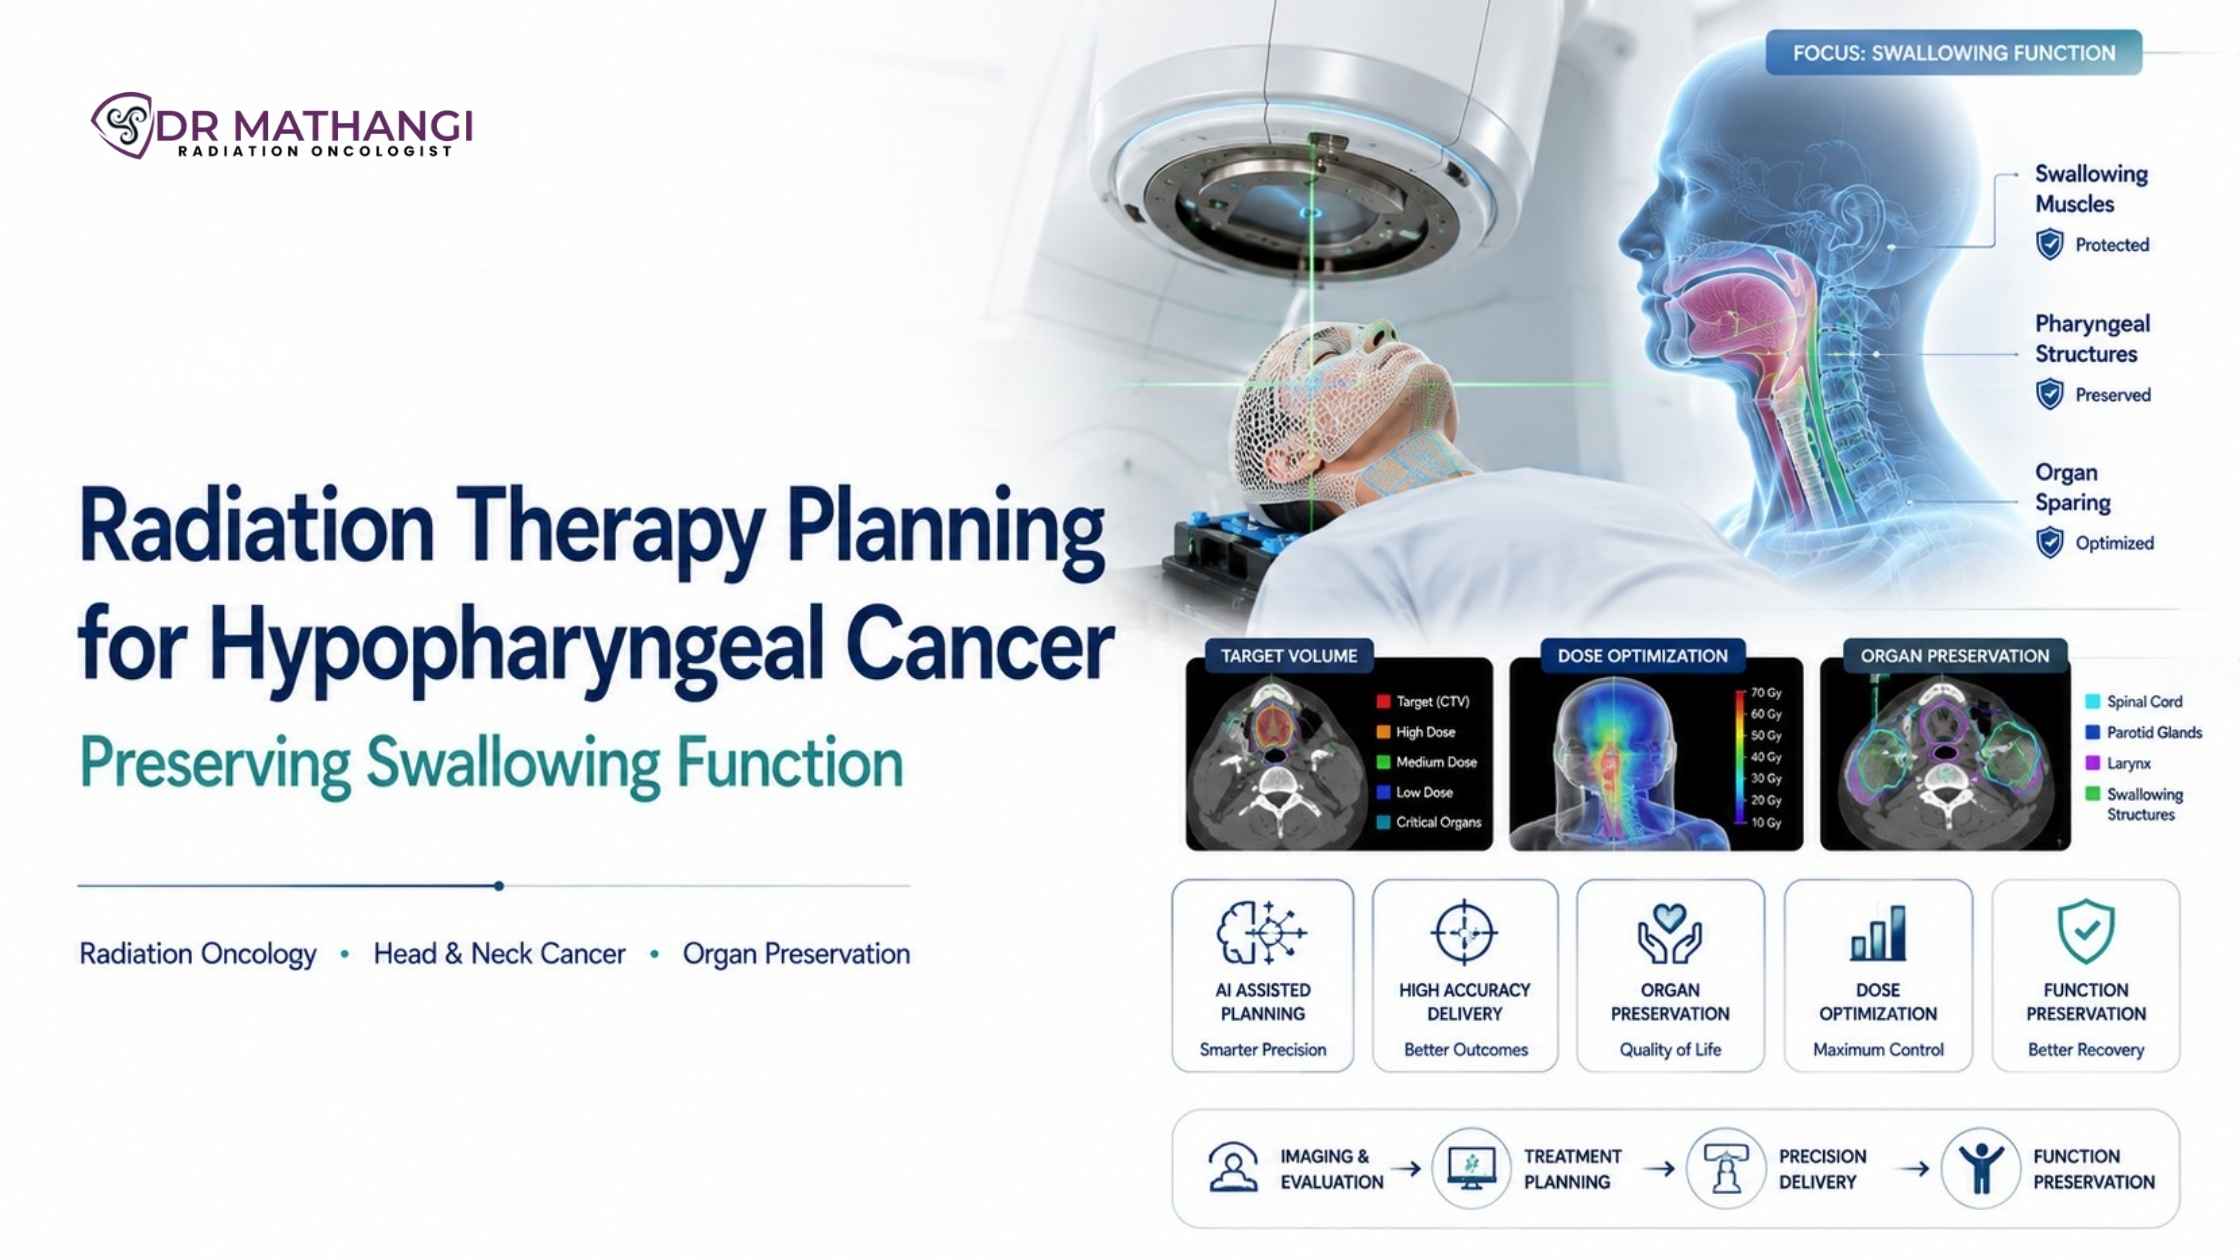
Radiation Therapy Planning for Hypopharyngeal Cancer: Preserving Swallowing Function

What Is Radiation Therapy Planning For Hypopharyngeal Cancer?

Radiation therapy planning for hypopharyngeal cancer is a sophisticated process that aims to precisely target malignant tissues while minimizing the impact on critical structures involved in swallowing. According to global cancer statistics, hypopharyngeal cancers account for approximately 3-5% of all head and neck cancers, but their management is particularly challenging due to their proximity to the swallowing apparatus and the high risk of functional impairment.

At Gleneagles Cancer Institute in Bangalore, Dr Mathangi J stands at the forefront of radiation therapy for throat cancer with a patient-centered approach that prioritizes both tumor control and quality of life. Patients who undergo expertly planned therapy enjoy better outcomes, including preserved swallowing function and reduced long-term complications.

How Is Hypopharyngeal Carcinoma Radiotherapy Structured To Maximize Benefits?

Hypopharyngeal carcinoma radiotherapy must navigate the delicate balance between eradicating cancer and safeguarding vital anatomical structures. The hypopharynx is surrounded by muscles and nerves essential for swallowing and speech, making precision in therapy delivery crucial.

  • Advanced Imaging and Target Delineation: Using state-of-the-art imaging technologies, Dr Mathangi maps out tumor boundaries and critical neighboring structures in 3D, ensuring only the tumor receives the high dose of radiation.
  • Customized Dose Distribution: By tailoring the radiation dose, Dr Mathangi minimizes exposure to the swallowing and voice mechanisms, reducing the risk of treatment-related complications.
  • Continuous Monitoring: Throughout the course of therapy, regular imaging and clinical assessment ensure that any changes in anatomy or tumor size are quickly addressed.

This meticulous approach is especially valuable for patients seeking functional preservation post-treatment.

What Is Swallowing Apparatus Sparing And Why Does It Matter?

Swallowing apparatus sparing refers to the intentional reduction of radiation dose to muscles and nerves critical for swallowing, such as the pharyngeal constrictor muscles. Preserving these structures is vital for maintaining the ability to eat and drink normally after treatment.

  • Reduction in Dysphagia: Sparing the swallowing apparatus significantly decreases the risk of dysphagia prevention, a common complication where patients experience difficulty swallowing.
  • Improved Quality of Life: Patients are more likely to retain natural eating and speaking abilities, avoiding the need for feeding tubes or long-term dietary restrictions.

Dr Mathangi is a pioneer in incorporating advanced techniques to achieve optimal swallowing apparatus sparing in every treatment plan.

How Does Dysphagia Prevention Fit Into Radiation Therapy For Throat Cancer?

Dysphagia prevention is one of the cornerstones of modern radiation therapy for throat cancer. Dysphagia, or difficulty swallowing, is not just a side effect but a potential life-altering complication that can lead to malnutrition, aspiration pneumonia, and diminished quality of life.

  1. Targeted Therapy: By limiting radiation exposure to the pharyngeal constrictor muscles and other swallowing-related structures, Dr Mathangi minimizes the incidence of acute and chronic dysphagia.
  2. Rehabilitation Integration: Early involvement of speech and swallowing therapists ensures that patients receive timely exercises and interventions, further reducing the risk.

Dr Mathangi’s approach integrates proactive dysphagia prevention into every phase of the treatment journey.

What Role Do Pharyngeal Constrictor Muscles Play In Radiation Therapy Planning?

The pharyngeal constrictor muscles are a group of muscles that form the muscular wall of the pharynx and are essential for initiating the swallowing reflex. Sparing these muscles during radiation is crucial for reducing post-treatment swallowing difficulties.

Impact of Sparing Pharyngeal Constrictor Muscles
Aspect Without Sparing With Sparing
Swallowing Function Significantly impaired Typically preserved
Risk of Dysphagia High Low
Quality of Life Reduced Maintained

Dr Mathangi’s precision targeting ensures that these muscles are protected as much as possible, highlighting her commitment to functional preservation.

Why Is Laryngeal Preservation Important In Hypopharyngeal Cancer?

Laryngeal preservation is a key goal in the management of hypopharyngeal cancer. The larynx, or voice box, is not only vital for speech but also for preventing aspiration during swallowing.

  • Functional Outcomes: Saving the larynx allows patients to retain their natural voice and avoid permanent tracheostomy.
  • Holistic Well-being: Preserving the larynx reduces psychological distress and helps patients reintegrate into society.

Through advanced IMRT planning, Dr Mathangi maximizes tumor control while prioritizing laryngeal preservation, ensuring the best possible balance between cure and quality of life.

How Does IMRT Planning Transform Radiation Therapy For Throat Cancer?

IMRT planning—Intensity-Modulated Radiation Therapy—is a revolutionary technology that allows radiation beams to be shaped and modulated with extraordinary precision. This means the cancer gets the full prescribed dose, while critical structures receive minimal exposure.

  1. Precision and Personalization: IMRT allows for highly personalized treatment, adjusting beam angles and intensity to the patient’s unique anatomy.
  2. Reduced Side Effects: By sparing healthy tissues, IMRT reduces the risk of both short- and long-term complications, such as dysphagia and voice changes.
  3. Proven Outcomes: Clinical studies show that IMRT significantly improves both tumor control and post-treatment quality of life in head and neck cancers.

Dr Mathangi’s expertise in IMRT planning, honed over two decades and 12,000+ patients, places her among the most sought-after specialists for complex head and neck cancers in South India.

Why Choose Dr Mathangi For Radiation Therapy Planning In Hypopharyngeal Cancer?

When it comes to radiation therapy for throat cancer, experience and expertise make all the difference. Dr Mathangi J, Senior Consultant and In-charge of Radiation Oncology at Gleneagles Cancer Institute, Bangalore, is renowned for her pioneering work in advanced radiotherapy techniques.

  • Over 20 years of dedicated experience
  • 12,000+ patients successfully treated
  • Expert in stereotactic techniques, IGRT, RapidArc, and interstitial brachytherapy
  • Asia Pacific’s first TrueBeam STx installation under her leadership
  • Director of Fellowship in Advanced Radiotherapy Techniques (RGUHS)

Her commitment to swallowing apparatus sparing and dysphagia prevention ensures that patients not only survive but thrive after treatment. If you want the best chance at preserving your swallowing function and voice, entrusting your care to Dr Mathangi is a decision you won’t regret.

What Are The Next Steps For Patients Seeking Expert Care?

If you or a loved one is facing hypopharyngeal cancer or another head and neck malignancy, timely and specialized care is crucial for the best outcomes. Here’s how to get started:

  1. Submit Your Details: Visit this contact form and submit your contact information.
  2. Appointment Scheduling: Dr Mathangi’s team will promptly coordinate your appointment and notify you with all the details.
  3. Comprehensive Evaluation: Undergo a thorough assessment and receive a personalized treatment plan.
  4. Begin Your Journey: Start your path to recovery with the assurance of world-class care and unwavering support.

Don’t miss the opportunity to safeguard your quality of life—book your appointment with Dr Mathangi today!

About Dr Mathangi

Dr Mathangi J is a Senior Radiation Oncologist and In-charge of Radiation Oncology at Gleneagles Cancer Institute, Bangalore. With prestigious qualifications (MBBS, DMRT, DNB) and international training in advanced radiation techniques from Germany and Denmark, she is recognized as a leader in head and neck cancer treatment. Her expertise spans stereotactic ablative radiotherapy, gated RapidArc, DIBH gated radiotherapy, and image-guided interstitial brachytherapy. She is the Director of the Fellowship in Advanced Radiotherapy Techniques at RGUHS and has been instrumental in bringing cutting-edge technology like the TrueBeam STx to the Asia Pacific region.

Gleneagles Cancer Institute, part of Gleneagles Hospitals, is a center of excellence in cancer care, renowned for its holistic approach and patient-centric philosophy.

Frequently Asked Questions

What is the significance of swallowing apparatus sparing in radiation therapy for throat cancer?

Swallowing apparatus sparing refers to advanced planning techniques that minimize radiation dose to critical swallowing structures such as the pharyngeal constrictor muscles and larynx. This approach is especially important in radiation therapy for throat cancer, as it helps reduce the risk of dysphagia and maintains quality of life. Dr. Mathangi uses precise contouring and modern radiotherapy methods to prioritize these structures during treatment planning.

How does hypopharyngeal carcinoma radiotherapy impact swallowing function?

Hypopharyngeal carcinoma radiotherapy can unintentionally damage the muscles and nerves responsible for swallowing, leading to difficulties such as aspiration and persistent swallowing problems. Dr. Mathangi’s approach involves detailed mapping and targeted treatment to reduce the dose to the swallowing apparatus, thereby helping to preserve normal swallowing function as much as possible.

What steps are taken during IMRT planning to prevent dysphagia?

IMRT planning (Intensity-Modulated Radiation Therapy) allows for highly conformal dose distribution. During planning, Dr. Mathangi identifies and outlines the pharyngeal constrictor muscles and other critical swallowing structures. By applying strict dose constraints to these areas, she minimizes their exposure, actively supporting dysphagia prevention and improving post-treatment swallowing outcomes.

Why are the pharyngeal constrictor muscles important in treatment planning?

The pharyngeal constrictor muscles play a vital role in the act of swallowing. If exposed to high radiation doses, these muscles can become stiff or weak, leading to swallowing difficulties. Dr. Mathangi meticulously contours these muscles during planning and aims to keep their radiation dose as low as safely possible, which is a cornerstone of her patient-centered technique.

How does Dr. Mathangi achieve laryngeal preservation during radiation therapy?

Laryngeal preservation is a major goal in treating hypopharyngeal cancers. Dr. Mathangi leverages advanced imaging and IMRT technology to accurately target the tumor while sparing the larynx from high radiation doses. This approach not only helps maintain voice and breathing functions but also supports better long-term swallowing outcomes.

What is dysphagia prevention and how is it integrated into Dr. Mathangi’s protocols?

Dysphagia prevention is the proactive effort to avoid or minimize swallowing difficulties after radiation therapy. In Dr. Mathangi’s protocols, this means early identification of at-risk structures, detailed IMRT planning, and collaboration with speech and swallowing therapists before, during, and after treatment. This multi-disciplinary strategy leads to better functional outcomes for patients.

Are there specific solutions offered by Dr. Mathangi for patients with pre-existing swallowing issues?

Yes, Dr. Mathangi tailors treatment for patients with pre-existing swallowing difficulties. She collaborates closely with rehabilitation specialists and employs swallowing apparatus sparing approaches. By customizing radiation fields and leveraging advanced planning, she aims to stabilize or even improve swallowing function throughout the treatment journey.

How does swallowing apparatus sparing affect long-term quality of life?

Swallowing apparatus sparing has a profound impact on long-term quality of life. By reducing the radiation dose to the muscles and structures involved in swallowing, Dr. Mathangi’s approach minimizes the risk of chronic swallowing difficulties, feeding tube dependence, and aspiration pneumonia. This enables patients to maintain more normal eating and social interactions after treatment.

What makes Dr. Mathangi’s approach to radiation therapy for throat cancer unique?

Dr. Mathangi combines expertise in hypopharyngeal carcinoma radiotherapy with a passionate focus on functional preservation. Her use of IMRT planning, swallowing apparatus sparing, and multi-disciplinary care allows for effective tumor control while prioritizing swallowing and laryngeal preservation. Patients benefit from both cutting-edge technology and individualized support throughout their treatment.


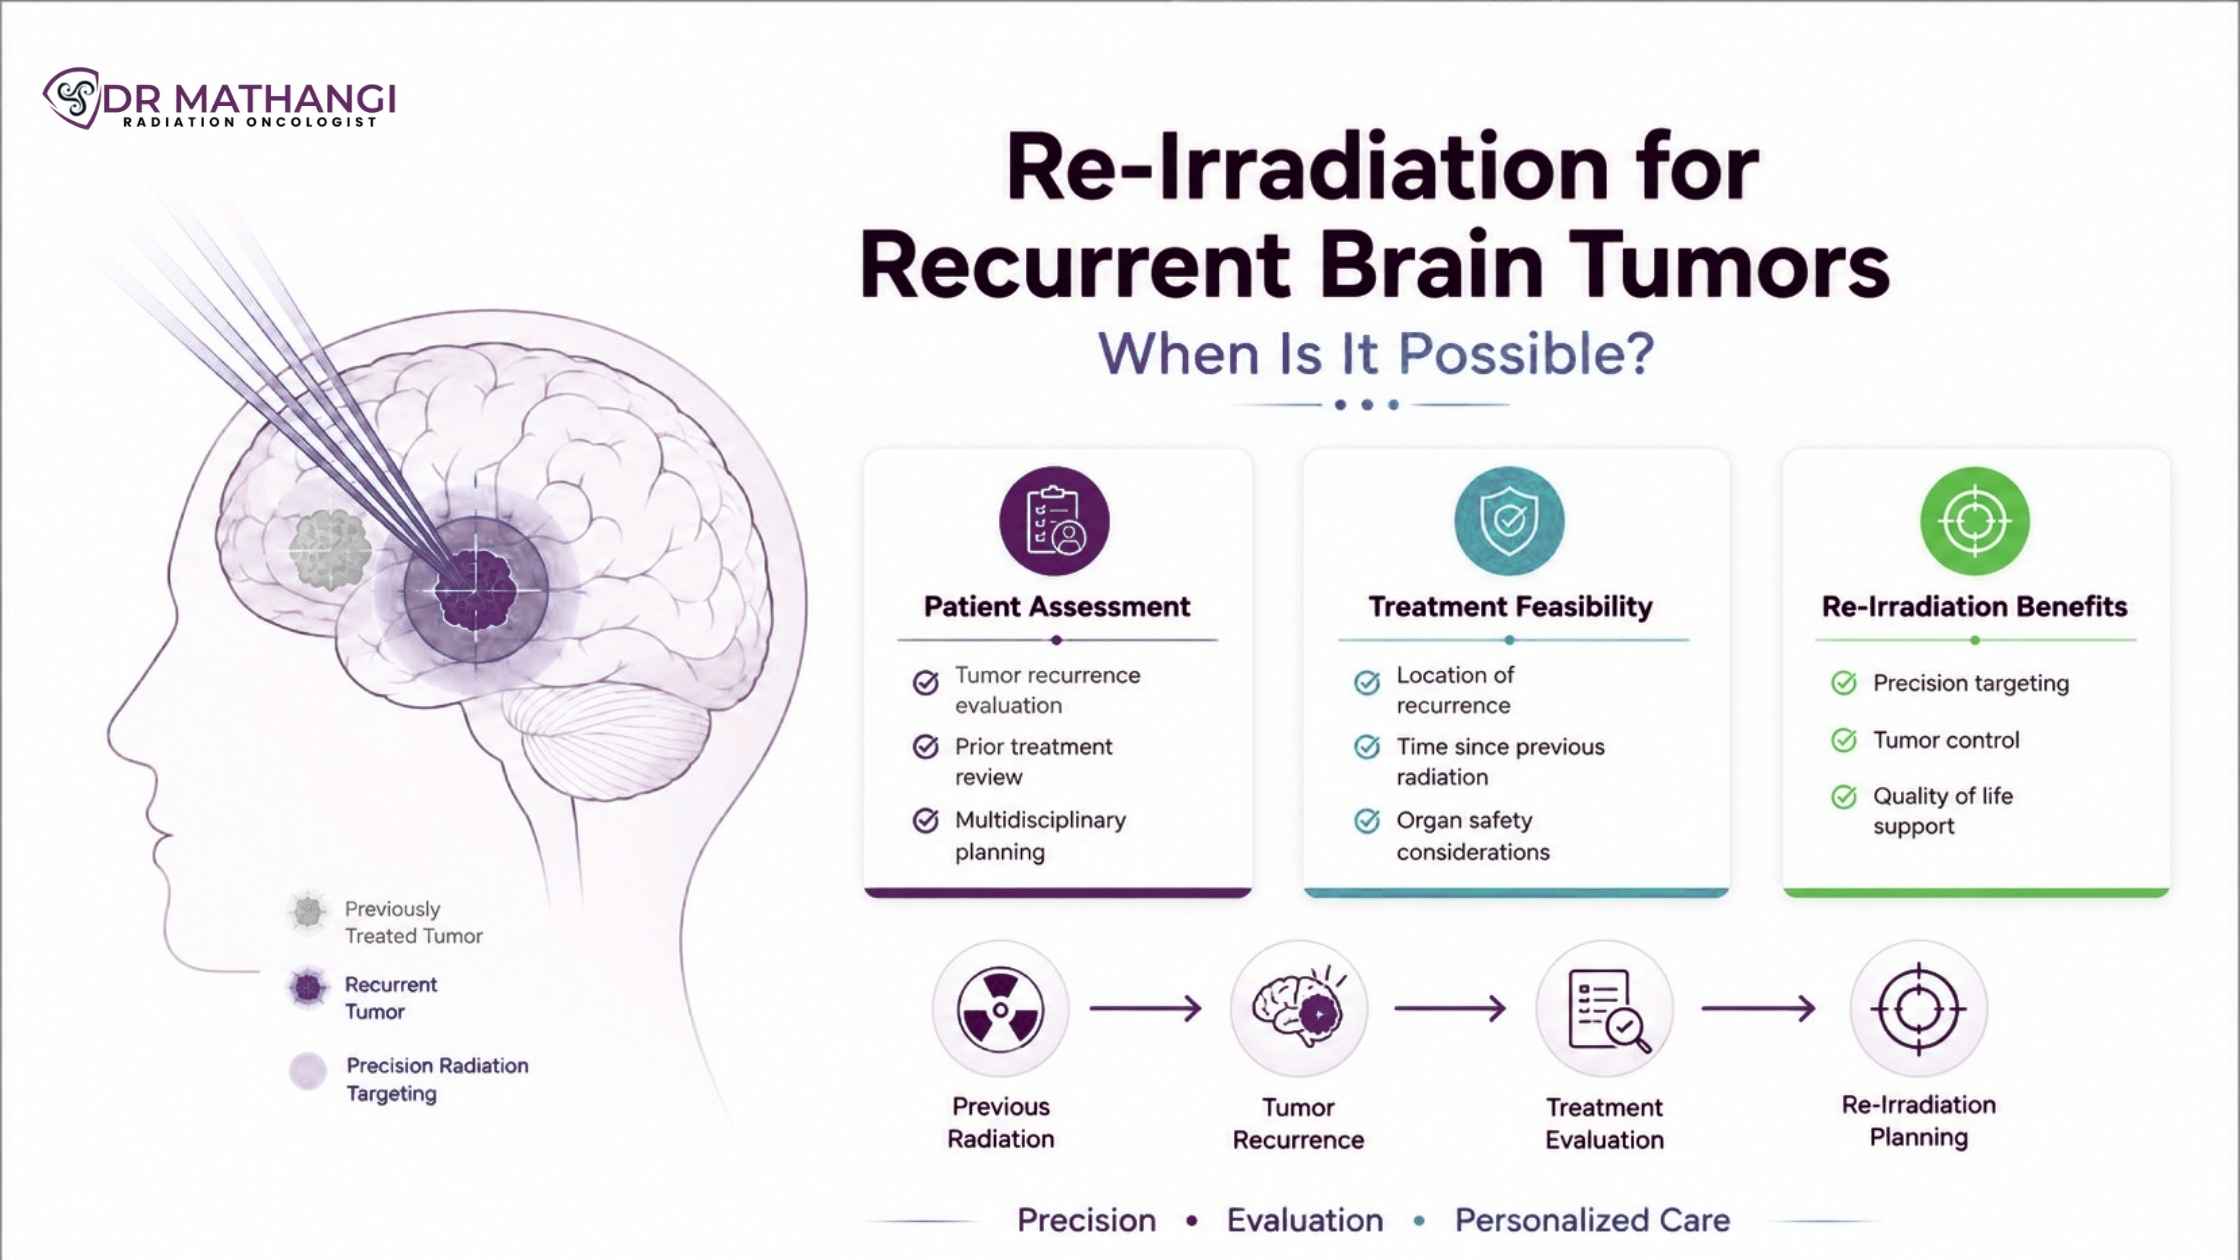
Re-Irradiation for Recurrent Brain Tumors: When Is It Possible?

Quick answer: Re-irradiation for recurrent brain tumors is possible in select patients when careful assessment of prior treatment, tumor characteristics, and advanced imaging confirm eligibility. At Gleneagles Cancer Institute, Dr Mathangi J delivers tailored, advanced re-irradiation options for challenging brain tumor recurrences.

Did you know? Over 30% of patients with brain tumors experience recurrence after initial treatment[1], often facing limited therapeutic options. However, re irradiation recurrent brain tumor strategies have evolved, offering new hope for these patients under expert care. At the forefront of this transformation in South India and beyond is Dr Mathangi J, Senior Consultant & In-charge of Radiation Oncology at Gleneagles Cancer Institute, Bangalore. With over two decades of experience and more than 12,000 patients treated, Dr Mathangi is redefining outcomes for patients with recurrent brain tumors using world-class technology and personalized care.

What Is Re-Irradiation For Recurrent Brain Tumors?

Re-irradiation refers to the precise delivery of a second (or subsequent) course of radiation therapy to a brain tumor that has recurred after initial radiation. Thanks to technological advances, re irradiation recurrent brain tumor is now feasible for selected cases, potentially controlling tumor growth, extending survival, and improving quality of life.

  • Re-irradiation is not a “one size fits all” approach.
  • It requires careful patient selection, advanced imaging, and expert multidisciplinary input.
  • Modern techniques like stereotactic radiosurgery and image-guided radiotherapy maximize tumor targeting and minimize risks.

When Is Re-Irradiation Possible? Key Factors

The decision to offer re irradiation recurrent brain tumor is complex. Dr Mathangi J and her team follow an evidence-based, highly individualized approach, considering these factors:

  1. Previous Radiation Details: The type, dose, and area previously treated. This determines the cumulative radiation dose the brain can safely receive.
  2. Time Since Last Radiation: A longer interval (usually >6-12 months) between treatments lowers toxicity risks and increases re-irradiation eligibility.
  3. Location and Size of Recurrence: Tumors that are small, well-defined, and not near critical brain structures are better candidates.
  4. Patient’s General Health: Functional status, age, and comorbidities influence the safety and benefits of re-irradiation.
  5. Tumor Biology: Slow-growing tumors (like low-grade gliomas or meningiomas) are more amenable to repeated radiation than aggressive, rapidly recurrent cancers.

At Gleneagles Cancer Institute, Dr Mathangi uses state-of-the-art planning and multidisciplinary tumor boards to ensure only the most suitable patients are offered this advanced treatment, maximizing benefit while minimizing harm.

How Does Recurrent Brain Tumor Radiation Differ From Initial Treatment?

Recurrent brain tumor radiation is fundamentally different from the first course of radiotherapy. The brain’s tolerance is limited — too much radiation can cause irreversible damage. Therefore, re-irradiation relies on advanced techniques:

  • Stereotactic Radiosurgery (SRS): Delivers high-dose, pinpointed radiation in 1-5 sessions, ideal for small, well-defined recurrences.
  • Fractionated Stereotactic Radiotherapy (FSRT): Uses multiple smaller doses to reduce risk to healthy brain.
  • Image-Guided Radiotherapy (IGRT): Maximizes accuracy by using real-time imaging during each session.
  • RapidArc and Intensity Modulated Radiotherapy (IMRT): Shape radiation beams to the tumor’s contours, sparing healthy tissue.

These techniques are available at Gleneagles Cancer Institute, where Dr Mathangi’s expertise ensures each plan is individualized for safety and effectiveness.

How Are Patients Selected For Re-Irradiation?

The selection process is rigorous, designed to maximize benefits and minimize risks. Here’s how Dr Mathangi’s team approaches it:

  1. History Review: Detailed analysis of previous treatments, including cumulative radiation dose and tumor response.
  2. Current Imaging: Advanced scans, especially tumor progression imaging and perfusion MRI, are critical in differentiating between true tumor recurrence and treatment-related changes (like radiation necrosis).
  3. Multidisciplinary Board: Radiation oncologists, neurosurgeons, neuroradiologists, and medical oncologists collaborate to assess all aspects of the patient's case.
  4. Patient Goals: Candid discussion about expected outcomes, potential risks, and patient preferences.

Only after this comprehensive assessment is a patient considered for re irradiation recurrent brain tumor therapy at Dr Mathangi’s center.

What Are The Risks Of Re-Irradiation?

While re-irradiation offers hope, it is not risk-free. The main concerns include:

  • Radiation Necrosis: Damage to healthy brain tissue, presenting as swelling, neurological deficits, or seizures. Advanced planning and imaging, such as perfusion MRI, help predict and minimize this risk.
  • Cognitive Effects: Memory, attention, or processing speed may be affected, especially with larger fields or repeated high doses.
  • Acute Side Effects: Fatigue, headache, nausea, or skin reactions, which are usually manageable.
  • Vascular Injury: Rare but serious damage to blood vessels, especially with high cumulative radiation dose.

At Gleneagles, Dr Mathangi uses the latest evidence, careful planning, and patient monitoring to minimize complications. Her advanced training in stereotactic and IGRT techniques further reduces the risk of radiation necrosis and other side effects.

How Is Tumor Progression Or Recurrence Diagnosed?

Distinguishing true recurrence from treatment effects is crucial. Tumor progression imaging plays a pivotal role. Here’s what Dr Mathangi’s protocol includes:

  • Conventional MRI: Essential for anatomical detail but sometimes limited in differentiating recurrence from post-treatment changes.
  • Perfusion MRI: Measures blood flow to the lesion. Higher perfusion suggests active tumor, while lower perfusion points to necrosis or scarring.
  • PET-CT: May be used for metabolic imaging in ambiguous cases.

These tools, combined with clinical assessment, ensure only genuine recurrences are targeted for stereotactic radiosurgery recurrence or other re-irradiation strategies.

What Is Stereotactic Radiosurgery For Recurrence?

Stereotactic radiosurgery recurrence refers to the use of high-precision, single-session (or hypofractionated) radiation for treating brain tumors that have returned after initial therapy.

  • It is particularly effective for small, well-defined tumors or metastases.
  • Reduces exposure of healthy brain tissue, minimizing risks.
  • Often used when surgery is not feasible or as an adjunct to other therapies.

Dr Mathangi’s expertise in SRS and SBRT, honed at leading international centers, ensures patients at Gleneagles Cancer Institute receive the safest and most effective care for recurrent brain tumor radiation.

What Are The Outcomes And Benefits Of Re-Irradiation?

When performed in experienced hands, re irradiation recurrent brain tumor offers:

  • Improved Tumor Control: Especially for slowly progressive or oligometastatic disease.
  • Extended Survival: Select patients may experience meaningful life extension.
  • Better Quality Of Life: Relief of neurological symptoms, reduced need for steroids, and preserved independence.
  • Minimal Downtime: Outpatient, non-invasive, and often completed in just a few sessions.

Published studies and real-world experience at Gleneagles Cancer Institute confirm the value of expert-led re-irradiation, with many patients reporting significant symptom relief and prolonged stability.

Why Choose Dr Mathangi J For Re-Irradiation?

Your choice of specialist is critical for the success and safety of re irradiation recurrent brain tumor therapy. Here’s why Dr Mathangi stands out:

  • Global-Standard Training: Advanced expertise from leading European centers in SRS, SBRT, IGRT, and intraoperative radiotherapy.
  • Track Record: Over 20 years of experience and 12,000+ patients successfully treated, including numerous complex re-irradiation cases.
  • Technology Leadership: Asia Pacific’s first TrueBeam STx Machine, Gated RapidArc, and DIBH gated radiotherapy.
  • Personalized Care: Each case is reviewed by a multidisciplinary team, with tailored plans for maximum benefit and safety.
  • Academic Leadership: Director of Fellowship in Advanced Radiotherapy Techniques, ensuring adoption of the latest protocols and ongoing innovation.

Patients and referring doctors across South and North India trust Dr Mathangi and her team for their blend of compassion, expertise, and results.

How To Book A Consultation With Dr Mathangi?

If you or a loved one is facing a re irradiation recurrent brain tumor situation, expert guidance can make all the difference. To schedule a personalized consultation with Dr Mathangi at Gleneagles Cancer Institute, simply use the form at https://drmathangi.com/contact/. Submit your contact information, and her team will promptly arrange your appointment and notify you with details.

Don’t let uncertainty limit your options. Access the most advanced re-irradiation strategies and compassionate care with Dr Mathangi J—your partner in conquering recurrent brain tumors.

About Dr Mathangi J

Dr Mathangi J is a highly respected Senior Consultant & In-charge of Radiation Oncology at Gleneagles Cancer Institute, Bangalore, part of Gleneagles Hospitals. She brings over 20 years of expertise, specializing in brain tumors, head and neck cancers, prostate, lung, and women’s cancers. With advanced international training and a pioneering spirit, Dr Mathangi has transformed cancer care in India. She leads with a commitment to innovation, safety, and patient-centered excellence, making her the preferred choice for re irradiation recurrent brain tumor and complex radiation oncology cases.

References

  1. Stupp R, et al. “Recurrent malignant glioma: From molecular biology to clinical management.” The Lancet Oncology. 2001;2(8):494-503.

Frequently Asked Questions

What is re-irradiation for recurrent brain tumors and when is it considered?

Re-irradiation for recurrent brain tumors refers to delivering another course of radiation therapy to a brain area previously treated with radiation. This approach is considered when a tumor recurs after initial treatment, and options like surgery or systemic therapy are limited or not feasible. Dr. Mathangi carefully evaluates each patient’s history, including prior radiation details and the potential risks, before recommending re irradiation recurrent brain tumor as a treatment.

How does Dr. Mathangi determine if re-irradiation is possible for my case?

Dr. Mathangi assesses several factors: the type and location of the recurrent brain tumor, the interval since initial radiation, previous cumulative radiation dose, the patient’s clinical status, and imaging findings. Advanced imaging techniques, such as perfusion MRI, help distinguish between tumor progression and radiation necrosis, guiding the decision-making process.

What advanced techniques are used for recurrent brain tumor radiation?

For recurrent brain tumor radiation, Dr. Mathangi often recommends highly precise methods like stereotactic radiosurgery (SRS) or fractionated stereotactic radiotherapy (FSRT). These techniques allow for focused delivery of radiation to the tumor while minimizing exposure to healthy brain tissue—crucial for patients who have already received radiation previously.

How does stereotactic radiosurgery help in cases of recurrence?

Stereotactic radiosurgery recurrence management involves delivering a high dose of radiation in a single or few sessions with pinpoint accuracy. This approach is especially useful for small, well-defined recurrent tumors and can offer a chance for tumor control with reduced risk of harming surrounding brain structures.

What are the risks of re-irradiation, and how are they managed?

The main risks of re-irradiation include radiation necrosis (damage to normal brain tissue) and other neurological side effects. Dr. Mathangi uses advanced planning software, careful calculation of cumulative radiation dose, and regular monitoring with imaging to minimize these risks. Early detection and management strategies are implemented if any complications arise.

How is tumor progression differentiated from radiation necrosis on imaging?

Distinguishing between tumor progression and radiation necrosis can be challenging. Dr. Mathangi utilizes advanced tumor progression imaging, including perfusion MRI and other modalities, to assess blood flow and metabolic activity in the suspicious area. This helps tailor the treatment plan more accurately and avoid unnecessary interventions.

What is the importance of cumulative radiation dose in re-irradiation?

The cumulative radiation dose is the total amount of radiation the brain tissue has received from all treatments. Dr. Mathangi carefully calculates this to ensure that the new dose does not exceed safe limits, thus reducing the risk of severe side effects and optimizing the chances of successful re irradiation recurrent brain tumor treatment.

What new imaging techniques are used to plan re-irradiation for recurrent tumors?

In addition to standard MRI, Dr. Mathangi employs advanced imaging such as perfusion MRI, MR spectroscopy, and PET scans. These modalities provide detailed information about the tumor’s blood supply, metabolic activity, and biological behavior, helping to accurately identify areas suitable for recurrent brain tumor radiation and to spare healthy tissue.

What follow-up care is required after re-irradiation for a recurrent brain tumor?

After re-irradiation, Dr. Mathangi provides close follow-up with regular clinical assessments and repeat imaging to monitor for tumor response, radiation necrosis, or late effects. Long-term care plans are tailored for each patient to address any new symptoms promptly and maintain quality of life.


SBRT for Oligometastatic Lung Cancer: Treatment Selection and Outcomes

Author: Dr Mathangi J, Sr Consultant & In-charge - Radiation Oncology, Gleneagles Cancer Institute, Bangalore

What Is SBRT For Oligometastatic Lung Cancer?

Stereotactic body radiation therapy (SBRT) for lung cancer is a highly precise, non-invasive treatment that delivers concentrated radiation doses to lung tumors, offering hope even for patients with limited metastatic spread. According to recent studies, SBRT can achieve local control rates of over 85% for selected patients with oligometastatic lung cancer—a condition where a patient has a limited number (typically up to five) of metastatic tumors.

Dr Mathangi, Senior Radiation Oncologist at Gleneagles Cancer Institute, Bangalore, brings over 20 years of experience and global expertise to the forefront of cancer care. Her mastery in SBRT for lung cancer ensures patients in South India, North India, and beyond access world-class, evidence-based care. If you or your loved one faces the challenge of oligometastatic lung cancer, this guide will help you understand why choosing Dr Mathangi’s service could be a life-changing decision.

Why Is SBRT Considered For Oligometastatic Lung Cancer?

Oligometastatic lung cancer represents a clinical state where the disease has spread, but only to a limited extent—typically fewer than five sites. This concept has revolutionized the approach to metastatic cancer, as patients with this diagnosis may benefit from aggressive local therapies like SBRT, which can potentially improve survival and quality of life.

  • SBRT for lung cancer offers a non-surgical, outpatient alternative for patients unfit for surgery.
  • It targets tumors with millimeter precision, sparing healthy tissue and reducing recovery time.
  • The high-dose, short-duration treatment can be completed in as few as 1-5 sessions.

Dr Mathangi’s expertise helps select patients most likely to benefit from this advanced approach, ensuring the best possible outcomes.

How Does Stereotactic Body Radiation Therapy Work?

Stereotactic body radiation therapy uses advanced imaging and planning to deliver focused radiation beams from multiple angles. This process ensures the highest dose to the tumor while minimizing exposure to surrounding organs.

  1. Detailed imaging (CT, MRI, PET) maps the tumor in 3D.
  2. Computerized planning systems create a personalized treatment plan.
  3. Motion management techniques account for tumor movement due to breathing.
  4. Precise radiation delivery occurs over a few brief sessions.

At Gleneagles Cancer Institute, Dr Mathangi employs cutting-edge technology such as TrueBeam STx and Gated RapidArc, offering unmatched accuracy and safety for patients.

What Is The Role Of The SABR-COMET Trial In SBRT For Lung Cancer?

The landmark SABR-COMET trial changed the landscape for treating oligometastatic cancers. This pivotal clinical trial demonstrated that adding SBRT to standard care in patients with oligometastatic disease significantly increased overall survival compared to standard palliative treatments alone.

  • Patients receiving SBRT had a median overall survival of 41 months, compared to 28 months for standard therapy.
  • SBRT also improved progression-free survival and local control rates.
  • The trial validated the use of SBRT for lung cancer in cases of limited metastatic spread.

Dr Mathangi integrates these evidence-based findings into her practice, ensuring her patients receive globally benchmarked care for oligometastatic lung cancer.

How Are Patients Selected For SBRT In Oligometastatic Lung Cancer?

Careful patient selection is vital to maximize the benefits of SBRT for lung cancer. Not every patient is suitable; the decision is based on multiple factors:

  • Number and location of metastases: Typically up to five lesions, all suitable for precise targeting.
  • Overall health and performance status: Patients should be able to tolerate treatment.
  • Pulmonary function assessment: Evaluates lung reserve to ensure safe radiation delivery.
  • Stability of primary and other metastatic sites: Best outcomes are seen when the disease is otherwise stable or controlled.

Dr Mathangi’s comprehensive evaluation process includes advanced imaging, multidisciplinary tumor board discussions, and detailed pulmonary function assessment. This ensures that only those most likely to benefit are offered SBRT, optimizing safety and effectiveness.

How Is Motion Management Critical In Lung SBRT?

Motion management is an essential component in delivering safe and effective SBRT for lung cancer. Because tumors in the lung move as patients breathe, failure to account for this motion can result in missed targets or damage to healthy tissue.

  • Techniques such as respiratory gating, DIBH (deep inspiration breath hold), and real-time tumor tracking are used.
  • Gated RapidArc and advanced imaging ensure sub-millimeter accuracy.
  • Motion management minimizes side effects and maximizes tumor control.

Dr Mathangi’s center is renowned for expertise in motion management, having pioneered the use of advanced gating technologies in the Asia Pacific region.

What Are The Lung SBRT Side Effects?

Understanding lung SBRT side effects is crucial for making an informed decision. While SBRT is generally well tolerated, some potential side effects include:

  • Fatigue: Usually mild and short-lived.
  • Cough or mild chest discomfort: May occur during or after treatment.
  • Radiation pneumonitis: Inflammation of the lung tissue, usually manageable with medication.
  • Rib pain or skin changes: Rare and typically mild.

The risk of severe complications is low when SBRT is administered by an experienced specialist like Dr Mathangi. Her meticulous planning and use of the latest technologies significantly reduce lung SBRT side effects, preserving lung function and quality of life.

What Are The Outcomes Of SBRT For Lung Cancer?

SBRT for lung cancer, especially in oligometastatic cases, has demonstrated excellent outcomes:

Outcome SBRT Result Conventional Therapy
Local Control Rate 85-95% 50-60%
Overall Survival (2 years) 55-70% 30-40%
Treatment Duration 1-2 weeks 6-7 weeks
Quality of Life Maintained/Improved Variable

Dr Mathangi’s patients at Gleneagles Cancer Institute consistently report high satisfaction and excellent functional outcomes, thanks to individualized care and access to the latest treatment protocols.

How To Book An Appointment With Dr Mathangi?

If you or your loved one is exploring options for oligometastatic lung cancer, time is of the essence. The right treatment, delivered by the right hands, can make all the difference. Don’t risk missing out on the most advanced, evidence-based care.

  1. Visit https://drmathangi.com/contact/.
  2. Fill in your contact information in the secure online form.
  3. Dr Mathangi’s team will promptly schedule your appointment and notify you of the details.

About Dr Mathangi

Dr Mathangi J is a Senior Radiation Oncologist and In-charge of the Radiation Oncology Department at Gleneagles Cancer Institute, Bangalore. With over 20 years of experience and advanced international training, she is recognized as a leader in cancer care across South India and North India. Her achievements include pioneering the installation of Asia Pacific’s first TrueBeam STx Machine and directing a prestigious Fellowship in Advanced Radiotherapy Techniques.

  • Expertise in head and neck, brain, spine, lung, liver, breast, bladder, prostate, uterine, cervical, vulval, anal canal, and penile cancers.
  • Over 12,000 patients successfully treated with a focus on patient-centered, precision medicine.
  • Active educator and mentor, shaping the next generation of radiation oncologists through her RGUHS-affiliated fellowship program.

Choosing Dr Mathangi means choosing a globally respected, compassionate, and technologically advanced cancer care provider.

Gleneagles Cancer Institute, Bangalore is a premier cancer center specializing in advanced radiation oncology services. For appointments and more information, visit drmathangi.com.

Frequently Asked Questions

What is SBRT for lung cancer and how is it different from conventional radiation?

SBRT for lung cancer, also known as stereotactic body radiation therapy, is a highly precise form of radiation that delivers very high doses to lung tumors over a few sessions (typically 3 to 5). Unlike conventional radiation, which is usually given over several weeks, SBRT targets tumors with sub-millimeter accuracy, sparing healthy tissue and reducing side effects. Dr. Mathangi utilizes advanced SBRT techniques to ensure optimal outcomes for patients with early-stage or oligometastatic lung cancer.

Who is an ideal candidate for SBRT in oligometastatic lung cancer?

Patients with oligometastatic lung cancer—meaning those with a limited number (usually up to 5) of metastatic lesions—may benefit from SBRT. Ideal candidates are those with controlled primary tumors, good overall health, and limited metastases that are safely accessible for radiation. Dr. Mathangi performs thorough evaluations, including imaging and pulmonary function assessment, to determine suitability and personalize treatment.

What evidence supports the use of stereotactic body radiation therapy for oligometastatic lung cancer?

The SABR-COMET trial provided strong evidence that stereotactic body radiation therapy (SBRT) improves survival and disease control in patients with oligometastatic cancer, including those with lung metastases. This landmark study demonstrated that aggressive local treatment like SBRT, when combined with systemic therapies, can offer meaningful survival benefits. Dr. Mathangi incorporates the latest evidence and guidelines to recommend SBRT when it is most likely to benefit each patient.

How does Dr. Mathangi assess pulmonary function before lung SBRT?

Pulmonary function assessment is a key step before proceeding with lung SBRT. Dr. Mathangi arranges for comprehensive lung function tests (such as spirometry and diffusion capacity) to evaluate if the patient’s lungs can safely tolerate radiation. This assessment helps tailor the treatment plan, minimize lung SBRT side effects, and ensure the best possible results for each individual.

What role does motion management play in SBRT for lung cancer?

Motion management is crucial in SBRT for lung cancer because tumors can move with breathing. Dr. Mathangi uses advanced imaging, 4D-CT scans, and real-time tracking techniques to ensure the radiation precisely targets the tumor during each breath cycle. Effective motion management reduces risks to healthy lung tissue and maximizes the safety and effectiveness of the treatment.

What are the common lung SBRT side effects and how are they managed?

Lung SBRT side effects are generally mild and may include fatigue, cough, mild chest discomfort, or shortness of breath. Occasionally, more serious effects like pneumonitis or rib fractures can occur. Dr. Mathangi takes proactive steps to minimize these risks through careful planning, personalized dosing, and regular follow-up. Most patients tolerate SBRT very well and recover quickly.

What kind of outcomes can patients expect after SBRT for oligometastatic lung cancer?

Patients treated with SBRT for oligometastatic lung cancer can expect excellent local control rates—often exceeding 85%—and potential improvements in overall survival, as supported by studies like the SABR-COMET trial. With Dr. Mathangi’s expertise and multidisciplinary approach, many patients experience durable disease control with minimal impact on quality of life.

How does Dr. Mathangi personalize SBRT treatment selection for lung cancer patients?

Dr. Mathangi customizes SBRT for lung cancer by considering tumor size, location, number of metastases, lung function, and patient preferences. She collaborates with a multidisciplinary team to ensure the treatment plan is evidence-based and tailored to each patient’s situation, maximizing benefits while minimizing risks.

Is SBRT an option for patients who cannot undergo surgery for lung metastases?

Yes, SBRT offers an effective, non-invasive alternative for patients with lung metastases who are not surgical candidates due to medical reasons or personal choice. Under Dr. Mathangi’s care, SBRT is delivered with precision and safety, providing a curative option for select individuals with oligometastatic lung cancer.


Latest AACR 2026 ctDNA Research & Radiation Oncology Trends

In 2024, over 19 million new cancer cases were diagnosed worldwide, and cutting-edge research is rapidly transforming how oncologists detect, monitor, and treat cancer. AACR 2026 ctDNA research is at the forefront of this revolution, offering unprecedented insights into tumor biology and paving the way for personalized cancer care. Under the leadership of Dr. Mathangi, Senior Consultant & In-charge of Radiation Oncology at Gleneagles Cancer Institute, Bangalore, patients can access these latest advancements — ensuring world-class outcomes and hope for thousands of families.

What Is AACR 2026 ctDNA Research?

AACR 2026 ctDNA research refers to the latest studies and advancements presented at the American Association for Cancer Research (AACR) annual meeting, focusing on circulating tumor DNA (ctDNA) as a biomarker for cancer. ctDNA are small fragments of DNA shed from tumors into the bloodstream, and their analysis is transforming cancer diagnosis, monitoring, and treatment stratification.

  • Non-invasive cancer monitoring: ctDNA allows for “liquid biopsy” through a simple blood sample, reducing the need for surgical biopsies.
  • Early detection: By identifying tumor-specific mutations, ctDNA can detect cancer earlier than imaging in some cases.
  • Real-time tracking: ctDNA reflects the dynamic nature of tumors, enabling oncologists to monitor response to therapy and detect relapse sooner.

The AACR 2026 meeting has spotlighted clinical trials where ctDNA guided therapy decisions, improving both survival rates and quality of life. These breakthroughs are now being integrated into everyday practice by visionaries like Dr. Mathangi in Bangalore.

How Is ctDNA Changing Radiation Oncology?

Radiation oncologists are leveraging AACR 2026 ctDNA research to personalize care like never before. Here’s how ctDNA is being used to revolutionize radiation oncology:

  1. Risk-adapted therapy: ctDNA levels before, during, and after radiotherapy help identify which patients need intensified treatment or can safely de-escalate therapy.
  2. Early detection of recurrence: Regular ctDNA monitoring allows for prompt intervention if cancer returns, significantly improving survival chances.
  3. Treatment response prediction: ctDNA mutations can predict sensitivity or resistance to specific radiation techniques or combined therapies.

Dr. Mathangi integrates these protocols, ensuring that each patient benefits from the latest science-backed strategies, truly exemplifying precision oncology.

What Are The Latest Cancer Research Updates From AACR?

The field of oncology is evolving rapidly, with several cancer research updates from the AACR 2026 meeting reshaping clinical practice. Among the most impactful are:

  • Multi-cancer early detection (MCED): Liquid biopsy panels using ctDNA can screen for several cancers simultaneously, improving early diagnosis rates.
  • Integration with immunotherapy: ctDNA is being used to select patients most likely to benefit from immunotherapy, especially in lung and bladder cancers.
  • Adaptive radiotherapy: Real-time ctDNA monitoring enables clinicians to adjust radiation plans based on tumor evolution.
  • Minimal residual disease (MRD) detection: Ultra-sensitive ctDNA assays can detect residual disease post-treatment, guiding adjuvant therapy decisions.

These advances are particularly vital for cancers that need RT (radiation therapy), including head and neck cancers, brain tumors, spine tumors, esophagus and rectal cancers, lung cancers, liver cancers, breast cancers, bladder cancers, prostate cancers, uterine cancers, cervical cancer, vulval cancers, anal canal cancers, and penile cancers.

Cancers That Benefit Most From ctDNA-Guided Radiation Therapy
Cancer Type Role of ctDNA Radiation Modality
Head & Neck Early relapse detection, risk stratification IMRT, SBRT
Brain Tumors Tumor monitoring, response assessment SRS, Image-guided RT
Lung Therapy response, MRD detection SBRT, Gated RapidArc
Breast Minimal residual disease, adaptive therapy DIBH Gated RT, IORT
Prostate Personalized follow-up, recurrence monitoring IGRT, Brachytherapy

Why Is The Liquid Biopsy Symposium Transforming Oncology?

The liquid biopsy symposium at AACR 2026 has underscored the paradigm shift in cancer diagnostics and monitoring. Unlike traditional biopsies, liquid biopsy analyzes ctDNA and other tumor-derived materials from blood or other body fluids, offering:

  • Minimal invasiveness: Reduced procedural risk and discomfort for patients.
  • Frequent sampling: Enables real-time tracking of tumor evolution and heterogeneity.
  • Comprehensive profiling: Detects multiple genetic alterations that drive cancer progression and therapy resistance.

At Gleneagles Cancer Institute, Dr. Mathangi ensures that eligible patients have access to these innovations, supported by collaborations with leading laboratories and research networks.

How Are Oncology Innovation Trends Shaping The Future?

With the rise of oncology innovation trends, the future of cancer therapy is more hopeful than ever. Key trends highlighted at AACR 2026 include:

  1. Artificial intelligence in radiotherapy: AI-driven planning tools now optimize dose distribution, reduce side effects, and accelerate treatment times.
  2. Integration of genomics and radiomics: Combining genetic data (like ctDNA) and imaging features for a holistic approach to therapy planning.
  3. Personalized radiotherapy: Adaptive protocols tailored to the unique tumor biology of each patient, as revealed by liquid biopsy and imaging.
  4. Combination regimens: Novel protocols combining radiation, immunotherapy, and targeted agents for synergistic effects.

Dr. Mathangi’s leadership has positioned Gleneagles Cancer Institute as a pioneer in adopting these trends, evidenced by the installation of Asia Pacific’s first TrueBeam STx Machine and the routine use of advanced techniques such as Stereotactic Ablative Body Radiotherapy (SBRT), Gated RapidArc, DIBH Gated RT, and image-guided Interstitial Brachytherapy.

What Sets Dr. Mathangi Apart In Advanced Radiation Oncology?

Dr. Mathangi J is a recognized authority in radiation oncology, with over 20 years of experience and a track record of 12,000+ successfully treated patients. Her expertise spans:

  • State-of-the-art stereotactic techniques (SRS/SBRT)
  • International training in IGRT/RapidArc and Intraoperative Radiotherapy (IORT)
  • Expertise in cancers of the head and neck, prostate, brain, lung, and women’s cancers (breast, cervix, endometrium)
  • Directorship in advanced radiotherapy fellowship programs, nurturing the next generation of oncologists

Patients under Dr. Mathangi’s care benefit from her relentless pursuit of excellence, empathy, and a patient-centric approach that integrates the latest AACR 2026 ctDNA research, cancer research updates, and oncology innovation trends.

How To Book An Appointment With Dr. Mathangi?

If you or a loved one is seeking the best in cancer care — from the most recent AACR 2026 ctDNA research insights to groundbreaking radiation oncology — trust your journey with Dr. Mathangi at Gleneagles Cancer Institute, Bangalore. To book an appointment:

  1. Visit this appointment form and submit your contact details.
  2. Dr. Mathangi’s dedicated team will promptly schedule your consultation and notify you of the appointment date.

Secure your place at the forefront of cancer innovation — because when it comes to your health, only the best will do.

Don’t miss out on the future of cancer care.
Book your consultation with Dr. Mathangi now and access the latest AACR 2026 ctDNA research and oncology breakthroughs in Bangalore.

About Dr Mathangi

Dr. Mathangi J is a Senior Radiation Oncologist and In-charge of Gleneagles Cancer Institute, Bangalore, India. She is widely recognized for her expertise in advanced radiation therapy and is a trailblazer in integrating global oncology innovations into Indian clinical practice. Her qualifications (MBBS, DMRT, DNB) and international training set her apart as a leader in cancer care across South and North India.
Gleneagles Cancer Institute is a premier institution, offering comprehensive and compassionate cancer treatment backed by state-of-the-art technology and a multidisciplinary team.

To know more or to book your appointment, visit drmathangi.com.


Frequently Asked Questions

What are the main highlights from the AACR 2026 ctDNA research for radiation oncology?

The AACR 2026 ctDNA research has showcased several pivotal advancements in the use of circulating tumor DNA for monitoring treatment response and minimal residual disease in radiation oncology. These insights are fueling more precise, personalized cancer therapies. Dr. Mathangi integrates these breakthroughs into her clinical practice, enabling earlier intervention and adaptive treatment planning for her patients.

How is ctDNA changing the landscape of cancer monitoring and treatment?

ctDNA provides a minimally invasive method to track tumor genetics and evolution over time. This allows for dynamic monitoring of disease progression, early detection of relapse, and the ability to tailor radiation doses. Dr. Mathangi employs ctDNA assessments, as discussed in the latest cancer research updates, to refine patient care and enable real-time, evidence-driven decisions.

What was discussed at the recent liquid biopsy symposium relevant to radiation oncology?

The liquid biopsy symposium highlighted the expanding role of non-invasive tests like ctDNA in treatment planning and surveillance. For radiation oncologists, these tools enhance the ability to personalize therapy and monitor response without repeated tissue biopsies. Dr. Mathangi incorporates such methodologies to improve accuracy and patient comfort throughout the treatment journey.

What oncology innovation trends are shaping the future of radiation therapy?

Key oncology innovation trends include the integration of genomics with imaging, the application of artificial intelligence in treatment planning, and the adoption of liquid biopsy technologies like ctDNA. Dr. Mathangi stays at the forefront by leveraging these innovations to offer highly targeted and effective radiation treatments that are informed by the very latest in cancer research updates.

How does Dr. Mathangi apply AACR 2026 ctDNA research insights in her clinical practice?

Dr. Mathangi uses the latest data from AACR 2026 ctDNA research to guide evidence-based decisions for her radiation oncology patients. By applying these findings, she can stratify risk, monitor minimal residual disease, and personalize follow-up protocols, ultimately enhancing patient outcomes and reducing unnecessary interventions.

What solutions does Dr. Mathangi offer for patients seeking advanced cancer monitoring?

Dr. Mathangi provides comprehensive cancer monitoring solutions, including regular ctDNA testing, integration of advanced imaging, and personalized surveillance plans. These services are based on the latest oncology innovation trends and cancer research updates, ensuring that patients receive the most current and effective care available.

How can liquid biopsy improve the accuracy of radiation oncology treatments?

Liquid biopsy, as discussed in recent symposiums, enables precise detection of tumor DNA in the bloodstream. This allows for ongoing assessment of tumor dynamics, facilitating rapid adjustments to radiation therapy. Dr. Mathangi incorporates liquid biopsy findings to fine-tune treatment plans and minimize unnecessary exposure to radiation.

What are the benefits of integrating ctDNA analysis in routine cancer care?

Integrating ctDNA analysis allows for earlier detection of recurrence, better risk stratification, and real-time monitoring of therapeutic efficacy. Dr. Mathangi leverages this technology, as highlighted in AACR 2026 ctDNA research, to provide her patients with proactive and personalized treatment strategies.

Where can patients learn more about the latest cancer research updates and Dr. Mathangi’s approach?

Patients are encouraged to explore Dr. Mathangi’s blog and attend upcoming webinars, where she shares insights from cancer research updates, major events like the liquid biopsy symposium, and the most relevant oncology innovation trends. These resources empower patients with knowledge about cutting-edge advancements in radiation oncology.


Complete Guide to Liquid Biopsy & ctDNA Testing for Cancer Patients


Did you know?
According to recent global studies, over 2 million cancer patients have already benefited from liquid biopsy and ctDNA-based cancer blood tests, revolutionizing how cancer is diagnosed and monitored. In India, the adoption of these advanced molecular diagnostics is rapidly improving outcomes for patients who want safer, more personalized, and less invasive cancer care.

What Is Liquid Biopsy And Why Is It Transforming Cancer Care?

Liquid biopsy is a game-changing, minimally invasive diagnostic tool that uses a simple blood sample to detect and analyze genetic material from tumors. Unlike traditional biopsies, which require tissue extraction through surgery or needle insertion, liquid biopsies evaluate circulating tumor DNA (ctDNA) and other biomarkers in your blood. This means no pain, faster results, and the potential to catch changes in your cancer earlier than ever before.

  • Quick, safe, and repeatable – no surgical risks or recovery time.
  • Monitors your cancer’s genetic evolution in real time.
  • Guides targeted treatment and detects resistance early.

For patients treated by Dr Mathangi at Gleneagles Cancer Institute, Bangalore, these cutting-edge techniques are now a core part of advanced, personalized oncology care.

How Does Liquid Biopsy Work? (Complete Guide To Liquid Biopsy)

The complete guide to liquid biopsy begins with understanding how this technology harnesses the power of your blood to provide actionable cancer insights:

  1. Blood Sample Collection: A small tube of blood is drawn, usually from your arm.
  2. ctDNA & Biomarker Isolation: Specialized labs extract circulating tumor DNA (ctDNA) and other cancer-related materials.
  3. Next-Generation Sequencing: High-precision sequencing identifies genetic mutations and alterations linked to your cancer.
  4. Data Interpretation: Results are analyzed to guide diagnosis, monitor response to treatment, and predict potential relapses.

Why is this important? Liquid biopsy can provide actionable results within days, allowing Dr Mathangi to fine-tune your treatment plan without waiting for invasive procedures or tissue samples.

What Is ctDNA And How Does It Help Cancer Patients? (ctDNA Guide)

The ctDNA guide focuses on circulating tumor DNA, a hallmark fragment of genetic material shed by cancer cells into the bloodstream. By analyzing ctDNA, doctors like Dr Mathangi can:

  • Track cancer burden: Quantify how much ctDNA is present, reflecting the size or activity of the tumor.
  • Detect recurrence early: Spot relapses before symptoms or imaging changes appear.
  • Understand resistance: Identify new mutations that may make your cancer resistant to certain drugs.
  • Personalize therapy: Choose targeted treatments based on your tumor’s current genetic profile.

For patients under radiation oncology monitoring, ctDNA provides a sensitive, real-time window into how well therapy is working, and if adjustments are needed.

What Are The Key Advantages Of Cancer Blood Tests Compared To Traditional Biopsies?

Cancer blood tests like liquid biopsy offer several crucial benefits over surgical or needle-based tissue biopsies, especially for patients needing repeated monitoring:

  • Less invasive: Only a blood draw, reducing pain, risk, and recovery time.
  • Comprehensive: Captures information from the whole body, not just a single tumor site.
  • Frequent monitoring: Enables repeated testing throughout your treatment journey.
  • Early detection: Catches molecular changes before they appear on scans.
  • Cost-effective: Reduces the need for expensive, risky procedures.

These tests are especially valuable for hard-to-reach tumors like brain, spine, and lung cancers, or when repeated biopsies are not feasible.

How Is Molecular Diagnostics Personalizing Cancer Treatment?

Molecular diagnostics represent the future of cancer care. By decoding the genetic makeup of your tumor through blood, doctors like Dr Mathangi can:

  • Predict response: Identify which therapies are most likely to work for you.
  • Monitor resistance: Detect changes that suggest your cancer is escaping current treatment.
  • Guide new options: Suggest clinical trials or new drugs based on emerging mutations.

Personalized medicine is no longer a dream—it's a reality for patients at Gleneagles Cancer Institute, Bangalore, thanks to advanced molecular diagnostics.

What Cancers Benefit Most From Radiation Oncology Monitoring And Liquid Biopsy?

Radiation oncology monitoring with liquid biopsy is particularly impactful for:

  • Head and neck cancers
  • Brain tumors
  • Spine tumors
  • Esophagus and rectal cancers
  • Lung cancers
  • Liver cancers
  • Breast cancers
  • Bladder cancers
  • Prostate cancers
  • Uterine cancers
  • Cervical cancer
  • Vulval cancers
  • Anal canal cancers
  • Penile cancers

For these cancers, repeat blood-based monitoring allows for timely adjustments in treatment, rapid detection of relapse, and improved overall survival.

Why Should You Choose Dr Mathangi For Liquid Biopsy & ctDNA Testing?

Dr Mathangi J is a Senior Consultant and In-charge of Radiation Oncology at Gleneagles Cancer Institute, Bangalore—one of India's top cancer centers. With over 20 years of experience and 12,000+ patients treated, she is a pioneer in integrating advanced technologies like:

  • Stereotactic ablative body radiotherapy (SBRT)
  • Gated RapidArc and DIBH gated radiotherapy
  • Image-guided interstitial brachytherapy
  • Asia Pacific’s first TrueBeam STx Machine installation

Dr Mathangi’s expertise means you get the best of clinical experience, cutting-edge research, and compassionate care. She specializes in cancers where liquid biopsy and ctDNA monitoring are most impactful, ensuring your diagnosis and treatment are always at the forefront of science.

Book Your Appointment With Dr Mathangi Today

What Is The Process For Getting A Liquid Biopsy Or ctDNA Test At Gleneagles Cancer Institute?

Here is a step-by-step overview for patients in Bangalore and across India:

  1. Consultation: Meet with Dr Mathangi to assess your suitability and discuss the goals of testing.
  2. Blood Collection: A blood sample is taken at the institute’s advanced diagnostics lab.
  3. Analysis: The sample undergoes high-sensitivity ctDNA or other molecular diagnostics.
  4. Results & Discussion: Dr Mathangi discusses your results, implications, and next steps in a personalized care plan.

To get started, simply submit your contact information here, and Dr Mathangi’s team will promptly schedule your appointment.

How Do Liquid Biopsy And ctDNA Testing Compare To Traditional Methods?

Feature Liquid Biopsy & ctDNA Traditional Biopsy
Invasiveness Minimally invasive (blood draw) Invasive (surgery/needle)
Repeatability Can be repeated frequently Rarely repeatable
Turnaround Time Days Weeks
Whole-Body Assessment Yes No (local sample only)
Detects Resistance Early Yes Limited
Risk Low Higher (infection, bleeding, complications)

What Should Patients In India Know About Accessing Liquid Biopsy And ctDNA Testing?

Access to advanced molecular diagnostics is expanding rapidly in India. Bangalore’s Gleneagles Cancer Institute, under Dr Mathangi’s leadership, is helping set national standards for precision oncology. Here’s why Indian patients should consider these tests:

  • Improved outcomes: Early relapse detection and personalized treatment options.
  • Fewer hospital visits: Less need for invasive procedures and faster recovery times.
  • Global-standard care: Access to the same technology used in leading cancer centers worldwide.

Don’t wait for cancer to change—let your treatment adapt first with liquid biopsy and ctDNA monitoring.

Schedule Your Personalized Cancer Blood Test With Dr Mathangi

About Dr Mathangi

Dr Mathangi J, Senior Radiation Oncologist

Dr Mathangi J is a Senior Consultant & In-charge of Radiation Oncology at Gleneagles Cancer Institute, Bangalore. With expertise honed at premier global institutes and over 20 years of experience, she specializes in head and neck, prostate, brain, lung, and women’s cancers. Dr Mathangi is celebrated for her leadership in advanced radiotherapy and precision diagnostics, offering hope and world-class care to thousands of patients across South and North India.

Don’t let outdated diagnostics hold back your fight against cancer. Trust Dr Mathangi for the most advanced care in India. Book your appointment today and experience the difference.

Frequently Asked Questions

What is a liquid biopsy and how does it work for cancer patients?

A liquid biopsy is a minimally invasive test that detects cancer-related genetic material—such as circulating tumor DNA (ctDNA)—in a blood sample. This approach allows for real-time monitoring of a patient's cancer without the need for traditional surgical biopsies. Dr. Mathangi provides a complete guide to liquid biopsy, helping patients understand how these tests can be used for early detection, treatment response, and surveillance of cancer progression.

How does ctDNA testing differ from other cancer blood tests?

ctDNA testing specifically analyzes fragments of DNA shed by cancer cells into the bloodstream, providing detailed genetic information about the tumor. Unlike routine cancer blood tests that may look for proteins or general markers, ctDNA tests offer a high level of specificity and sensitivity for detecting mutations and monitoring minimal residual disease. For comprehensive information, Dr. Mathangi’s ctDNA guide outlines the benefits and applications of this advanced testing method.

What types of cancers can be monitored using liquid biopsy?

Liquid biopsy can be used to monitor a wide range of solid tumors, including lung, breast, colorectal, and prostate cancers. Its utility is expanding as research advances. Dr. Mathangi works closely with patients to determine if liquid biopsy is appropriate based on the type and stage of cancer, ensuring personalized and precise care.

Why are molecular diagnostics important in cancer treatment?

Molecular diagnostics allow doctors to analyze the genetic and molecular features of a tumor, enabling customized treatment plans. By identifying specific mutations or biomarkers, therapies can be tailored for maximum effectiveness and minimal side effects. Dr. Mathangi incorporates advanced molecular diagnostics, including ctDNA analysis, to guide targeted therapies and improve patient outcomes.

How can liquid biopsy help in radiation oncology monitoring?

Liquid biopsy offers a non-invasive way to track tumor response during and after radiation therapy. By measuring ctDNA levels, oncologists like Dr. Mathangi can assess treatment effectiveness, detect early signs of recurrence, and modify therapy plans as needed. This approach enhances precision in radiation oncology monitoring and supports timely clinical decisions.

What are the advantages of choosing Dr. Mathangi for liquid biopsy and ctDNA testing?

Dr. Mathangi offers expert guidance through the entire process of liquid biopsy and ctDNA testing, from initial consultation to interpreting results and integrating findings into personalized treatment plans. Her approach is patient-centered, using the latest molecular diagnostics to ensure that each patient receives the most precise and effective cancer care available.

Is liquid biopsy safe and how often should it be performed?

Liquid biopsy is a safe and low-risk procedure, requiring only a standard blood draw. The frequency of testing depends on the cancer type, treatment phase, and clinical objectives. Dr. Mathangi develops individualized monitoring schedules, ensuring that liquid biopsy is used optimally to inform care without unnecessary procedures.

Can liquid biopsy replace traditional tissue biopsy?

While liquid biopsy is a powerful tool, it may not completely replace tissue biopsy in all cases. Tissue biopsies can provide detailed information about tumor histology and microenvironment. However, liquid biopsy, as detailed in the complete guide to liquid biopsy, offers complementary insights—especially for ongoing monitoring and when tissue samples are hard to obtain. Dr. Mathangi guides patients on the best approach based on individual needs.

How can I get started with ctDNA testing and liquid biopsy through Dr. Mathangi?

To get started, book a consultation with Dr. Mathangi. She will review your medical history, discuss the benefits of ctDNA and other cancer blood tests, and recommend the most suitable molecular diagnostics for your cancer type. Her personalized approach ensures that each patient receives state-of-the-art care and support from diagnosis through every stage of treatment and follow-up.


RapidArc VMAT vs IMRT for Head and Neck Cancer Treatment


What is the difference between RapidArc VMAT and IMRT for head and neck cancer radiation?
RapidArc radiation therapy (a form of volumetric modulated arc therapy or VMAT) and intensity-modulated radiation therapy (IMRT) are both advanced techniques for treating head and neck cancers. However, RapidArc VMAT delivers highly conformal doses in less time, improving patient comfort and potentially reducing side effects.

According to the World Health Organization, head and neck cancers account for over 550,000 cases and 380,000 deaths annually worldwide, making them a major global health concern. Radiation therapy is a critical component of curative management, with nearly 80-90% of patients requiring it as part of their treatment regimen. Choosing the right radiation technique can greatly impact treatment outcomes and quality of life.

Why is advanced head and neck cancer radiation important?

Head and neck cancer radiation requires extreme precision due to the proximity of vital structures like the spinal cord, salivary glands, and optic nerves. The main challenge is to eradicate cancer cells while minimizing damage to healthy tissues, thereby reducing complications like xerostomia (dry mouth), swallowing difficulties, and long-term toxicity.

  • Preserves speech and swallowing functions
  • Minimizes treatment-related disfigurement
  • Improves long-term quality of life after cancer cure

What is RapidArc radiation therapy?

RapidArc radiation therapy is a state-of-the-art treatment method that uses volumetric modulated arc therapy (VMAT) to deliver radiation quickly and precisely. Unlike conventional IMRT, which delivers radiation from fixed angles, RapidArc VMAT rotates around the patient, adjusting the dose rate and beam shape in real time. This results in highly conformal dose delivery in a much shorter time.

  • Shorter treatment times (typically 2-4 minutes per session)
  • Greater patient comfort and reduced movement
  • Enhanced dose conformity and sparing of healthy tissues

How does VMAT vs IMRT compare for head and neck cancers?

The debate of VMAT vs IMRT centers on which technique offers superior outcomes in terms of tumor control, toxicity, and patient experience. Here’s a concise comparison:

Parameter IMRT RapidArc VMAT
Dose conformity High Very high
Treatment time 10-20 minutes 2-4 minutes
Parotid gland sparing Good Excellent
Xerostomia prevention Effective More effective
Salivary gland toxicity Moderate Low
Patient comfort Moderate High

In summary, RapidArc VMAT offers superior dose conformity, faster treatments, and better sparing of critical structures, which is especially important for head and neck cancer radiation.

What are the benefits of parotid gland sparing and xerostomia prevention?

Parotid gland sparing is a key objective in head and neck cancer radiation, as these glands are responsible for producing saliva. Radiation-induced damage can result in xerostomia, a debilitating side effect that affects speech, taste, swallowing, and oral health.

  • Xerostomia prevention: Reduces risk of dental decay, oral infections, and nutritional deficiencies.
  • Parotid gland sparing: Preserves natural saliva production, improving long-term quality of life.
  • Lower salivary gland toxicity: Minimizes irreversible gland damage and associated complications.

RapidArc radiation therapy, through advanced volumetric modulated arc therapy planning, achieves remarkable parotid gland sparing, translating to better xerostomia prevention compared to traditional IMRT.

How does dose conformity impact treatment outcomes?

Dose conformity refers to how closely the radiation dose matches the tumor’s shape while avoiding healthy tissues. High dose conformity is crucial in head and neck cancer radiation to:

  • Maximize tumor control and local cure rates
  • Minimize radiation exposure to normal tissues
  • Reduce acute and long-term side effects, such as salivary gland toxicity and swallowing difficulties

RapidArc VMAT’s unique delivery allows for exceptional dose conformity, ensuring that even complex-shaped tumors receive optimal coverage with the least collateral damage.

Why choose Dr Mathangi for RapidArc radiation therapy?

Dr Mathangi J, Senior Consultant & In-charge of Radiation Oncology at Gleneagles Cancer Institute, Bangalore, is a pioneer in advanced radiation techniques. With over 20 years of experience and more than 12,000 patients successfully treated, she brings unmatched expertise in head and neck cancer radiation, including RapidArc radiation therapy and volumetric modulated arc therapy.

  • Asia Pacific’s first installation of the TrueBeam STx Machine
  • International training in IGRT/RapidArc (Denmark) and Stereotactic techniques (Germany)
  • Director of Fellowship in Advanced Radiotherapy Techniques (RGUHS-affiliated)
  • Leader in Gated RapidArc, SBRT, DIBH gated radiotherapy, and image-guided interstitial brachytherapy

Her leadership at Gleneagles Cancer Institute ensures that patients receive the latest and most effective treatments, emphasizing patient safety, comfort, and outcomes.

How do I book an appointment for advanced head and neck cancer radiation?

To access cutting-edge therapies like RapidArc radiation therapy and volumetric modulated arc therapy for head and neck cancer, schedule a consultation with Dr Mathangi. Simply submit your contact information via the appointment request form on her official website. Dr Mathangi’s team will promptly reach out to confirm your appointment and guide you through the next steps.

What cancers need radiation therapy?

Dr Mathangi specializes in treating a broad range of cancers that benefit from advanced radiation therapy, including:

  • Head and neck cancers
  • Brain tumors
  • Spine tumors
  • Esophagus and rectal cancers
  • Lung cancers
  • Liver cancers
  • Breast cancers
  • Bladder cancers
  • Prostate cancers
  • Uterine cancers
  • Cervical cancer
  • Vulval cancers
  • Anal canal cancers
  • Penile cancers

With a patient-centric approach, individualized plans, and the latest in radiotherapy technology, Dr Mathangi delivers unparalleled cancer care in South India.

About Dr Mathangi

Dr Mathangi J is a renowned Senior Radiation Oncologist and In-charge at Gleneagles Cancer Institute, Bangalore. She holds an MBBS, DMRT, and DNB, with advanced international training in stereotactic and image-guided radiation techniques. Dr Mathangi is recognized for her contributions to radiation oncology, leadership in cancer care innovation, and her commitment to patient outcomes.

Gleneagles Cancer Institute, part of Gleneagles Hospitals, is a premier institution equipped with world-class technology and multidisciplinary expertise, offering comprehensive cancer care in Bangalore and the broader South and North India regions.

Take the next step towards advanced cancer care

If you or your loved one is seeking the most effective, comfortable, and advanced head and neck cancer radiation, do not miss the opportunity to consult with Dr Mathangi. Experience the advantage of RapidArc radiation therapy and volumetric modulated arc therapy under the guidance of a leader in the field.

Book your appointment today at drmathangi.com/contact/ and give yourself the best chance at a cure with optimal quality of life.

Frequently Asked Questions

What is the difference between RapidArc radiation therapy (VMAT) and IMRT for head and neck cancer?

RapidArc radiation therapy is a specific implementation of volumetric modulated arc therapy (VMAT), which delivers radiation in a continuous arc around the patient. In contrast, Intensity-Modulated Radiation Therapy (IMRT) delivers radiation from several fixed angles. The main advantage of VMAT vs IMRT is that VMAT often results in faster treatment times and can offer better dose conformity—shaping the radiation more precisely to the tumor—while sparing surrounding healthy tissues. Dr. Mathangi utilizes both techniques, tailoring the choice to maximize tumor control and minimize side effects such as salivary gland toxicity.

How does VMAT help with parotid gland sparing during head and neck cancer radiation?

VMAT, including RapidArc radiation therapy, allows for highly precise targeting of the tumor while shaping the radiation dose to avoid critical structures like the parotid glands. This parotid gland sparing approach reduces the risk of damage to these glands, which are responsible for producing saliva. Dr. Mathangi prioritizes these advanced planning techniques to protect salivary gland function and improve patients' quality of life during and after treatment.

Can VMAT or RapidArc reduce the long-term risk of xerostomia in head and neck cancer patients?

Yes, both VMAT and RapidArc radiation therapy are designed to minimize the dose delivered to salivary glands, which is crucial for xerostomia prevention. By sparing these glands, the risk of chronic dry mouth (xerostomia) is significantly reduced. Dr. Mathangi's treatment planning emphasizes this benefit, helping patients maintain better oral health and comfort post-treatment.

How does dose conformity differ between VMAT (RapidArc) and IMRT?

Dose conformity refers to how closely the radiation dose matches the shape of the tumor. VMAT, including RapidArc radiation therapy, often achieves higher dose conformity compared to traditional IMRT, especially for complex targets in the head and neck. This means the tumor receives the prescribed dose more precisely, while healthy tissues and organs at risk receive less exposure. Dr. Mathangi leverages these advantages to optimize outcomes for her patients.

What are the benefits of VMAT vs IMRT in terms of treatment time and patient comfort?

One of the major benefits of VMAT vs IMRT is reduced treatment time. VMAT delivers radiation in a continuous arc, often completing a session in just a few minutes, compared to the longer sessions required by IMRT. This not only improves patient comfort but also reduces the likelihood of movement during treatment, ensuring greater precision. Dr. Mathangi's clinic offers both options, selecting the best fit for each individual's needs.

How does Dr. Mathangi approach salivary gland toxicity during head and neck cancer radiation?

Dr. Mathangi uses advanced techniques like volumetric modulated arc therapy to minimize radiation exposure to the salivary glands, thereby reducing the risk of salivary gland toxicity. Her personalized planning ensures the best possible tumor control while protecting quality of life, with a strong focus on parotid gland sparing and xerostomia prevention throughout the treatment course.

Is RapidArc radiation therapy suitable for all head and neck cancer patients?

While RapidArc radiation therapy is highly effective for many patients with head and neck cancer, the suitability depends on individual tumor characteristics, location, and patient health. Dr. Mathangi evaluates each case carefully to determine whether RapidArc (VMAT), IMRT, or another approach will provide the best outcome with the least side effects.

What makes Dr. Mathangi’s approach to head and neck cancer radiation unique?

Dr. Mathangi combines the latest technology in volumetric modulated arc therapy and IMRT with a patient-centric approach. Her meticulous planning emphasizes dose conformity, parotid gland sparing, and xerostomia prevention. She actively monitors for salivary gland toxicity and adapts treatments as needed, ensuring optimal tumor control and a better quality of life for her patients.


Modern Image-Guided Brachytherapy (IGBT) for Cervical Cancer Stage II and IIIB


Quick Answer:
Modern image-guided brachytherapy (IGBT) for cervical cancer stage II and IIIB combines advanced imaging and precise radiation delivery to maximize tumor control while minimizing side effects. Dr Mathangi J in Bangalore leverages global best practices, including HDR brachytherapy and MRI-guided planning, to achieve superior outcomes for women with these stages of cervical cancer.

According to the World Health Organization, cervical cancer is the fourth most common cancer among women globally, with over 600,000 new cases each year. In India, it remains a leading cause of cancer-related deaths in women. The majority of patients present in locally advanced stages, underscoring the critical need for effective, precise therapies like modern image-guided brachytherapy (IGBT). As a pioneer in cervical cancer radiation therapy, Dr Mathangi J at Gleneagles Cancer Institute, Bangalore, is redefining treatment standards with cutting-edge technology and compassionate expertise.

What Is Modern Image-Guided Brachytherapy (IGBT) For Cervical Cancer?

Modern image-guided brachytherapy (IGBT) for cervical cancer is an advanced radiation technique that delivers high doses of radiation directly to the cervix and surrounding tissues using internal applicators. Unlike traditional methods, IGBT uses real-time imaging—such as MRI or CT scans—to precisely target the tumor, sparing healthy tissue and reducing complications. This approach is especially vital for stage II and IIIB cervical cancers, where the tumor may have spread into the surrounding pelvic area.

  • IGBT: Combines imaging (MRI/CT) with internal radiation.
  • Higher precision: Targets tumor while minimizing exposure to bladder, rectum, and other organs.
  • Improved outcomes: Better tumor control and fewer long-term side effects.

How Does Brachytherapy For Cervical Cancer Work?

Brachytherapy for cervical cancer involves placing a radioactive source close to or inside the tumor using specialized applicators. This allows for a high, localized dose of radiation, maximizing tumor destruction while limiting damage to surrounding tissues.

Step Action
1. Applicator Placement Insertion of tandem and ring applicator or other devices into the uterus and vagina.
2. Imaging MRI or CT scans to confirm accurate placement and assess tumor size and location.
3. Treatment Planning MRI-guided planning creates a customized radiation plan targeting the tumor and sparing healthy tissue.
4. Radiation Delivery HDR brachytherapy or other techniques deliver prescribed radiation dose in one or more sessions.
5. Follow-up Removal of applicator and post-treatment monitoring.

Why Is Image-Guided Brachytherapy The Gold Standard For Cervical Cancer Radiation Therapy?

Image-guided brachytherapy has revolutionized cervical cancer radiation therapy by enhancing accuracy, efficacy, and safety. For stage II and IIIB disease, where the tumor may invade the parametrium or pelvic wall, precision is crucial for cure and preserving quality of life.

  • Personalized Treatment: MRI-guided planning enables visualization of the tumor and nearby organs in exquisite detail, allowing for individualized dose distributions.
  • Reduced Toxicity: By optimizing radiation delivery, the risk of damage to the bladder, rectum, and bowel is minimized.
  • Superior Outcomes: Studies show modern IGBT improves local control rates, pelvic tumor eradication, and overall survival compared to conventional methods.
  • International Standards: Protocols align with GEC-ESTRO guidelines—the global benchmark for gynecological brachytherapy.

How Does Dr Mathangi Ensure World-Class Brachytherapy For Cervical Cancer?

At Gleneagles Cancer Institute, Dr Mathangi J delivers brachytherapy for cervical cancer using the latest techniques and technology:

  1. MRI-guided planning: Each patient receives individualized planning using MRI, considered the gold standard for soft tissue visualization.
  2. Precise Applicators: Use of tandem and ring applicator or specialized interstitial needles for optimal coverage, even in complex cases.
  3. HDR brachytherapy: High-dose-rate delivery shortens treatment time, enhances convenience, and maintains excellent tumor control.
  4. Multidisciplinary Care: Collaboration with gynecological oncologists, radiologists, physicists, and nursing staff ensures comprehensive treatment and holistic support.
  5. Strict Adherence To GEC-ESTRO Guidelines: Every protocol is evidence-based, reflecting the latest research and best practices.

What Is The Role Of Pelvic Radiation In Cervical Cancer Stage II And IIIB?

For stage II and IIIB cervical cancers, pelvic radiation is essential to control both the primary tumor and any microscopic disease in the pelvic lymph nodes. The typical treatment sequence includes:

  • External beam radiation (EBRT) to the pelvis—treats the tumor and lymphatic drainage areas.
  • Concurrent chemotherapy (cisplatin-based)—enhances radiosensitivity and increases cure rates.
  • Brachytherapy for cervical cancer—follows EBRT to deliver a tumoricidal dose directly to the cervix and adjacent tissues, crucial for achieving a cure.

This combined approach is the global standard, with IGBT now regarded as the definitive technique for the brachytherapy component.

Why Choose HDR Brachytherapy Over Other Techniques?

HDR brachytherapy (High Dose Rate) offers several advantages over older, low-dose-rate (LDR) methods:

  • Shorter Procedure Times: Outpatient or day-care setting, reducing hospital stays.
  • Improved Dosimetry: Precise control over dose delivery, minimizing risk to normal tissues.
  • Flexible Applicators: Options like tandem and ring applicator can be adapted for different anatomies and tumor extents.
  • Enhanced Patient Comfort: Faster treatment, less immobilization, and quicker recovery.

What Makes Dr Mathangi The Leading Expert In Cervical Cancer Radiation Therapy?

Dr Mathangi J is recognized as a leading authority in cervical cancer radiation therapy across South and North India, especially Bangalore. Her credentials include:

  • Over 20 years of experience and 12,000+ successfully treated patients.
  • Advanced training in stereotactic, image-guided, and interstitial brachytherapy techniques from India and Europe.
  • Director of Fellowship in Advanced Radiotherapy Techniques, influencing the next generation of oncologists.
  • Recipient of accolades for installing Asia Pacific’s first TrueBeam STx Machine.
  • Expertise in image-guided brachytherapy, MRI-based planning, and GEC-ESTRO compliant protocols.

Patients who choose Dr Mathangi access the best of international science, compassionate care, and holistic support—all under one roof.


Don't let cervical cancer dictate your future. Take charge with world-class image-guided brachytherapy delivered by the region’s most trusted expert. To book your personalized consultation, submit your contact information here. Dr Mathangi’s dedicated team will schedule your appointment and guide you every step of the way.

What Are The Benefits Of MRI-Guided Planning In Image-Guided Brachytherapy?

MRI-guided planning represents the pinnacle of precision in IGBT for cervical cancer. Key benefits include:

  • Superior Tumor Visualization: MRI distinguishes tumor tissue from normal cervix and parametria better than CT or X-ray.
  • Personalized Dose Escalation: Allows safe delivery of higher, curative doses to the tumor while protecting bladder and rectum.
  • Better Outcomes: Multiple studies confirm improved local control and reduced late toxicity with MRI-based IGBT.

How Do GEC-ESTRO Guidelines Influence Cervical Cancer Brachytherapy?

The GEC-ESTRO guidelines set the international standard for image-guided brachytherapy in gynecologic cancers. They provide clear recommendations on:

  • Imaging protocols (preferably MRI) for accurate tumor delineation.
  • Applicator selection (e.g., tandem and ring applicator) and insertion techniques.
  • Dosimetry, target definition, and organ-at-risk sparing.
  • Reporting and follow-up protocols to ensure quality and consistency.

Dr Mathangi’s practice is fully compliant with these guidelines, ensuring world-class, evidence-based care for every patient.

Comprehensive Women’s Cancer Care At Gleneagles Cancer Institute

Beyond cervical cancer, Dr Mathangi and her expert team offer advanced radiation therapy for:

  • Head and neck cancers
  • Brain tumors
  • Spine tumors
  • Esophagus and rectal cancers
  • Lung cancers
  • Liver cancers
  • Breast, bladder, prostate, uterine, vulval, anal canal, and penile cancers

Her department is equipped with state-of-the-art technology and delivers personalized care, making it a leading destination for cancer treatment in Bangalore and across India.

About Dr Mathangi J

Dr Mathangi J is a Senior Consultant & In-charge of Radiation Oncology at Gleneagles Cancer Institute, Bangalore. With MBBS, DMRT, and DNB qualifications, and advanced fellowships from Germany and Denmark, she is a pioneer in image-guided brachytherapy and other sophisticated radiotherapy techniques. Dr Mathangi’s approach blends technical mastery, international standards, and a patient-centered philosophy—making her the trusted choice for women facing cervical and other cancers in India.

  • Senior Radiation Oncologist, 20+ years of expertise
  • Director of Fellowship in Advanced Radiotherapy Techniques (RGUHS)
  • Pioneered installation of Asia Pacific’s first TrueBeam STx Machine
  • Specializes in gynecological, brain, head and neck, lung, liver, and prostate cancers

To experience the difference of expert-led, compassionate care, book your appointment now.

Why Timely Brachytherapy For Cervical Cancer Matters

Delaying or missing advanced brachytherapy for cervical cancer can compromise cure rates and increase the risk of recurrence. Modern image-guided brachytherapy is not just a treatment—it's your best chance at a healthy, cancer-free life. Don’t miss out on the opportunity to be treated by one of India’s most accomplished experts. Schedule your consultation with Dr Mathangi today and step confidently toward recovery.

Frequently Asked Questions

What is image-guided brachytherapy (IGBT) and how does it benefit cervical cancer patients?

Image-guided brachytherapy (IGBT) is an advanced form of brachytherapy for cervical cancer where imaging modalities such as MRI or CT are used to precisely guide the placement of radioactive sources within or near the tumor. This allows for highly accurate targeting, sparing healthy tissues and improving tumor control. Dr. Mathangi utilizes IGBT to maximize treatment effectiveness for both Stage II and IIIB cervical cancer patients, reducing side effects and improving outcomes.

How does HDR brachytherapy differ from conventional brachytherapy methods?

HDR brachytherapy (High Dose Rate brachytherapy) delivers a higher dose of radiation over a shorter period of time compared to conventional low-dose-rate (LDR) methods. This allows for outpatient procedures, shorter treatment times, and greater precision. Dr. Mathangi specializes in HDR brachytherapy for cervical cancer, which can be especially beneficial when integrated with advanced imaging and personalized treatment planning.

Why is MRI-guided planning considered the gold standard for brachytherapy in cervical cancer?

MRI-guided planning provides superior visualization of the tumor and surrounding organs compared to other imaging techniques. This enables clinicians like Dr. Mathangi to define target volumes and critical structures with precision, ensuring optimal dose distribution and minimizing toxicity. MRI-guided planning is particularly important for complex cases, such as Stage IIIB cervical cancer, where tumor extent may be more challenging to assess.

What is the role of the tandem and ring applicator in cervical cancer radiation therapy?

The tandem and ring applicator is a specialized device used during brachytherapy for cervical cancer. It is inserted into the uterus and vaginal vault to accurately position the radiation source close to the tumor. Under Dr. Mathangi's care, the use of the tandem and ring applicator is tailored to each patient's anatomy and tumor size, ensuring effective and safe delivery of cervical cancer radiation therapy.

How are GEC-ESTRO guidelines followed in modern IGBT for cervical cancer?

The GEC-ESTRO guidelines provide evidence-based recommendations for target definition, dose prescription, and treatment planning in image-guided brachytherapy. Dr. Mathangi strictly adheres to these guidelines to ensure international standards of care, enhancing safety and efficacy for patients with Stage II and IIIB cervical cancer.

What are the typical steps involved in pelvic radiation and brachytherapy for cervical cancer?

Treatment typically begins with external beam pelvic radiation to shrink the tumor and treat potential lymph node spread. This is followed by brachytherapy, often using advanced image-guided techniques. Dr. Mathangi coordinates both aspects, personalizing the approach to maximize tumor control and minimize side effects, especially in advanced stages.

How does Dr. Mathangi individualize brachytherapy for cervical cancer patients?

Dr. Mathangi tailors treatment by considering tumor size, stage, patient anatomy, and response to initial therapy. Using tools like image-guided brachytherapy and MRI-guided planning, she adjusts the applicator type, radiation dose, and schedule to best fit each patient's needs, achieving optimal outcomes for both Stage II and IIIB cervical cancer.

What are the expected side effects of image-guided brachytherapy and how are they managed?

Most side effects are localized, such as vaginal irritation, urinary frequency, or mild discomfort, and are generally temporary. With advanced image-guided brachytherapy, the risk of serious complications is reduced. Dr. Mathangi and her team provide comprehensive support and follow-up to promptly address any issues, ensuring patient comfort and safety throughout the process.


Total Body Irradiation (TBI): Protocols for Bone Marrow Transplant Conditioning


By Dr Mathangi J, Sr Consultant & In-charge – Radiation Oncology, Gleneagles Cancer Institute, Bangalore

What Is Total Body Irradiation And Why Is It Crucial For Bone Marrow Transplant Conditioning?

Total Body Irradiation is a specialized form of radiotherapy that delivers a uniform dose of radiation to the entire body. It is a cornerstone in preparing patients for bone marrow or stem cell transplantation, particularly in the treatment of hematologic malignancies such as leukemia and lymphoma. According to recent studies, over 20,000 bone marrow transplants are performed annually worldwide, with TBI used in a significant proportion of these cases for optimal conditioning and disease eradication.

How Does Total Body Irradiation Work In Stem Cell Transplant Conditioning?

TBI works by eradicating malignant cells and suppressing the recipient’s immune system to prevent graft rejection. In stem cell transplant conditioning, this dual action is critical: it not only destroys any remaining cancer cells but also creates space within the bone marrow to facilitate engraftment of the donor stem cells. The process involves careful calculation of the total body irradiation dose to maximize efficacy while minimizing toxicity.

  • Immune Suppression: Reduces risk of transplant rejection.
  • Malignant Cell Eradication: Targets residual cancer cells resistant to chemotherapy.
  • Marrow Space Creation: Facilitates donor cell engraftment.

What Protocols Are Used For Myeloablative Conditioning With TBI?

Myeloablative conditioning refers to high-intensity regimens that completely ablate the patient’s bone marrow. TBI is frequently combined with high-dose chemotherapy in these protocols, designed for younger and fit patients with aggressive hematologic malignancies. Dr Mathangi and her team at Gleneagles Cancer Institute meticulously tailor protocols based on individual diagnosis, age, comorbidities, and disease status.

  1. Patient Assessment: Comprehensive evaluation including organ function and disease burden.
  2. Individualized Planning: Advanced imaging and simulation to map radiation delivery.
  3. Fractionated Dosing: TBI often delivered in multiple smaller doses (fractions) to reduce toxicity.
  4. Combination Therapy: Administered alongside chemotherapeutic agents for maximum impact.

How Is The Total Body Irradiation Dose Determined And Delivered?

Determining the appropriate total body irradiation dose is critical for balancing disease control with organ preservation. Typical regimens range from 10-14 Gy, split into 6-8 fractions over 2-4 days. Dr Mathangi’s expertise ensures state-of-the-art immobilization, real-time monitoring, and sophisticated dosimetric calculations to achieve homogenous exposure while sparing vital organs.

TBI Protocol Type Dose (Gy) Number of Fractions Indication
Myeloablative 12-14 6-8 Acute Leukemias, Lymphomas
Reduced Intensity 2-8 2-4 Elderly, Comorbid Patients

Why Is Pulmonary Toxicity Sparing Important In TBI?

A notable challenge with TBI is the risk of damaging sensitive organs, especially the lungs. Pulmonary toxicity sparing is a set of advanced techniques employed by Dr Mathangi to shield the lungs from excessive radiation, thus significantly reducing the risk of potentially life-threatening complications such as interstitial pneumonitis and fibrosis.

  • Use of customized lung blocks
  • Modern techniques like intensity-modulated radiation therapy (IMRT)
  • Real-time imaging and respiratory gating
  • Strict monitoring of lung dose constraints

These advancements have led to improved transplant outcomes and better quality of life for survivors.

What Are The Main Indications For Total Body Irradiation In Hematologic Malignancies?

TBI is primarily used in the treatment of hematologic malignancies where bone marrow transplant is indicated. Diseases commonly treated include:

  • Acute myeloid leukemia (AML)
  • Acute lymphoblastic leukemia (ALL)
  • Chronic myeloid leukemia (CML)
  • Non-Hodgkin and Hodgkin lymphomas
  • Myelodysplastic syndromes

For patients with relapsed or refractory disease, leukemia radiotherapy with TBI offers a chance at durable remission and long-term survival when combined with transplantation.

How Are TBI Side Effects Managed And What Can Patients Expect?

TBI side effects may include nausea, vomiting, mucositis, diarrhea, skin reactions, and temporary hair loss. Delayed effects can involve growth disturbances (in children), cataracts, infertility, or secondary cancers. Dr Mathangi’s approach emphasizes proactive side effect management, with a multidisciplinary team providing supportive care throughout the transplant journey.

  • Anti-nausea medications and hydration protocols
  • Skin care regimens and oral hygiene support
  • Monitoring for infections and early intervention
  • Long-term survivorship clinics for ongoing assessment

What Makes Dr Mathangi’s TBI Protocols Unique At Gleneagles Cancer Institute?

As a leader in radiation oncology with over 20 years of experience and more than 12,000 treated patients, Dr Mathangi stands at the forefront of innovation in TBI protocols. Her training in advanced radiation techniques from reputed European centers and installation of Asia Pacific’s first TrueBeam STx machine reflect her commitment to excellence.

  • Personalized, evidence-based protocols for each patient
  • Integration of the latest technology for precise, safe delivery
  • Collaboration with expert hematologists and transplant specialists
  • Comprehensive pre- and post-transplant care
  • Focus on minimizing complications and optimizing outcomes

Who Benefits Most From TBI And When Should You Consult Dr Mathangi?

Patients diagnosed with high-risk hematologic malignancies, including acute leukemias and lymphomas, stand to benefit most from expertly administered TBI as part of their stem cell transplant conditioning. Early consultation with a multidisciplinary team led by Dr Mathangi ensures timely evaluation, optimal protocol selection, and improved survival chances.

To book an appointment with Dr Mathangi and her expert team at Gleneagles Cancer Institute, Bangalore, please submit your contact information at https://drmathangi.com/contact/. Her team will promptly schedule your appointment and notify you of the details.

About Dr Mathangi

Dr Mathangi J is a Senior Consultant and In-charge of Radiation Oncology at Gleneagles Cancer Institute, Bangalore. With an MBBS, DMRT, and DNB, and over two decades of experience, she is acclaimed for her expertise in advanced techniques such as Stereotactic Ablative Body Radiotherapy, Gated RapidArc, and image-guided Interstitial Brachytherapy. She heads the radiation oncology department at her center and serves as the Director of Fellowship in Advanced Radiotherapy techniques affiliated with RGUHS. Dr Mathangi is widely recognized for her clinical excellence, leadership, and dedication to patient-centered cancer care.

Gleneagles Cancer Institute is a leading cancer care center in Bangalore, offering comprehensive and advanced treatment options for various cancers, including head and neck cancers, brain tumors, spine tumors, esophagus and rectal cancers, lung cancers, liver cancers, breast, bladder, prostate, uterine, cervical, vulval, anal canal, and penile cancers.

Key Takeaways: Why Choose Dr Mathangi For Total Body Irradiation Protocols?

  • Unmatched experience and proven expertise in TBI protocols for hematologic malignancies
  • Cutting-edge technology and individualized patient care
  • Commitment to minimizing TBI side effects and maximizing transplant success
  • Access to a multidisciplinary team for holistic cancer care
  • Patient-first approach, ensuring comfort, safety, and optimal outcomes

Don’t miss the opportunity to benefit from one of India’s most trusted experts in Total Body Irradiation. Early intervention can make all the difference in your journey towards remission and recovery.

Frequently Asked Questions

What is Total Body Irradiation and why is it used in bone marrow transplant conditioning?

Total Body Irradiation (TBI) is a specialized form of external beam radiotherapy that delivers a uniform dose of radiation to the entire body. It is primarily used as part of the preparative regimen before a stem cell or bone marrow transplant. TBI helps destroy malignant cells, suppresses the immune system to reduce graft rejection, and creates space in the bone marrow for new, healthy stem cells to engraft. Dr. Mathangi employs advanced TBI protocols tailored for optimal efficacy and patient safety.

How does myeloablative conditioning differ from reduced intensity conditioning?

Myeloablative conditioning uses high-dose chemotherapy and/or radiation, such as Total Body Irradiation, to completely destroy bone marrow cells, both healthy and malignant. This approach is often necessary for acute hematologic malignancies like leukemia, ensuring maximal disease control before transplant. Reduced intensity conditioning uses lower doses and is selected for older patients or those with comorbidities. Dr. Mathangi evaluates each patient’s profile to determine the most appropriate conditioning strategy.

How is the total body irradiation dose determined for transplant patients?

The total body irradiation dose is precisely calculated based on the patient’s age, diagnosis, overall health, and the type of stem cell transplant conditioning planned. Standard regimens typically deliver 12 Gy in divided fractions, but dosing can vary. Dr. Mathangi uses advanced planning systems and evidence-based protocols to ensure optimal dosing while minimizing the risk of side effects.

What types of hematologic malignancies are commonly treated with TBI in transplant settings?

TBI as part of transplant conditioning is most frequently used for hematologic malignancies such as acute lymphoblastic leukemia (ALL), acute myeloid leukemia (AML), certain lymphomas, and myelodysplastic syndromes. Its role is well established in improving outcomes for high-risk or relapsed disease. Dr. Mathangi customizes protocols to address specific disease characteristics and patient needs.

How does TBI compare to chemotherapy-only regimens for leukemia radiotherapy?

TBI offers several advantages over chemotherapy-only regimens, especially for leukemia radiotherapy. It provides uniform eradication of malignant cells throughout the body, including sanctuary sites that might be less accessible to chemotherapy. Studies show that, in select populations, TBI-containing regimens may lead to improved disease control. Dr. Mathangi carefully evaluates the potential benefits and risks to design the best individualized approach.

What are the common TBI side effects and how are they managed?

TBI side effects can include fatigue, nausea, hair loss, mouth sores, skin reactions, and a lowered blood count. Long-term risks may involve cataracts, infertility, growth delay (in children), and organ toxicity. Dr. Mathangi incorporates preventive strategies, supportive care, and modern techniques to minimize these effects, ensuring close monitoring and prompt management throughout the treatment process.

What measures are used for pulmonary toxicity sparing during TBI?

Pulmonary toxicity sparing is a critical aspect of TBI planning. Techniques such as lung shielding, advanced dose modulation, and careful patient positioning are employed to reduce the risk of radiation-induced lung injury. Dr. Mathangi utilizes sophisticated imaging and planning tools to optimize lung protection, while still ensuring effective conditioning for the transplant.

How does Dr. Mathangi’s approach enhance safety and outcomes in stem cell transplant conditioning?

Dr. Mathangi’s approach combines evidence-based protocols, state-of-the-art technology, and personalized care to optimize outcomes in stem cell transplant conditioning. Her meticulous planning includes dose customization, organ protection strategies, and close interdisciplinary collaboration, all aimed at maximizing transplant success while minimizing risks for each patient.

Can patients undergoing TBI return to normal life after transplant?

Many patients are able to return to normal activities following recovery from TBI and bone marrow transplantation, though this process may take several months. Dr. Mathangi’s team provides comprehensive follow-up care to monitor recovery, manage late effects, and support reintegration into daily life, ensuring the best possible long-term outcomes.


SBRT vs SRS: Understanding Brain and Lung Cancer Radiation Protocols


What Is The Difference Between SBRT Vs SRS In Cancer Treatment?

SBRT vs SRS are two advanced radiation techniques that revolutionize the management of brain and lung cancers. Both treatments offer highly targeted, non-invasive alternatives to surgery, with studies showing that stereotactic techniques can achieve local control rates of up to 85-95% in early-stage lung and brain tumors. Choosing the right protocol—SBRT or SRS—can significantly impact a patient’s quality of life and overall outcome.

Under the expert guidance of Dr Mathangi J, Senior Consultant and In-charge of Radiation Oncology at Gleneagles Cancer Institute, Bangalore, patients benefit from precise, personalized, and evidence-based protocols. This article provides a comprehensive comparison, answering common questions and helping you make informed decisions about your treatment options.

How Does Stereotactic Body Radiotherapy Work?

Stereotactic body radiotherapy (SBRT) is a cutting-edge technique that delivers very high doses of radiation to tumors in the body—most commonly in the lung, liver, spine, prostate, and adrenal glands. SBRT uses advanced imaging and computer planning to precisely target tumors, minimizing exposure to surrounding healthy tissue.

  • Typically used for small, well-defined tumors
  • Treatment usually completed in 1-5 sessions
  • Ideal for patients who are not surgical candidates
  • Reduces overall treatment time and side effects

Dr Mathangi’s expertise in stereotactic body radiotherapy ensures that patients with complex cases—such as lung tumor ablation SBRT—receive meticulous care, reducing recurrence risks and improving survival rates.

What Is Stereotactic Radiosurgery And When Is It Used?

Stereotactic radiosurgery (SRS) is a non-surgical radiation technique primarily used for brain and spinal tumors. Despite the name, SRS does not involve any incisions or surgical procedures. Instead, it delivers a single, very high dose of focused radiation to destroy tumor cells.

  • Best suited for brain metastases, benign brain tumors, and functional disorders
  • Typically performed in a single session
  • Minimizes risk to healthy brain tissue
  • Can treat multiple tumors simultaneously

Dr Mathangi is renowned for her advanced training in intracranial radiosurgery, particularly for challenging brain lesions, offering hope where conventional therapies may fall short.

SBRT Vs SRS: Key Differences At A Glance

Aspect SBRT SRS
Full Form Stereotactic Body Radiotherapy Stereotactic Radiosurgery
Target Area Body (e.g., lung, liver, spine, prostate) Brain and spine
Fractionation 1-5 fractions (sessions) Typically single session
Common Indications Lung, liver, spine, oligometastatic disease Brain metastases, benign brain tumors
Technology Used LINAC, CyberKnife, Gamma Knife LINAC, Gamma Knife, CyberKnife
Precision High (sub-millimeter accuracy) Very high (sub-millimeter accuracy)

Both SBRT and SRS utilize state-of-the-art devices like LINAC radiosurgery platforms, but their application and dosing protocols differ based on tumor location and type.

How Are Lung Tumors Treated With Lung Tumor Ablation SBRT?

Lung tumor ablation SBRT is a breakthrough for patients with early-stage lung cancer or inoperable tumors. Using focused beams, SBRT can deliver ablative doses—destroying tumor cells while preserving lung function.

  • Highly effective for patients with limited (oligometastatic) lung disease
  • Reduces recovery time and hospital visits
  • Minimal impact on breathing and overall lung health

Dr Mathangi’s team employs advanced motion management techniques, such as Gated RapidArc and DIBH, to further improve the safety and effectiveness of lung tumor ablation SBRT.

What Is Oligometastatic Disease And Why Does It Matter?

Oligometastatic disease refers to cancer that has spread to a limited number (typically up to 5) of sites beyond the primary tumor. This state is increasingly recognized as potentially curable or controllable with aggressive local therapies like SBRT or SRS.

  • Common in lung, liver, and brain metastases
  • SBRT and SRS can achieve long-term control or even cure
  • Reduces need for extensive systemic therapy

Through her vast experience, Dr Mathangi delivers personalized SBRT vs SRS strategies tailored to the unique biology and spread of each patient’s cancer, maximizing outcomes.

How Does Fractionated Stereotactic Radiotherapy Benefit Patients?

Fractionated stereotactic radiotherapy involves dividing the total radiation dose into several smaller treatments (fractions), typically over multiple days. This approach is especially useful for large or critically located tumors where a single high dose could risk damaging surrounding tissues.

  • Improves safety for sensitive or large tumors
  • Allows normal tissues time to recover between sessions
  • Maintains high precision and tumor control rates

Dr Mathangi’s approach integrates fractionated stereotactic radiotherapy for select patients, balancing efficacy with reduced toxicity.

Why Choose LINAC Radiosurgery For Brain And Body Tumors?

LINAC radiosurgery uses a Linear Accelerator (LINAC) to generate high-energy X-rays, delivering pinpoint radiation to tumors in the brain and body. This system is versatile, cost-effective, and capable of treating a wide range of cancers.

  • Suitable for both SBRT and SRS procedures
  • Enables adaptive treatment planning
  • Can treat multiple lesions in a single session
  • Widely available and highly reliable

Dr Mathangi has been instrumental in introducing the region’s first TrueBeam STx Machine, setting new benchmarks for precision and patient outcomes with LINAC radiosurgery.

Which Cancers Need Radiation Therapy?

According to Dr Mathangi, cancers most likely to benefit from radiation therapy—including SBRT vs SRS—are:

  • Head and neck cancers
  • Brain tumors
  • Spine tumors
  • Esophagus and rectal cancers
  • Lung cancers
  • Liver cancers
  • Breast cancers
  • Bladder cancers
  • Prostate cancers
  • Uterine cancers
  • Cervical cancer
  • Vulval cancers
  • Anal canal cancers
  • Penile cancers

The right protocol—be it stereotactic body radiotherapy, stereotactic radiosurgery, or fractionated stereotactic radiotherapy—depends on tumor location, size, and patient health.

Why Trust Dr Mathangi For SBRT Vs SRS In Bangalore?

Dr Mathangi J stands out as one of India’s most accomplished radiation oncologists, combining technical excellence, global training, and compassionate care. She heads Gleneagles Cancer Institute in Bangalore, a leader in advanced cancer care.

  • 20+ years of experience with 12,000+ patients treated
  • Expert in all major stereotactic techniques (SBRT vs SRS)
  • Asia Pacific’s first TrueBeam STx installation
  • Director of Fellowship in Advanced Radiotherapy Techniques
  • Focus on evidence, safety, and patient-centered outcomes

Patients who do not opt for her specialized protocols risk missing out on the latest advances and highest standards in cancer care. To book your consultation with Dr Mathangi, submit your details at drmathangi.com/contact/ and let her team help you chart the best course for your recovery.

About Dr Mathangi

Dr Mathangi Radiation Oncologist

Dr Mathangi J is a Senior Consultant and Head of Radiation Oncology at Gleneagles Cancer Institute, Bangalore. With over 20 years of experience, she has pioneered many advanced techniques in India, including SRS, SBRT, and LINAC radiosurgery. Her commitment to global best practices, patient safety, and continuous innovation make her the preferred choice for complex cancer cases in South and North India.

Gleneagles Cancer Institute, part of Gleneagles Hospitals, is renowned for its comprehensive cancer care and world-class technology. Dr Mathangi’s leadership ensures that every patient receives a tailored, evidence-based approach for optimal outcomes.

Frequently Asked Questions

What is the difference between SBRT and SRS, and when is each used?

The key difference between SBRT vs SRS lies in the treatment area and number of sessions. Stereotactic body radiotherapy (SBRT) is primarily used for tumors outside the brain, such as in the lungs or liver, and typically involves 1–5 sessions. Stereotactic radiosurgery (SRS) is focused on intracranial radiosurgery—treating brain tumors or lesions in one single, high-precision session. Dr. Mathangi evaluates each patient to determine which protocol offers the best balance of tumor control and safety based on tumor location, size, and the patient’s overall health.

How does SBRT work for lung cancer and what is lung tumor ablation SBRT?

SBRT for lung cancer delivers high-dose radiation with millimeter accuracy, targeting lung tumors while minimizing damage to healthy tissue. Lung tumor ablation SBRT is especially effective for patients with early-stage lung cancer or those who are not candidates for surgery. Dr. Mathangi uses advanced imaging and motion management to ensure precise delivery, maximizing tumor ablation and reducing side effects.

What are the advantages of stereotactic radiosurgery for brain tumors?

Stereotactic radiosurgery offers a non-invasive alternative to brain surgery for certain tumors and brain metastases. It delivers a single, high dose of radiation directly to the tumor with pinpoint accuracy, often without an incision or hospital stay. Dr. Mathangi’s expertise in LINAC radiosurgery ensures optimal outcomes for patients needing intracranial radiosurgery, with rapid recovery and minimal disruption to daily life.

Can fractionated stereotactic radiotherapy be used for both brain and lung tumors?

Yes, fractionated stereotactic radiotherapy involves delivering radiation in several smaller sessions, rather than a single high dose. This approach is used when tumors are near sensitive structures or are larger in size, both in the brain and other parts of the body. Dr. Mathangi customizes the number of fractions and dose per session to maximize safety and effectiveness for each patient.

What is oligometastatic disease and how can SBRT or SRS help?

Oligometastatic disease refers to cancer that has spread to a limited number of sites (usually up to 5). Both SBRT and SRS are effective in controlling these limited metastases, whether in the brain or the body. Dr. Mathangi leverages these advanced techniques to target each metastatic site precisely, aiming to prolong survival and maintain quality of life.

What are the risks and side effects associated with SBRT and SRS?

Both SBRT and SRS are designed to minimize exposure to healthy tissues, but side effects can occur depending on the treatment site. For SBRT, possible side effects include fatigue, mild skin changes, or localized pain. SRS for brain lesions may cause headaches, swelling, or rarely, cognitive changes. Dr. Mathangi discusses all potential risks thoroughly and employs careful planning to reduce complications.

How does LINAC radiosurgery compare to other radiosurgery platforms?

LINAC radiosurgery uses a linear accelerator to deliver high-dose, precisely shaped beams of radiation to the tumor. It offers flexibility in treating both brain and body tumors with SBRT and SRS. Compared to other platforms, LINAC systems are highly adaptable and allow for both single-fraction and fractionated stereotactic treatments. Dr. Mathangi utilizes state-of-the-art LINAC technology for safe and effective cancer care.

Why should I consult Dr. Mathangi for stereotactic body radiotherapy or radiosurgery?

Dr. Mathangi is a specialist in advanced radiation protocols, including stereotactic body radiotherapy and stereotactic radiosurgery. She provides personalized care, assesses eligibility for SBRT vs SRS, and guides patients through treatment decisions using the latest technologies and protocols. Her patient-centered approach ensures that each treatment plan is tailored to achieve the best possible outcome with minimal side effects.

Deep Inspiration Breath Hold (DIBH) vs Free Breathing in Left-Sided Breast Cancer Radiotherapy


What is the difference between Deep Inspiration Breath Hold (DIBH) and Free Breathing for left-sided breast cancer radiotherapy?

Deep Inspiration Breath Hold (DIBH) breast cancer technique significantly reduces radiation exposure to the heart compared to Free Breathing, making it a preferred method for left-sided breast cancer radiotherapy. DIBH helps minimize long-term cardiotoxicity and improves patient safety during treatment.

Did you know that studies show DIBH breast cancer protocols can reduce cardiac radiation dose by up to 60% compared to traditional Free Breathing methods?1 For women with left-sided breast cancer, this can mean a major reduction in the risk of heart disease post-treatment. With breast cancer rates rising and survivorship improving, it is crucial to ensure the highest level of cardiac protection during radiotherapy. Dr Mathangi J, Senior Radiation Oncologist and In-charge at Gleneagles Cancer Institute, Bangalore, leads the way with advanced DIBH techniques, offering hope and safety to thousands of patients across South and North India.

Meet Dr Mathangi J – Your Expert in Advanced Radiation Oncology

  • Senior Consultant & In-charge - Radiation Oncology at Gleneagles Cancer Institute, Bangalore
  • MBBS, DMRT (Madras Medical College), DNB (Apollo Cancer Specialty Hospital)
  • 20+ years of experience, 12,000+ patients treated
  • Expert in Stereotactic techniques, DIBH gated Radiotherapy, IGRT/RapidArc, and more
  • Director of Fellowship in Advanced Radiotherapy (RGUHS)
  • Installed Asia Pacific’s first TrueBeam STx Machine
  • Specializes in Head and Neck, Brain, Lung, Prostate, and Women’s Cancers

To consult with Dr Mathangi, submit your contact details at this form and her team will schedule your appointment.

Why is DIBH preferred over Free Breathing for left-sided breast cancer radiotherapy?

DIBH breast cancer protocols are favored because they dramatically reduce the heart’s exposure to radiation, a major concern in left-sided breast cancer radiotherapy. During DIBH, patients take a deep breath and hold it, expanding the lungs and moving the heart away from the chest wall. This increased distance allows the radiation to target breast tissue precisely while minimizing the dose to the heart and the critical LAD artery (left anterior descending artery).

  • Cardiac dose sparing: DIBH can reduce mean heart dose by up to 60% compared to Free Breathing.
  • LAD artery radiation protection: The DIBH radiation technique specifically protects the LAD artery, lowering the risk of long-term cardiovascular complications.
  • Reduced risk of cardiotoxicity radiation breast cancer: Lower cardiac exposure translates to significantly reduced cardiotoxicity, enhancing long-term outcomes.

How does deep inspiration breath hold radiotherapy work?

Deep inspiration breath hold radiotherapy involves these key steps:

  1. The patient inhales deeply and holds their breath at a predetermined lung volume.
  2. During this breath hold, the heart moves down and away from the breast tissue, creating a physical separation.
  3. Radiation is delivered precisely during this period, ensuring minimal heart exposure.
  4. This process may be repeated several times during each treatment session.

Technologies such as respiratory gating and real-time monitoring ensure that radiation is only delivered when the patient holds their breath within the required threshold, maximizing treatment precision and safety.

Comparison Table: DIBH vs Free Breathing in Left-Sided Breast Cancer Radiotherapy

Parameter DIBH (Deep Inspiration Breath Hold) Free Breathing
Heart Dose Significantly Reduced Higher
LAD Artery Exposure Minimized Significant
Cardiotoxicity Risk Much Lower Increased
Respiratory Gating Essential Part Not Used
Patient Comfort Requires Training Simple
Precision High Lower
Long-Term Cardiac Outcomes Favorable Potentially Risky

What are the risks of cardiotoxicity radiation breast cancer?

Cardiotoxicity radiation breast cancer refers to damage caused to the heart by radiotherapy, especially when treating left-sided breast cancers. The heart, and particularly the LAD artery, can receive incidental radiation, leading to increased risk of ischemic heart disease, arrhythmias, pericarditis, and reduced cardiac function over time. Even modest increases in heart dose have been linked to higher rates of cardiac events in survivors.

  • Every 1 Gy increase in mean heart dose increases the risk of major coronary events by 7.4%.
  • Cardiac events can manifest years after treatment, impacting survivorship and quality of life.
  • DIBH breast cancer protocols are designed to mitigate these risks by minimizing radiation exposure to cardiac structures.

How does LAD artery radiation protection work in DIBH?

The LAD artery is a critical vessel supplying blood to the heart’s front wall and is particularly vulnerable during left-sided breast radiotherapy. LAD artery radiation protection is achieved through the DIBH radiation technique, which utilizes the anatomical shift during deep inspiration to physically distance the LAD from the treatment field, thus lowering the risk of radiation-induced coronary artery disease.

What role does respiratory gating play in modern radiotherapy?

Respiratory gating is a technology that synchronizes radiation delivery with the patient’s breathing cycle. In DIBH breast cancer protocols, respiratory gating ensures that radiation is only administered when the heart is farthest from the radiation beam, further optimizing cardiac dose sparing. This technology increases the accuracy of each session and reduces the risk of inadvertent exposure to healthy tissues.

What is cardiac dose sparing, and why is it vital?

Cardiac dose sparing refers to reduction of the radiation dose delivered to the heart during breast cancer radiotherapy. This is especially critical for left-sided breast cancer radiotherapy, as the heart lies close to the breast and can be inadvertently damaged. Cardiac dose sparing techniques, including DIBH, play a pivotal role in reducing the long-term risk of cardiac morbidity and mortality in survivors.

How does the DIBH radiation technique enhance safety and effectiveness?

The DIBH radiation technique enhances safety by:

  • Minimizing cardiac and pulmonary exposure
  • Allowing for more precise targeting of the tumor
  • Reducing the risk of secondary cancers and cardiac events
  • Improving long-term survival and quality of life

Under the expert care of Dr Mathangi J, patients benefit from state-of-the-art planning and delivery systems that integrate respiratory gating and real-time monitoring, ensuring every session is both safe and effective.

Who should consider DIBH breast cancer protocols?

DIBH breast cancer protocols are especially recommended for:

  • All patients with left-sided breast cancer requiring radiotherapy
  • Patients with pre-existing heart disease or risk factors for cardiac disease
  • Young women, who have a longer life expectancy and thus a higher lifetime risk of late cardiac effects

With the rising incidence of breast cancers and improved survival rates, choosing DIBH over Free Breathing can powerfully impact your future health and peace of mind.

Take the Next Step: Book Your Consultation with Dr Mathangi

Why settle for standard care when you can access world-class expertise? Dr Mathangi J offers advanced DIBH breast cancer radiotherapy at Gleneagles Cancer Institute, Bangalore, ensuring the best possible protection for your heart and long-term well-being. Don’t risk unnecessary exposure—choose the most advanced care available in South and North India.

Ready to get started? Submit your details here and Dr Mathangi’s team will promptly schedule your appointment.

What other cancers benefit from advanced radiotherapy techniques?

According to Dr Mathangi, cancers that benefit from advanced radiation therapy (RT) include:

  1. Head and neck cancers
  2. Brain tumors
  3. Spine tumors
  4. Esophagus and rectal cancers
  5. Lung cancers
  6. Liver cancers
  7. Breast cancers
  8. Bladder cancers
  9. Prostate cancers
  10. Uterine cancers
  11. Cervical cancer
  12. Vulval cancers
  13. Anal canal cancers
  14. Penile cancers

Dr Mathangi’s expertise spans all these cancer types, ensuring that patients receive personalized, cutting-edge care tailored to their individual needs.

About Dr Mathangi J

Dr Mathangi J is a highly respected Senior Radiation Oncologist based in Bangalore, India, with over two decades of experience in treating complex cancers. As the In-charge of Gleneagles Cancer Institute, she is renowned for her deep expertise in advanced radiotherapy techniques, including DIBH, SBRT, and IGRT. Her commitment to patient safety, innovation, and education has made her a leader in oncology across South and North India. Patients and caregivers trust Dr Mathangi for her compassionate approach and her unwavering focus on delivering the best possible outcomes.

For more information or to schedule a consultation, visit Dr Mathangi’s official website.

Frequently Asked Questions

What is Deep Inspiration Breath Hold (DIBH) and how does it differ from free breathing in left-sided breast cancer radiotherapy?

Deep Inspiration Breath Hold (DIBH) is a technique used during left-sided breast cancer radiotherapy where the patient is asked to take a deep breath and hold it for a short period while radiation is delivered. This expands the lungs and increases the distance between the heart and the chest wall, thereby reducing radiation exposure to the heart. In contrast, free breathing involves the patient breathing normally during treatment, which can result in higher cardiac doses. DIBH breast cancer protocols are particularly helpful in minimizing risks associated with cardiotoxicity radiation breast cancer treatments.

Why is heart protection important in left-sided breast cancer radiotherapy?

The heart lies close to the left breast, making it susceptible to unwanted radiation exposure during left-sided breast cancer radiotherapy. Even small doses to the heart can increase the risk of long-term cardiac complications. Protecting the heart, especially the left anterior descending (LAD) artery, is crucial because it can help reduce the chances of cardiotoxicity radiation breast cancer side effects. Techniques like deep inspiration breath hold radiotherapy are essential in providing LAD artery radiation protection and improving patient outcomes.

How does the DIBH radiation technique help in reducing cardiac dose?

The DIBH radiation technique works by expanding the chest cavity during a deep breath, which moves the heart away from the path of the radiation beams. This spatial separation allows for more precise targeting of the breast tissue while sparing the heart and adjacent structures from unnecessary exposure. As a result, DIBH is highly effective at cardiac dose sparing, which is especially important for patients receiving left-sided breast cancer radiotherapy.

What is respiratory gating and how is it used in DIBH?

Respiratory gating is a technology that synchronizes the delivery of radiation with the patient's breathing cycle. In DIBH, respiratory gating ensures that radiation is delivered only when the patient is holding their breath at the optimal lung expansion. This further enhances the benefit of deep inspiration breath hold radiotherapy by guaranteeing that the heart is at its maximum distance from the chest wall during each treatment session.

How does Dr. Mathangi ensure effective LAD artery radiation protection for her patients?

Dr. Mathangi utilizes advanced planning and imaging techniques during DIBH breast cancer treatments to clearly visualize the heart and LAD artery. She customizes the radiation plan for each patient, often using 3D imaging and respiratory gating, to ensure the lowest possible dose to the LAD artery. This personalized approach provides optimal LAD artery radiation protection and minimizes cardiac risks.

Are there any challenges or limitations to using DIBH in clinical practice?

While the DIBH radiation technique offers significant benefits, it does require patient cooperation and the ability to hold their breath for short durations. Some patients may find it challenging due to anxiety, lung conditions, or difficulty following instructions. Dr. Mathangi provides thorough guidance and practice sessions to help patients become comfortable with the process, maximizing the effectiveness of deep inspiration breath hold radiotherapy.

What kind of results have patients experienced with DIBH under Dr. Mathangi’s care?

Patients treated with DIBH breast cancer protocols under Dr. Mathangi’s supervision have experienced reduced cardiac exposure, minimized risk of long-term heart complications, and high satisfaction with the overall treatment process. Her expertise in left-sided breast cancer radiotherapy and commitment to cardiac dose sparing have led to improved clinical outcomes and peace of mind for patients concerned about cardiotoxicity radiation breast cancer risks.

Is DIBH suitable for all patients receiving left-sided breast cancer radiotherapy?

DIBH is highly recommended for most patients undergoing left-sided breast cancer radiotherapy, especially when heart or LAD artery sparing is a priority. However, eligibility is assessed on an individual basis. Dr. Mathangi evaluates each patient’s ability to perform breath holds and tailors the approach as needed, sometimes integrating alternative cardiac protection strategies if necessary.

How can patients prepare for DIBH-based treatments with Dr. Mathangi?

Patients scheduled for DIBH-based deep inspiration breath hold radiotherapy receive detailed instructions and practice sessions before treatment begins. Dr. Mathangi’s team guides patients through breath-hold exercises and explains what to expect during each session, ensuring comfort and confidence throughout the course of DIBH breast cancer therapy.


The Role of Radiation Therapy in Preventing Breast Cancer Recurrence

What is the most effective way to prevent breast cancer from coming back after surgery? Radiation therapy, under expert supervision, is the cornerstone of recurrence prevention for women with breast cancer, dramatically reducing local recurrence risk and improving breast cancer survival rates. In fact, studies reveal that radiation preventing breast cancer recurrence can reduce the risk of cancer returning in the breast or chest wall by up to 70% after breast-conserving surgery1. This makes radiation therapy an essential component in the fight against breast cancer recurrence.

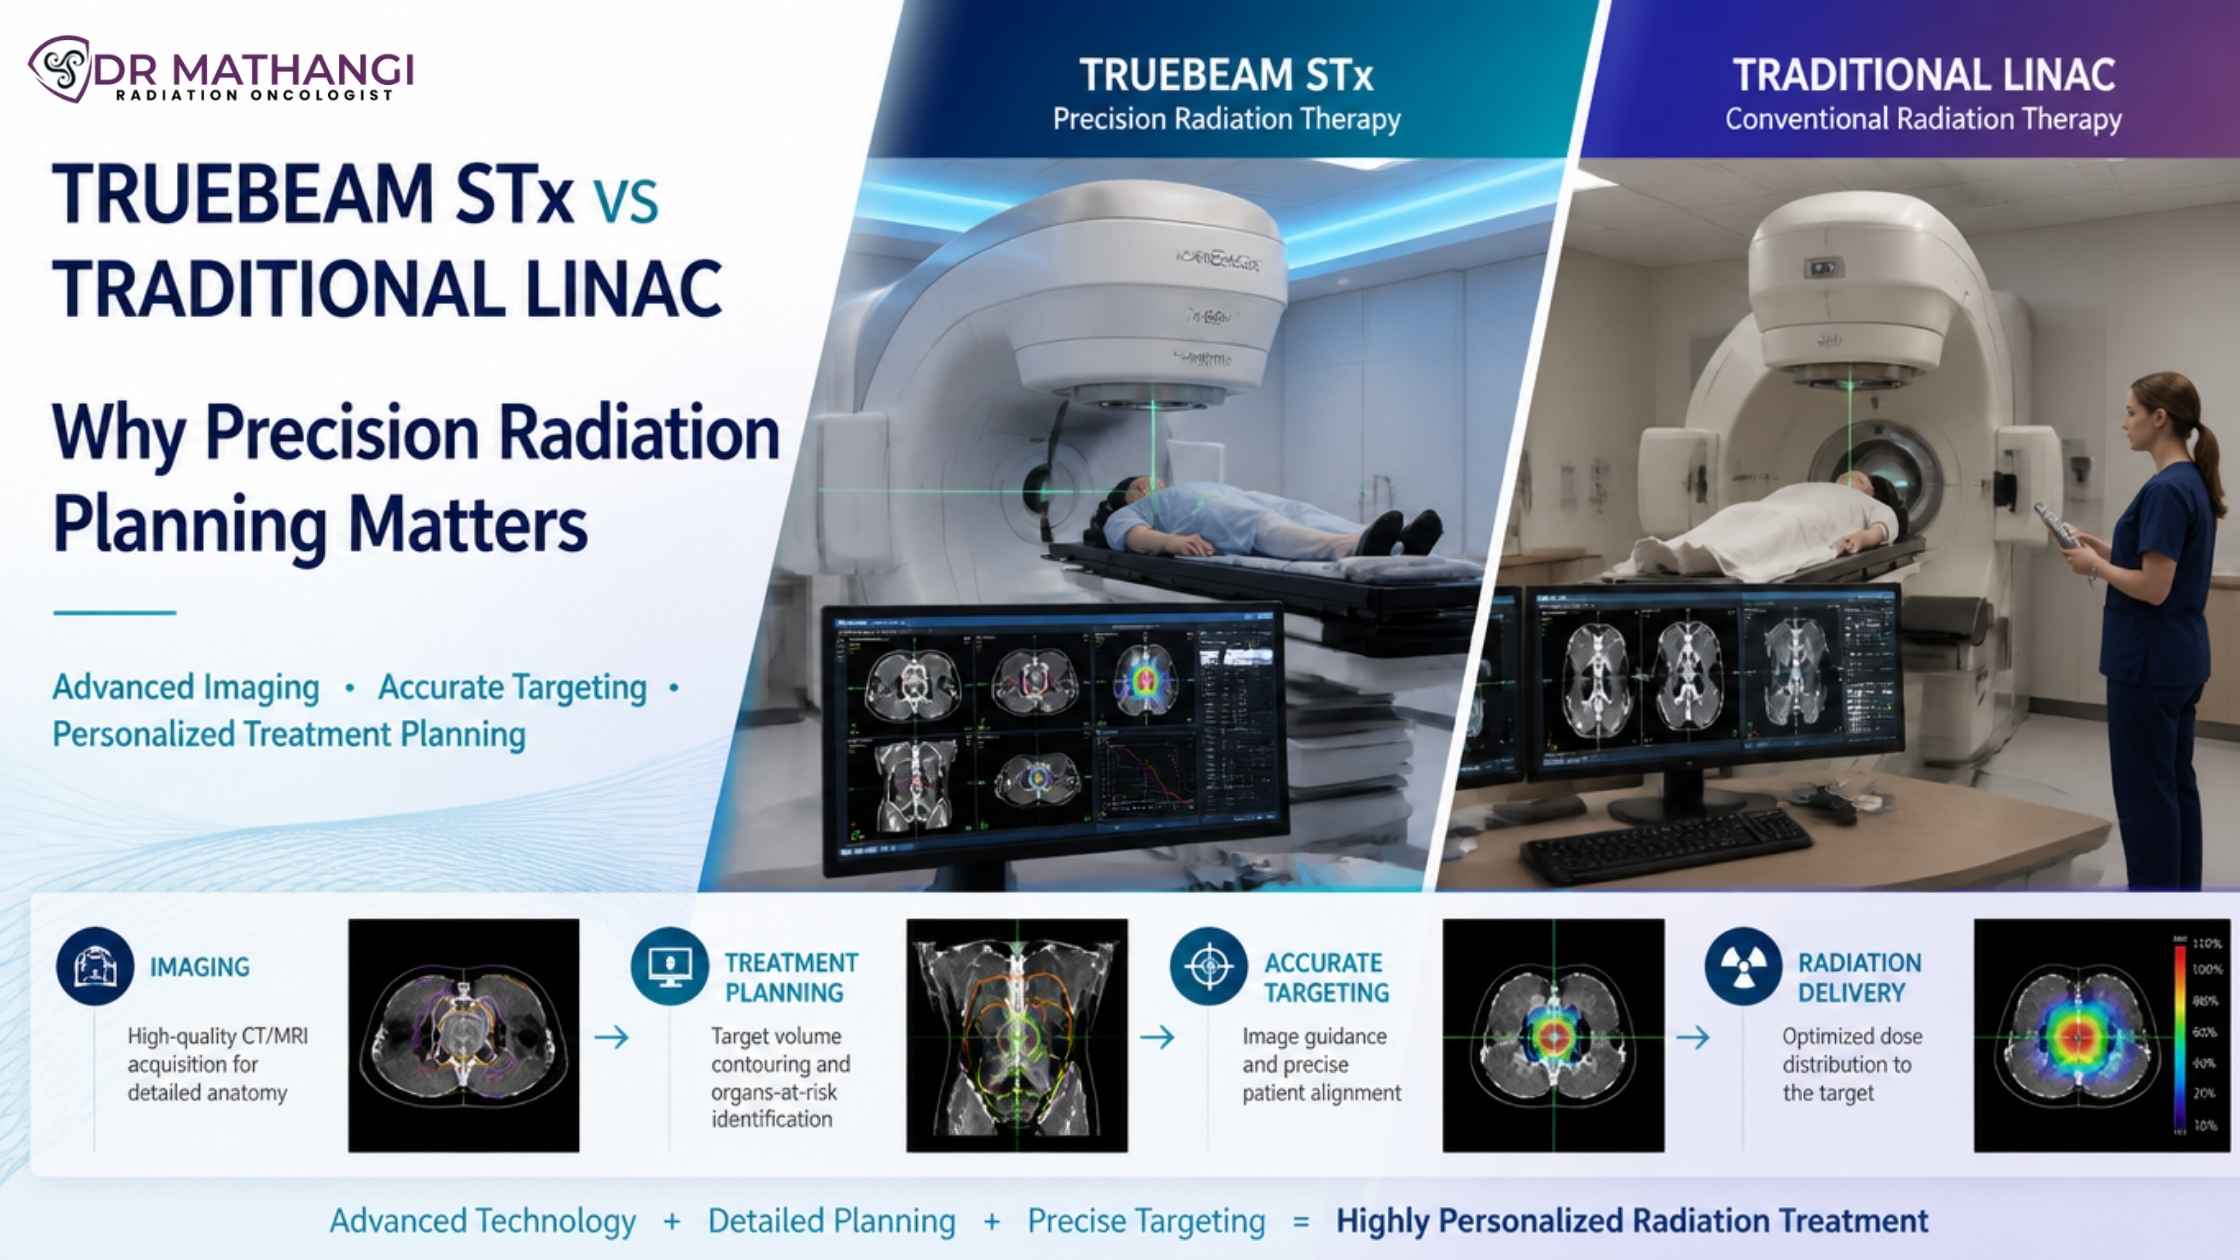
Did you know? Without post surgery radiation therapy, about one in three women with early breast cancer may experience local recurrence within 10 years. With the right treatment approach, this risk can be reduced to less than 10%—a remarkable improvement for long-term health and peace of mind.

How does radiation therapy prevent breast cancer recurrence?

Radiation therapy uses high-energy rays or particles to destroy cancer cells that may remain in the breast, chest wall, or lymph nodes after surgery. By targeting microscopic cancer cells left behind, radiation preventing breast cancer recurrence ensures that these cells do not multiply and form new tumors, significantly lowering the chance of cancer returning in the treated area.

  • Precision targeting means healthy tissues are spared as much as possible
  • Modern techniques like IMRT, RapidArc, and DIBH minimize side effects while maximizing cancer cell destruction
  • Effective for different stages: from early breast cancer (after lumpectomy) to locally advanced cases (post-mastectomy)

What is local recurrence risk and why does it matter?

Local recurrence risk refers to the likelihood that breast cancer will return in the same area where it was originally found, such as the breast, chest wall, or nearby lymph nodes. This risk is highest within the first few years after initial treatment and varies based on:

  • Tumor size and grade
  • Surgical margins (how much healthy tissue was removed around the tumor)
  • Presence of lymph node involvement
  • Patient’s age and overall health
  • Whether post surgery radiation therapy was administered

By reducing local recurrence risk, radiation therapy not only protects the treated area but also improves overall prognosis, as local recurrences can be more difficult to treat and may lead to distant metastases.

Why is post surgery radiation therapy crucial for recurrence prevention?

Post surgery radiation therapy—sometimes called adjuvant radiation—is administered after breast-conserving surgery (lumpectomy) or, in selected cases, after mastectomy. Its primary goal is recurrence prevention by sterilizing any undetected cancer cells that might have been missed during surgery.

When is post surgery radiation therapy recommended?

  • After lumpectomy, to treat the remaining breast tissue
  • After mastectomy, especially if cancer was large (>5 cm), involved the skin or chest wall, or spread to multiple lymph nodes
  • For patients with positive surgical margins or high-risk features

By incorporating radiation therapy into personalized treatment plans, Dr Mathangi ensures each patient receives the best possible chance for long-term remission and improved breast cancer survival rates.

How does radiation therapy improve breast cancer survival rates?

Numerous clinical trials have shown that radiation therapy not only reduces local recurrence but also increases overall breast cancer survival rates. By eliminating residual cancer cells, it prevents local recurrences that could otherwise lead to further spread of the disease.

Scenario 10-Year Local Recurrence (No Radiation) 10-Year Local Recurrence (With Radiation) Impact on Survival
After Lumpectomy ~35% <10% Significant Survival Benefit
After Mastectomy (Node Positive) ~20-30% <5-10% Improved Survival

This substantial reduction in recurrence rates translates to improved breast cancer survival rates for thousands of women each year.

What advanced radiation techniques are available at Gleneagles Cancer Institute?

Under the leadership of Dr Mathangi J, Gleneagles Cancer Institute in Bangalore offers state-of-the-art radiation oncology services, ensuring the highest standards in recurrence prevention. Dr Mathangi’s expertise spans:

  • Stereotactic ablative body radiotherapy (SBRT): High-precision radiation for focused treatment
  • Gated RapidArc: Delivers radiation during specific parts of the breathing cycle, reducing exposure to the heart and lungs
  • DIBH gated radiotherapy: Deep inspiration breath-hold technique to further protect healthy tissues
  • Image-guided interstitial brachytherapy: Internal radiation for precise targeting

These innovations ensure that each patient receives a tailored approach, maximizing the benefit of radiation preventing breast cancer recurrence while minimizing side effects.

Who should consider radiation therapy for breast cancer?

According to Dr Mathangi, cancers that need RT (radiotherapy) include:

  • Head and neck cancers
  • Brain tumors
  • Spine tumors
  • Esophagus and rectal cancers
  • Lung cancers
  • Liver cancers
  • Breast cancers
  • Bladder cancers
  • Prostate cancers
  • Uterine, cervical, vulval, anal canal, and penile cancers

For breast cancer patients, especially those with risk factors for recurrence, radiation therapy is not just an option—it is a vital part of comprehensive cancer care.

What sets Dr Mathangi apart in breast cancer radiation therapy?

With more than 20 years of specialized experience and over 12,000 patients successfully treated, Dr Mathangi is a pioneer in advanced radiotherapy. She is:

  • The Senior Consultant & In-charge of Radiation Oncology at Gleneagles Cancer Institute, Bangalore
  • Trained internationally in Stereotactic techniques, IGRT/RapidArc, and Intraoperative radiotherapy
  • Director of Fellowship in Advanced Radiotherapy techniques, affiliated with RGUHS
  • Instrumental in installing Asia Pacific's first TrueBeam STx Machine
  • Recognized for patient-centric, evidence-based care that emphasizes recurrence prevention

Her leadership and commitment to excellence make her one of the most sought-after radiation oncologists in South India and North India.

How can you book a consultation with Dr Mathangi?

  1. Visit Dr Mathangi's Contact Page.
  2. Submit your contact information using the secure form.
  3. Her expert team will promptly schedule your appointment and notify you of the date and time.

Book Your Consultation

Don’t risk a recurrence—make the choice that could save your future health. Trust your care to Dr Mathangi’s expertise and advanced technology for the best chance at a cancer-free life.

About Dr Mathangi J

Dr Mathangi J, Senior Radiation Oncologist Gleneagles Cancer Institute Bangalore

Dr Mathangi J is a Senior Consultant & In-charge of Radiation Oncology at Gleneagles Cancer Institute, Bangalore, with MBBS, DMRT, and DNB qualifications. With over 20 years of experience, she has pioneered the adoption of advanced radiation techniques, including Stereotactic radiotherapy, RapidArc, and DIBH, for optimal recurrence prevention in breast and other cancers. Her patient-first philosophy, international training, and leadership in technology adoption make her a trusted name in cancer care across India.

Why choose Gleneagles Cancer Institute for your radiation therapy?

Gleneagles Cancer Institute, part of Gleneagles Hospitals, is recognized for its comprehensive, multidisciplinary approach and cutting-edge technology. With Dr Mathangi at the helm, patients benefit from:

  • Personalized treatment plans based on each patient’s risk profile
  • Access to the latest innovations in radiation oncology
  • Compassionate, evidence-driven care for every stage of breast cancer
  • Proven track record in improving breast cancer survival rates

Whether you reside in Bangalore, elsewhere in South India, or North India, Gleneagles Cancer Institute delivers world-class cancer care close to home.

Take action now for recurrence prevention

The risk of breast cancer returning can be drastically reduced. By choosing radiation preventing breast cancer recurrence under the care of Dr Mathangi, you prioritize both your survival and your quality of life. Don’t wait—reach out today to secure your future health.

For appointments and more information, visit drmathangi.com/contact/


Frequently Asked Questions

What is the role of radiation therapy in preventing breast cancer recurrence?

Radiation therapy is a critical component in the treatment plan for many breast cancer patients, especially after surgery. By targeting any remaining cancer cells in the breast, chest wall, or lymph nodes, radiation therapy significantly reduces the risk of the cancer returning in the same area. This proactive approach is central to radiation preventing breast cancer recurrence, helping patients achieve long-term remission and peace of mind.

How does Dr. Mathangi determine if I need post surgery radiation therapy?

Dr. Mathangi conducts a comprehensive evaluation of your pathology report, tumor size, margins, lymph node involvement, and overall health. If there is a moderate to high risk for local recurrence or if the tumor was large or involved lymph nodes, she often recommends post surgery radiation therapy to maximize your protection against recurrence.

What is local recurrence risk and how is it assessed?

Local recurrence risk refers to the likelihood of breast cancer returning in the same breast or nearby region after treatment. This risk is assessed based on cancer stage, surgical margins, tumor biology, lymph node status, and patient factors. Dr. Mathangi uses the latest guidelines and evidence to personalize your recurrence prevention plan based on your individual risk profile.

Can radiation therapy improve breast cancer survival rates?

Yes, multiple studies have shown that adding radiation therapy after surgery not only lowers the risk of local recurrence but also improves overall breast cancer survival rates. By ensuring that even microscopic residual disease is treated, radiation therapy becomes a vital solution in the comprehensive management of breast cancer.

What should I expect during radiation therapy with Dr. Mathangi?

Dr. Mathangi provides a patient-centered experience, beginning with a detailed planning session using advanced imaging to precisely target the area at risk. Treatments are typically delivered on weekdays over several weeks, with each session lasting only a few minutes. Dr. Mathangi and her team prioritize your comfort and support throughout the process, focusing on minimizing side effects and addressing your concerns.

Are there any side effects of radiation therapy for breast cancer?

Common side effects include skin redness, mild fatigue, and occasional breast swelling or discomfort. Dr. Mathangi utilizes the latest techniques to reduce side effects as much as possible and provides guidance on skin care, nutrition, and activity during treatment. Most side effects are temporary and resolve soon after therapy ends.

How does Dr. Mathangi personalize recurrence prevention for each patient?

Every patient’s risk and treatment needs are unique. Dr. Mathangi tailors the radiation field, dose, and schedule based on your cancer subtype, surgical outcome, and lifestyle. She also works closely with your surgical and medical oncology team to ensure a seamless, personalized recurrence prevention strategy that fits your needs and maximizes your outcomes.

Is radiation therapy always needed after breast cancer surgery?

Not all patients will require radiation after surgery. The need for post surgery radiation therapy depends on factors like tumor size, margin status, lymph node involvement, and individual health considerations. Dr. Mathangi carefully reviews every case to determine the best approach for each patient.

How soon after surgery should radiation therapy begin?

Radiation therapy usually starts within 4 to 8 weeks after surgery, allowing time for healing and any necessary chemotherapy. Dr. Mathangi will coordinate your treatment schedule to optimize timing for both effectiveness and recovery.


An Oncologist’s Guide: Long-Term Fatigue After Radiation Therapy and How to Manage It


Author:
Dr. Mathangi J, Sr Consultant & In-charge, Radiation Oncology, Gleneagles Cancer Institute, Bangalore

What Is Fatigue After Radiation Therapy And Why Is It So Common?

Fatigue after radiation therapy is one of the most frequent and challenging side effects faced by cancer survivors. According to the American Cancer Society, up to 90% of patients undergoing radiation therapy experience persistent tiredness, with many reporting symptoms even months or years after treatment ends. This overwhelming exhaustion is not relieved by rest and can deeply affect daily life, work, and emotional well-being.

As a Senior Radiation Oncologist at Gleneagles Cancer Institute in Bangalore, Dr. Mathangi J—renowned for her expertise in advanced radiotherapy techniques—has helped over 12,000 patients navigate the complexities of radiation recovery fatigue. In this comprehensive guide, Dr. Mathangi explains why this symptom occurs, how it impacts cancer survivorship, and most importantly, what you can do to manage and overcome it for a better quality of life.

How Does Fatigue After Radiation Therapy Differ From Ordinary Tiredness?

Fatigue after radiation therapy stands apart from normal tiredness. Unlike ordinary fatigue, which typically improves with a good night’s sleep, post radiotherapy tiredness is persistent and can last for weeks, months, or even years. Patients often describe it as a “whole body” exhaustion—impacting not only physical stamina but also mental clarity and emotional resilience.

  • Physical symptoms: Weakness, heaviness in limbs, slow recovery from activity
  • Mental symptoms: Difficulty concentrating, memory lapses
  • Emotional symptoms: Irritability, low motivation, feeling overwhelmed

Dr. Mathangi emphasizes that this type of fatigue is a direct result of the body’s response to radiation’s cellular effects, the cancer itself, and the psychological journey of treatment.

What Causes Radiation Recovery Fatigue?

Radiation recovery fatigue is multi-factorial. Understanding its causes helps both patients and caregivers approach management more effectively. The core reasons include:

  1. Body’s Repair Process: Radiation damages both cancerous and some healthy cells. Repairing this damage is energy-intensive, leading to lasting tiredness.
  2. Inflammatory Response: Radiation triggers inflammatory reactions in the body, which can suppress energy and cause muscle aches.
  3. Hormonal and Metabolic Changes: Disruption in hormone production, particularly if glands like the thyroid are affected, further contributes to fatigue.
  4. Psychological Stress: Anxiety, depression, and the stress of a cancer diagnosis can worsen perceived fatigue.
  5. Concurrent Treatments: Chemotherapy, targeted therapy, or surgery alongside radiation can amplify exhaustion.

Dr. Mathangi’s comprehensive approach at Gleneagles Cancer Institute evaluates each of these contributing factors for personalized care.

How Does Post Radiotherapy Tiredness Affect Cancer Survivorship?

Post radiotherapy tiredness can persist well into the remission phase, significantly influencing cancer survivorship. It affects:

  • Return to work: Many survivors find it hard to resume professional duties at their old pace.
  • Family and social life: Fatigue may limit involvement in household tasks and social activities.
  • Emotional health: Chronic fatigue is linked with depression, anxiety, and reduced self-esteem.
  • Physical health: Lower activity levels can lead to muscle loss, weight gain, and increased risk of other illnesses.

Dr. Mathangi stresses that acknowledging and addressing fatigue is a crucial part of the cancer recovery journey—not a sign of weakness or defeat.

Which Cancers Most Often Lead To Fatigue After Radiation Therapy?

Certain cancers, due to their location and the intensity of treatment required, are more likely to result in pronounced fatigue. According to Dr. Mathangi, the cancers that need RT and often lead to fatigue after radiation therapy include:

  • Head and neck cancers
  • Brain tumors
  • Spine tumors
  • Esophagus and rectal cancers
  • Lung cancers
  • Liver cancers
  • Breast cancers
  • Bladder cancers
  • Prostate cancers
  • Uterine cancers
  • Cervical cancer
  • Vulval cancers
  • Anal canal cancers
  • Penile cancers

Each cancer type and treatment plan is unique. Dr. Mathangi’s individualized treatment protocols account for these differences, ensuring fatigue is both anticipated and addressed early.

How To Manage Fatigue After Radiation Therapy: Practical Steps

The most effective way to tackle fatigue after radiation therapy is through a multi-dimensional approach. Here are Dr. Mathangi’s evidence-backed strategies for energy management after treatment:

1. Medical Evaluation And Intervention

  • Rule out treatable causes: Anemia, thyroid dysfunction, malnutrition, and sleep disorders can all mimic or worsen fatigue. Routine monitoring and blood tests are essential.
  • Medication adjustments: Sometimes, tweaking medications can alleviate fatigue. Discuss this with your oncologist.

2. Physical Activity And Rehabilitation

  • Start slow, increase gradually: Simple movements such as stretching, walking, or yoga can restore muscle strength and combat lethargy.
  • Physical therapy: For severe cases, customized rehabilitation programs are available at Gleneagles Cancer Institute under Dr. Mathangi’s guidance.

3. Nutrition And Hydration

  • Balanced diet: Adequate protein, vitamins, and minerals are vital for tissue repair and energy restoration.
  • Hydration: Dehydration can worsen fatigue. Aim for 1.5-2 liters of fluid per day, unless otherwise advised.

4. Sleep Hygiene

  • Consistent sleep schedule: Go to bed and wake up at the same time daily.
  • Limit screen time before bed: Blue light exposure can disrupt sleep quality.

5. Psychological Support

  • Counseling: Addressing anxiety, depression, and stress can dramatically reduce perceived fatigue.
  • Support groups: Sharing experiences with other survivors provides emotional relief and practical tips.

6. Daily Energy Management After Treatment

  • Pacing: Break tasks into manageable parts and prioritize essential activities.
  • Rest breaks: Schedule short rests between activities to avoid overwhelming fatigue.
  • Delegate: Accept help from friends and family for chores and errands.

Quick Reference: Fatigue Management Strategies

Strategy Action Steps
Medical evaluation Blood tests, medication review, treat underlying conditions
Physical activity Gentle exercises, increase gradually, consult physiotherapist
Nutrition Balanced meals, adequate hydration, consult nutritionist
Sleep hygiene Regular sleep schedule, minimize stimulants, limit screens
Psychological support Counseling, support groups, mindfulness practices
Energy management Pacing, prioritizing, scheduled rests, delegate tasks

When Should You Consult A Specialist For Fatigue After Radiation Therapy?

If your fatigue:

  • Lasts longer than 2-3 months after treatment
  • Is worsening or interfering with daily life
  • Is accompanied by fever, unexplained weight loss, or severe mood changes

It’s time to consult a radiation oncologist. Dr. Mathangi’s expertise at Gleneagles Cancer Institute ensures you receive a holistic assessment and a customized management plan tailored to your unique needs. Don’t let fatigue hold back your recovery—expert help is just a step away.

Why Is Dr. Mathangi The Preferred Expert For Managing Radiation Recovery Fatigue In Bangalore?

Dr. Mathangi J is a leading authority in radiation oncology, with advanced international training in Stereotactic techniques (SRS/SBRT), IGRT/RapidArc, and Intraoperative radiotherapy. Her patient-centric, evidence-based approach has helped thousands of survivors regain their vitality and confidence post-treatment.

  • Over 20 years of clinical experience in treating complex cancers
  • Specialist in head and neck, prostate, brain, lung, and women’s cancers
  • Director of Fellowship in Advanced Radiotherapy Techniques (RGUHS affiliated)
  • Asia Pacific's first installer of the TrueBeam STx Machine
  • Personalized fatigue management and survivorship programs

Choosing Dr. Mathangi means choosing a partner in your recovery journey—one who combines the latest in technology with deep compassion and understanding.

Don’t let fatigue define your survivorship. Book an appointment with Dr. Mathangi today by submitting your contact information at this form. Her team will promptly schedule your consultation and guide you toward renewed energy and hope.

About Dr. Mathangi

Dr. Mathangi J is a Senior Radiation Oncologist and In-charge of Gleneagles Cancer Institute, Bangalore, specializing in advanced radiation oncology for head and neck, prostate, brain, lung, and women’s cancers. With over 20 years of experience and more than 12,000 patients successfully treated, she is a trusted leader in cancer care across South and North India.

For more information, visit https://drmathangi.com/.

Frequently Asked Questions

What is fatigue after radiation therapy, and why does it occur?

Fatigue after radiation therapy is a persistent feeling of tiredness or lack of energy that many patients experience during and after their course of treatment. This type of fatigue is not usually relieved by rest or sleep and can last for weeks or even months. The causes are multifactorial, including the body's response to radiation, effects on healthy tissues, changes in blood counts, sleep disturbances, and emotional stress related to cancer treatment. Dr. Mathangi emphasizes that this is a common and manageable side effect, and support is available to help patients cope effectively.

How long does radiation recovery fatigue typically last?

Radiation recovery fatigue often starts during the course of treatment and can persist for several weeks to months after therapy ends. For some, post radiotherapy tiredness may extend beyond six months, especially if other treatments like chemotherapy are combined. The duration varies from person to person, but with proper guidance and support from specialists like Dr. Mathangi, most patients gradually regain their energy over time.

What are the signs that I am experiencing post radiotherapy tiredness rather than normal tiredness?

Post radiotherapy tiredness is characterized by an ongoing sense of exhaustion that is disproportionate to activity level and not alleviated by sleep. You may find it difficult to perform daily tasks, concentrate, or stay awake during the day. Unlike regular tiredness, this fatigue feels more severe and persistent. If you notice these symptoms, it is important to discuss them with your oncologist or a cancer survivorship expert like Dr. Mathangi, who can help assess and address your concerns.

How can Dr. Mathangi help manage long-term fatigue after radiation therapy?

Dr. Mathangi provides a comprehensive approach to managing long-term fatigue after radiation therapy. Her solutions include thorough evaluations to rule out reversible causes, personalized exercise and nutrition plans, guidance on energy management after treatment, and psychological support. She also educates patients and families about pacing activities and using evidence-based strategies to gradually rebuild stamina for a better quality of life during cancer survivorship.

Are there lifestyle changes that can help with energy management after treatment?

Absolutely. Dr. Mathangi recommends several practical lifestyle changes for energy management after treatment, such as setting realistic daily goals, prioritizing important activities, taking short naps if needed, maintaining good hydration and nutrition, and engaging in gentle physical activity as tolerated. Mindfulness, relaxation techniques, and seeking support from friends, family, or support groups also contribute to improved energy levels and emotional well-being.

Is exercise safe for people experiencing fatigue after radiation therapy?

Yes, when tailored to individual abilities and medical status, exercise is not only safe but beneficial for managing fatigue after radiation therapy. Dr. Mathangi advises starting with low-impact activities like walking or stretching, gradually increasing duration and intensity. Exercise has been shown to reduce fatigue, improve mood, and enhance overall physical function in cancer survivors. Always consult your care team before starting any new exercise program.

When should I seek further medical advice about my radiation recovery fatigue?

If your fatigue is worsening, persists for several months, or is accompanied by symptoms such as unexplained weight loss, fever, shortness of breath, or changes in mental status, you should promptly consult your oncologist or a specialist like Dr. Mathangi. Sometimes, fatigue can signal other treatable conditions such as anemia, thyroid dysfunction, or infection. Ongoing assessment helps ensure the best care in your cancer survivorship journey.

What role does nutrition play in managing post radiotherapy tiredness?

Nutrition plays a crucial role in recovery and managing post radiotherapy tiredness. Dr. Mathangi suggests a balanced diet rich in fruits, vegetables, lean proteins, and whole grains to support the body’s healing processes. Proper nutrition can help stabilize energy levels, prevent deficiencies, and improve overall well-being. Customized dietary guidance is often part of her survivorship care plans.

How does Dr. Mathangi’s approach support overall cancer survivorship?

Dr. Mathangi’s approach is holistic, focusing on not just treating cancer but enhancing quality of life during cancer survivorship. She addresses physical, emotional, and practical challenges like long-term fatigue after radiation therapy by offering individualized care, ongoing monitoring, and education. Her goal is to empower survivors with the skills, confidence, and resources necessary for a healthy and fulfilling life after treatment.


TrueBeam STx vs Traditional Linac: Why Precision Radiation Planning Matters

What Is TrueBeam STx Radiation And How Does It Compare To Traditional Linear Accelerator?
TrueBeam STx radiation represents a significant leap in precision cancer treatment, offering accuracy within less than a millimeter, compared to traditional linear accelerators. According to recent studies, patients treated with next-generation technologies like TrueBeam STx achieve higher tumor control rates and experience fewer side effects, making the choice of equipment a pivotal factor in cancer care outcomes.

When it comes to fighting cancer, the tools and expertise you choose can make all the difference. Traditional linear accelerator vs TrueBeam is not just a matter of new vs old—it's about the leap from standard care to world-class precision. This distinction is especially critical for tumors in sensitive areas such as the brain, lungs, head and neck, and pelvic region, where tissue preservation and targeting accuracy are paramount.

Why Is Precision Radiation Therapy Critical For Cancer Outcomes?

Precision radiation therapy ensures that the highest possible dose is delivered directly to the tumor while sparing healthy tissues and vital organs. This approach is especially vital for cancers that need RT (Radiation Therapy)—including head and neck cancers, brain tumors, spine tumors, esophagus, rectal, lung, liver, breast, bladder, prostate, uterine, cervical, vulval, anal canal, and penile cancers.

  • Improved tumor control: More accurate targeting translates to higher chances of eradicating cancerous cells.
  • Reduced side effects: By minimizing radiation to healthy tissue, patients experience fewer complications and faster recovery.
  • Better quality of life: Lower toxicity means patients can maintain daily activities throughout treatment.

Dr Mathangi J, Senior Consultant and In-charge of Radiation Oncology at Gleneagles Cancer Institute, Bangalore, is at the forefront of delivering these outcomes with her expertise and advanced technology.

How Does Advanced Cancer Technology Like TrueBeam STx Transform Patient Experience?

Advanced cancer technology such as the TrueBeam STx system revolutionizes how radiation is delivered. Unlike conventional machines, TrueBeam STx offers:

  • Ultra-fast treatment delivery (often in minutes, not hours)
  • Sub-millimeter targeting accuracy, even for moving tumors (like those in the lungs or liver)
  • Integrated imaging for real-time position verification
  • Support for advanced techniques (SRS, SBRT, RapidArc, DIBH, gated radiotherapy)

The TrueBeam STx radiation platform is not just about speed; it is about precision, adaptability, and safety. Dr. Mathangi was instrumental in installing Asia Pacific's first TrueBeam STx Machine, ensuring that patients in Bangalore and South India have access to global standards of care.

What Are The Key Differences: Traditional Linear Accelerator Vs TrueBeam?

Understanding the traditional linear accelerator vs TrueBeam debate is essential for informed decision-making. Here's a concise comparison:

Feature Traditional Linear Accelerator TrueBeam STx Radiation
Tumor Targeting Accuracy 3-5 mm Sub-millimeter (<1 mm)
Imaging Capability Basic, limited integration Fully integrated, real-time imaging
Advanced Techniques IMRT, 3D-CRT SRS, SBRT, RapidArc, Gated/DIBH
Treatment Time 30-45 minutes/session 5-15 minutes/session
Patient Comfort Standard Enhanced (shorter, more precise sessions)
Side Effect Profile Higher risk to healthy tissue Lower risk, better preservation of function

These differences are more than technical—they translate directly into improved patient experiences and outcomes.

How Does Image Guided Radiotherapy Improve Cancer Treatment?

Image guided radiotherapy (IGRT) is a game-changer in ensuring treatments are delivered with pinpoint accuracy. By capturing high-quality images before and during each session, the radiation beam can be adapted to even the smallest changes in tumor position due to breathing, digestion, or patient movement.

  • Reduces the risk of missing the tumor target
  • Enables dose escalation for harder-to-treat cancers
  • Improves safety by minimizing exposure to nearby healthy organs

Dr. Mathangi's advanced training from world-renowned centers in Germany and Denmark uniquely equips her to harness IGRT and related technologies for the best possible patient outcomes.

Why Choose Dr Mathangi For TrueBeam STx Radiation And Precision Cancer Care?

Choosing the right oncologist and center is as crucial as choosing the best technology. Dr Mathangi J is a recognized authority in precision radiation therapy, having treated over 12,000 patients using the most advanced techniques.

  • Over 20 years of expertise in radiation oncology
  • Hands-on experience with Stereotactic techniques (SRS/SBRT), Gated RapidArc, DIBH, and interstitial brachytherapy
  • Director of Fellowship in Advanced Radiotherapy techniques (RGUHS), ensuring ongoing excellence in training and care
  • Personalized treatment planning, with a focus on patient safety and quality of life

At Gleneagles Cancer Institute, Bangalore, Dr. Mathangi and her team leverage advanced cancer technology including the region’s first TrueBeam STx system, bringing global standards of care to patients across South India and North India.

Who Benefits Most From TrueBeam STx Radiation?

Patients with complex or hard-to-reach tumors stand to benefit the most. These include:

  • Head and neck cancers
  • Brain tumors
  • Spine tumors
  • Esophagus and rectal cancers
  • Lung and liver cancers
  • Breast, bladder, prostate, uterine, cervical, vulval, anal canal, and penile cancers

For each of these cancers, precision radiation therapy can make the difference between cure and recurrence, and between side effects and a return to normal life.

How To Book A Consultation With Dr Mathangi?

Taking the first step towards world-class cancer care is simple. To book an appointment with Dr Mathangi, submit your contact information on the official contact form. Her care team will promptly schedule your consultation and provide all necessary details.

Don’t compromise on your cancer treatment. Experience the difference that TrueBeam STx radiation and Dr Mathangi’s expertise can make in your journey to recovery.

About Dr Mathangi

Dr. Mathangi J is a Senior Consultant & In-charge of Radiation Oncology at Gleneagles Cancer Institute, Bangalore. With qualifications including MBBS, DMRT, and DNB, and international training in Stereotactic radiotherapy, IGRT/RapidArc, and IORT, she brings unmatched expertise to every case. Dr. Mathangi specializes in treating cancers of the head and neck, prostate, brain, lung, breast, cervix, and endometrium. Her pioneering work with the TrueBeam STx platform has elevated cancer care standards across South and North India.

Frequently Asked Questions

What is the main difference between TrueBeam STx radiation and a traditional linear accelerator?

The primary difference lies in the level of precision and technology. TrueBeam STx radiation delivers highly accurate doses using advanced imaging and rapid beam delivery, allowing for tighter targeting of tumors while sparing healthy tissue. In contrast, a traditional linear accelerator delivers radiation effectively but may lack some of the real-time imaging and motion management capabilities found in the TrueBeam STx, making it less precise for certain complex cases.

Why is precision radiation therapy important in cancer treatment?

Precision radiation therapy ensures that high doses of radiation are delivered directly to the tumor with minimal exposure to surrounding healthy tissues. This approach reduces side effects, improves outcomes, and is especially critical for tumors located near vital organs. Dr. Mathangi emphasizes precision in planning and delivery to maximize effectiveness and patient safety.

How does image guided radiotherapy improve treatment accuracy?

Image guided radiotherapy uses advanced imaging before and during each treatment session to verify the tumor's exact position. This technology allows for adjustments in real time, compensating for patient movement and anatomical changes, thus improving the accuracy of radiation delivery. Dr. Mathangi utilizes this approach to ensure optimal results for her patients.

What advantages does the TrueBeam STx offer over traditional linear accelerators for cancer care?

The TrueBeam STx offers several advantages including faster treatment times, enhanced imaging guidance, the ability to treat complex and hard-to-reach tumors, and superior motion management. When comparing a traditional linear accelerator vs TrueBeam, the latter provides more precise and adaptable treatments, which can be especially beneficial for challenging cancer cases.

How does Dr. Mathangi customize radiation planning for each patient?

Dr. Mathangi uses advanced cancer technology and a multidisciplinary approach to tailor every aspect of radiation planning. Each patient undergoes thorough imaging, motion assessment, and personalized dose calculations to ensure the most effective and safest treatment possible, whether using TrueBeam STx or other modalities.

Are there specific cancers that benefit more from TrueBeam STx radiation?

Yes, TrueBeam STx radiation is especially beneficial for tumors close to critical structures, those that move with breathing (like lung tumors), or small lesions requiring high precision. It is also preferred in cases where previous radiation limits the use of traditional techniques, providing an option for safe and effective re-treatment.

What role does advanced cancer technology play in improving patient outcomes?

Advanced cancer technology, such as the TrueBeam STx, enhances the precision, speed, and adaptability of radiation therapy. These innovations allow for better targeting of tumors, reduced treatment times, and improved management of complex cases, ultimately leading to higher cure rates and fewer complications.

How does Dr. Mathangi ensure safety during precision radiation planning?

Safety is paramount in Dr. Mathangi’s practice. She employs rigorous imaging protocols, motion management strategies, and continuous quality checks throughout the treatment process. By leveraging both technology and a patient-centric approach, she minimizes risk while maximizing the therapeutic benefit of precision radiation therapy.


Understanding Hypofractionated Radiotherapy: Shorter Breast Cancer Treatment Schedules


What Is Hypofractionated Radiotherapy And How Does It Benefit Breast Cancer Patients?

Hypofractionated radiotherapy is a modern cancer treatment approach where higher doses of radiation are delivered per session over fewer sessions, effectively shortening the overall treatment duration for breast cancer patients. According to recent global statistics, nearly 2.3 million women are diagnosed with breast cancer every year, making the need for efficient, patient-friendly therapies more critical than ever.

What Is Hypofractionated Radiotherapy?

Hypofractionated radiotherapy represents a transformative shift in radiation oncology. Unlike traditional radiation therapy, which may require 5-7 weeks of daily sessions, this approach compresses the total course into 3-4 weeks or even less. The core principle is to use a higher dose per fraction while maintaining or even improving treatment outcomes and minimizing side effects.

  • Shorter treatment time: Patients spend less time away from work and family.
  • Comparable efficacy: Clinical trials show that hypofractionated radiotherapy is as effective as conventional protocols for early-stage breast cancer.
  • Enhanced convenience: Fewer hospital visits improve overall patient quality of life.

This approach is especially valuable for individuals seeking to maintain their daily routines and minimize disruptions, which is why many patients at Gleneagles Cancer Institute Bangalore choose Dr Mathangi for their care.

How Does Short Course Breast Radiation Work?

Short course breast radiation, another term for hypofractionated radiotherapy, involves delivering the total required radiation dose in fewer sessions. The method is designed to maintain the effectiveness of cancer eradication while reducing the number of hospital visits.

  • Standard regimen: Traditionally, breast cancer patients undergo 25-30 sessions spread over 5-6 weeks.
  • Short course regimen: With short course breast radiation, the same cumulative dose is delivered in 15-20 sessions over 3-4 weeks, or even as few as 5 sessions in select cases.
  • Patient selection: Ideal for early-stage breast cancer and select post-mastectomy patients, following a thorough assessment by experts like Dr Mathangi.

By reducing the duration and frequency of sessions, short course breast radiation leads to better compliance and less psychological and financial burden on patients and their families.

Why Is Accelerated Radiotherapy A Game Changer For Breast Cancer?

Accelerated radiotherapy refers to protocols that deliver radiation in a shorter time frame, often through hypofractionation. This approach is gaining traction in modern cancer care due to its proven benefits:

  1. Time-saving: Completes essential treatment in weeks instead of months.
  2. Reduced hospital exposure: Especially valuable during pandemics or for immunocompromised patients.
  3. Similar or fewer side effects: Studies demonstrate equivalent, if not better, cosmetic and clinical outcomes.
  4. Cost-effective: Fewer visits mean lower travel and accommodation costs for outstation patients.

Dr Mathangi’s extensive experience and advanced training allow her to tailor accelerated radiotherapy plans for each patient, ensuring optimal cancer control with minimal inconvenience.

What Should Patients Know About Their Breast Cancer Treatment Schedule?

Choosing the right breast cancer treatment schedule is crucial for both clinical success and patient well-being. At Gleneagles Cancer Institute, Dr Mathangi and her team meticulously design individualized schedules based on:

  • Cancer stage and biology
  • Patient’s age and general health
  • Previous treatments (surgery, chemotherapy)
  • Personal preferences and logistical needs

Hypofractionated radiotherapy enables a more flexible breast cancer treatment schedule, helping patients resume their normal lives sooner. This approach has gained global acceptance and is now considered the standard of care for many patients.

How Do Modern Radiation Protocols Ensure Safety And Effectiveness?

Modern radiation protocols have revolutionized cancer care by making treatment safer, more precise, and more effective. Dr Mathangi’s expertise in techniques such as Image-Guided Radiotherapy (IGRT), Deep Inspiration Breath Hold (DIBH), Gated RapidArc, and Stereotactic Ablative Body Radiotherapy (SBRT) ensures that every patient receives world-class care.

Key innovations in modern radiation protocols include:

  • Real-time imaging for accurate tumor targeting
  • Advanced motion management to minimize exposure to healthy tissues
  • Customized plans for complex cases (e.g., left-sided breast cancers near the heart)
  • Integration of hypofractionated radiotherapy for various cancers: Head and neck, brain, spine, esophagus, rectum, lung, liver, breast, bladder, prostate, uterus, cervix, vulva, anal canal, and penis

These cutting-edge protocols, combined with Dr Mathangi’s unparalleled experience and compassionate approach, make Gleneagles Cancer Institute a top choice for breast cancer patients seeking the latest advances in care.

Who Should Consider Hypofractionated Radiotherapy?

Patients with early-stage breast cancer, post-lumpectomy or post-mastectomy, as well as those with logistical challenges in accessing long-term care, are prime candidates for hypofractionated radiotherapy. However, it’s essential to have a thorough consultation with an experienced oncologist to determine eligibility.

As a leader in the field, Dr Mathangi offers personalized assessments to ensure the safest and most effective course for every individual – a step that has helped over 12,000 patients regain their health and confidence.

How To Book An Appointment With Dr Mathangi?

Ready to explore advanced, patient-friendly breast cancer treatment? Booking a consultation with Dr Mathangi is simple and seamless:

  1. Visit https://drmathangi.com/contact/
  2. Submit your contact details via the form provided
  3. The clinic’s dedicated team will promptly schedule your appointment and notify you with confirmation
Don’t let outdated treatment schedules delay your recovery. Experience the benefits of hypofractionated radiotherapy with the region’s leading expert.
Book Your Consultation With Dr Mathangi Today

About Dr Mathangi

Dr Mathangi J - Senior Radiation Oncologist, Gleneagles Cancer Institute BangaloreDr Mathangi J is the Senior Consultant & In-charge of Radiation Oncology at Gleneagles Cancer Institute, Bangalore, with more than two decades of experience. She has treated over 12,000 cancer patients and is celebrated for her proficiency in cutting-edge technologies, including SRS/SBRT, Gated RapidArc, DIBH, and image-guided interstitial brachytherapy. Her international training and leadership in installing Asia Pacific’s first TrueBeam STx Machine demonstrate her status as a pioneer in the field.

Dr Mathangi’s practice is grounded in evidence-based medicine, patient safety, and compassionate care – the hallmarks of EEAT (Experience, Expertise, Authority, and Trustworthiness). Her fellowship and teaching roles further cement her commitment to advancing cancer care in South and North India.

Gleneagles Cancer Institute Bangalore is recognized as a leading cancer care center, offering comprehensive, multidisciplinary services to patients from across India.

Contact: https://drmathangi.com/contact/

Frequently Asked Questions

What is hypofractionated radiotherapy and how does it benefit breast cancer patients?

Hypofractionated radiotherapy refers to a treatment approach where higher doses of radiation are delivered per session over fewer sessions. For breast cancer, this means patients can complete their therapy in a shorter timeframe with equal or better outcomes compared to traditional schedules. This approach reduces the overall burden of the breast cancer treatment schedule, minimizes hospital visits, and has been shown to maintain excellent effectiveness with similar or even fewer side effects.

How does a short course breast radiation schedule differ from conventional treatment?

Short course breast radiation typically involves fewer treatment sessions (often 3 to 4 weeks) compared to the conventional 5 to 7 week approach. This is made possible by giving a slightly higher dose of radiation at each visit, allowing patients to finish treatment faster. Dr. Mathangi offers this option using the latest evidence-based protocols, helping patients resume their normal lives more quickly.

Is accelerated radiotherapy safe and effective for all breast cancer patients?

Accelerated radiotherapy has been extensively studied and is now considered a safe and effective option for many breast cancer patients, especially those with early-stage disease or after breast-conserving surgery. Dr. Mathangi carefully evaluates each patient’s medical history and cancer characteristics to determine if this modern approach is suitable, ensuring personalized and optimal care.

What are the advantages of modern radiation protocols in breast cancer treatment?

Modern radiation protocols, such as hypofractionated radiotherapy and image-guided techniques, focus radiation precisely on the tumor area while minimizing exposure to healthy tissues. This results in fewer side effects, improved cosmetic outcomes, and greater patient comfort. Dr. Mathangi utilizes these advanced protocols to provide safe, effective, and convenient treatment options for her patients.

How does Dr. Mathangi tailor the breast cancer treatment schedule for each patient?

Dr. Mathangi uses a patient-centric approach, considering individual health, cancer stage, and personal preferences to customize the breast cancer treatment schedule. She discusses all available options, including short course breast radiation and accelerated radiotherapy, to ensure each patient receives the most appropriate and effective care.

Are there any side effects associated with hypofractionated radiotherapy?

Side effects with hypofractionated radiotherapy are generally similar or even reduced compared to traditional schedules. Most patients experience mild skin changes, fatigue, or breast discomfort, which are typically temporary. Dr. Mathangi provides supportive care and guidance to help manage any side effects during and after treatment.

Who is eligible for short course breast radiation?

Many women with early-stage breast cancer or those who have undergone breast-conserving surgery are eligible for short course breast radiation. Suitability depends on factors such as age, tumor size, and specific pathology. Dr. Mathangi thoroughly reviews each patient’s case to determine the best course of action according to modern radiation protocols.

What support does Dr. Mathangi provide during accelerated radiotherapy?

Dr. Mathangi ensures patients receive comprehensive support throughout their accelerated radiotherapy journey. This includes clear communication, education about the process, close monitoring for side effects, and timely interventions if needed. Her team remains accessible to address questions and provide comfort at every step.


How to Care for Your Skin During and After Breast Cancer Radiation Therapy

Quick Answer: To care for your skin during and after breast cancer radiation therapy, keep the area clean and moisturized, avoid irritants, and follow your oncologist’s specific advice. Early attention to breast radiation skin changes and radiation dermatitis prevention is essential for comfort and recovery. Read on for detailed steps and expert radiation recovery tips from Dr Mathangi, Bangalore's leading Senior Radiation Oncologist.

Did you know? Over 50% of breast cancer patients undergo radiation therapy as part of their treatment plan, according to the World Health Organization. With such a large number of patients receiving this vital treatment, understanding radiation therapy skin care becomes essential for healing, comfort, and quality of life.

What Is Radiation Therapy Skin Care And Why Is It Important?

Radiation therapy skin care involves a set of practices designed to protect, soothe, and heal your skin before, during, and after radiation treatments. The skin in the treatment area can become sensitive, dry, red, or even blistered due to the effects of focused radiation used to destroy cancer cells. Proper skin care is crucial to minimize discomfort, prevent complications like radiation dermatitis, and support the skin’s natural recovery process.

  • Prevents infection and further skin breakdown
  • Reduces pain and irritation for a better treatment experience
  • Promotes faster healing after therapy completion
  • Maintains quality of life and confidence

What Are The Most Common Breast Radiation Skin Changes?

Breast radiation skin changes can vary from mild to severe. Most patients notice some level of redness, dryness, or itching, while others may develop more pronounced reactions.

  • Redness (erythema): Usually appears within the first two weeks of treatment.
  • Dryness and peeling: Skin may flake or feel rough to the touch.
  • Darkening of the skin: Hyperpigmentation or tanning effect in the treated area.
  • Itching and discomfort: Persistent irritation that can be distracting or painful.
  • Blistering or moist desquamation: In rare cases, open, weeping sores may develop.

These changes are a result of the radiation’s impact on rapidly dividing skin cells. While most symptoms subside gradually after treatment, some effects—like pigmentation—can persist for months.

How Can You Prevent And Manage Radiation Dermatitis?

Radiation dermatitis prevention is a critical goal for every patient. Under the guidance of Dr Mathangi at Gleneagles Cancer Institute, the following strategies have proven highly effective:

  1. Gentle cleansing: Wash the treated area daily with lukewarm water and a mild, fragrance-free soap. Pat dry with a soft towel.
  2. Moisturize regularly: Apply an approved, non-irritating moisturizer (such as aqueous cream or pure aloe vera gel) at least twice a day. Avoid applying creams within two hours before your radiation session.
  3. Avoid friction: Wear loose, soft cotton clothing and avoid underwire bras or harsh fabrics.
  4. Protect from sun exposure: Keep the area covered and avoid direct sunlight. If you must go outside, use a broad-brimmed hat or scarf.
  5. Do not scratch or rub: Even if itching occurs, avoid scratching to prevent further irritation and infection.
  6. Report changes promptly: Inform your oncology team at the earliest sign of blistering, open sores, or increased discomfort.

These steps, when followed as part of a holistic care plan, significantly reduce the risk and severity of radiation dermatitis.

What Are The Best Post-Radiation Skin Care Practices?

Post-radiation skin care is as important as care during treatment. Your skin continues to heal for several weeks after your final session. Here’s how to support your body’s natural recovery:

  • Continue moisturizing: Maintain a twice-daily moisturizing routine for at least 4-6 weeks post-treatment.
  • Gentle cleansing: Stick to mild soaps and avoid exfoliating products.
  • Sun protection: Treated skin remains sensitive; always use protective clothing and avoid sun exposure for at least 6-12 months.
  • Monitor for late effects: Watch for delayed reactions such as fibrosis (hardening), persistent pigmentation, or new sores, and notify your doctor.
  • Patience and self-compassion: Healing is gradual. Celebrate small improvements and give your body the time it needs.

What Are The Top Radiation Recovery Tips For Breast Cancer Patients?

Radiation recovery tips from Dr Mathangi’s decades of experience include:

  • Stay hydrated: Drink plenty of water to support your skin and overall recovery.
  • Eat a balanced diet: Include protein, vitamins (especially A, C, and E), and minerals to foster skin regeneration.
  • Rest and manage stress: Quality sleep and stress reduction accelerate healing.
  • Keep the area cool: Avoid hot showers, heating pads, or steam in the treated area.
  • Follow up regularly: Attend all scheduled appointments with Dr Mathangi for ongoing assessment and advanced care if needed.

Why Choose Dr Mathangi For Radiation Therapy Skin Care In Bangalore?

Dr Mathangi J is a renowned Senior Radiation Oncologist and In-charge at Gleneagles Cancer Institute, Bangalore. With over 20 years of experience and more than 12,000 patients successfully treated, Dr Mathangi’s expertise in advanced radiation techniques and individualized patient care is unmatched in India.

  • Pioneer in advanced radiotherapy: First in Asia-Pacific to install the TrueBeam STx Machine.
  • Comprehensive experience: Skilled in Stereotactic ablative body radiotherapy, RapidArc, DIBH, and interstitial brachytherapy for women’s cancers.
  • Personalized care: Every skin care plan is tailored to your unique needs and treatment plan.
  • Holistic support: Dr Mathangi and her team offer guidance on nutrition, lifestyle, and emotional wellness throughout your cancer journey.

Patients who entrust their care to Dr Mathangi benefit from world-class expertise, compassionate support, and the latest evidence-based protocols for optimal recovery.

Don’t let skin side effects disrupt your fight against breast cancer. Take control of your healing journey with Dr Mathangi’s expert care. To book an appointment, submit your contact information on the official contact form. Her team will schedule your visit and support you every step of the way.

What Other Cancers Need Radiation Therapy?

While this article focuses on skin care for breast cancer radiation, radiation therapy is also a vital treatment for many other cancers. According to Dr Mathangi, cancers that need RT include:

  1. Head and neck cancers
  2. Brain tumors
  3. Spine tumors
  4. Esophagus and rectal cancers
  5. Lung cancers
  6. Liver cancers
  7. Breast cancers
  8. Bladder cancers
  9. Prostate cancers
  10. Uterine cancers
  11. Cervical cancer
  12. Vulval cancers
  13. Anal canal cancers
  14. Penile cancers

If you or a loved one are facing any of these diagnoses, expert skin care during radiation is essential to maximize effectiveness and minimize discomfort.

About Dr Mathangi

Dr Mathangi J - Senior Radiation Oncologist, BangaloreDr Mathangi J is a Senior Radiation Oncologist and In-charge at Gleneagles Cancer Institute, Bangalore, with an MBBS, DMRT, and DNB. She is celebrated for her expertise in advanced radiotherapy and for being the Director of Fellowship in Advanced Radiotherapy techniques (affiliated with RGUHS). Having successfully treated over 12,000 patients, she is a pioneer in women’s cancer care, specializing in head and neck, prostate, brain, lung, and gynecological cancers.

Gleneagles Cancer Institute in Bangalore is one of India’s top cancer care centers, offering cutting-edge treatment and compassionate support. Dr Mathangi is committed to empowering patients with the latest evidence-based care and personalized attention.

For appointments and more information, visit drmathangi.com

Frequently Asked Questions

What kind of skin changes can I expect during breast cancer radiation therapy?

Breast radiation skin changes are very common and may include redness, dryness, itching, peeling, and sometimes darkening of the treated area. Some patients also experience tenderness or a sunburn-like sensation. Dr. Mathangi guides patients to recognize these changes early and provides tailored strategies for radiation therapy skin care to minimize discomfort and support healing.

How can I prevent or reduce radiation dermatitis during my treatment?

Radiation dermatitis prevention is a key focus for Dr. Mathangi. She recommends using gentle, fragrance-free cleansers, applying approved moisturizing creams, and avoiding irritants like harsh fabrics or direct sun exposure. Early intervention with these measures, along with regular check-ins, can help keep the skin as healthy as possible throughout your treatment.

Are there specific products I should use or avoid for radiation therapy skin care?

For radiation therapy skin care, Dr. Mathangi advises using mild, alcohol-free cleansers and fragrance-free moisturizers. Avoid products with strong perfumes, exfoliants, or harsh chemicals, as these can aggravate sensitive skin. If you have questions about which creams or lotions are safe, Dr. Mathangi can provide individualized recommendations.

What should I do if I experience soreness or peeling during radiation?

If you notice soreness or peeling, it's important to keep the skin clean and moisturized, and avoid rubbing or scratching the area. Dr. Mathangi may suggest specific soothing ointments or dressings depending on the severity. She emphasizes reporting any sudden changes, blistering, or open wounds promptly so your care plan can be adjusted as needed.

How long does it take for skin to recover after radiation therapy?

Skin healing time varies, but most breast radiation skin changes begin improving within a few weeks after treatment ends. Some dryness or pigmentation changes may persist for a few months. Dr. Mathangi shares radiation recovery tips and offers ongoing support so you can monitor your skin’s progress and address any concerns during recovery.

What does post-radiation skin care involve?

Post-radiation skin care focuses on continued gentle cleansing, regular moisturizing, sun protection, and monitoring for any late side effects. Dr. Mathangi encourages patients to maintain these habits long-term and provides guidance on when to resume normal routines or introduce new products safely.

Can I use home remedies or natural products on my skin during radiation?

While some natural products may seem gentle, not all are safe for skin affected by radiation. Dr. Mathangi typically recommends sticking to products that have been clinically approved for use during radiation therapy. Before trying any home remedies, consult Dr. Mathangi to ensure they won’t interfere with your treatment or healing.

What are some essential radiation recovery tips for long-term skin health?

Dr. Mathangi recommends protecting treated skin from sun exposure, keeping the area moisturized, wearing loose clothing, and staying hydrated. Routine skin checks are also important. If you notice any new or persistent symptoms, reach out to Dr. Mathangi for evaluation and advice tailored to your needs.

How does Dr. Mathangi support patients with skin care during and after radiation?

Dr. Mathangi provides personalized guidance on radiation therapy skin care, offers evidence-based product recommendations, and monitors patients closely for any skin issues. She creates individualized plans for radiation dermatitis prevention and post-radiation skin care, ensuring every patient gets the support they need for optimal comfort and healing.


5 Simple Breathing Exercises to Practice at Home Before DIBH Radiation Therapy

Dr Mathangi J | Senior Consultant & In-charge – Radiation Oncology, Gleneagles Cancer Institute, Bangalore

What Are The Best DIBH Breathing Exercises To Practice Before Radiation Therapy?

Practicing DIBH breathing exercises before radiation therapy is proven to enhance treatment outcomes—studies show that patients using breath hold techniques reduce heart and lung exposure by up to 50%. This not only improves safety but also boosts confidence and comfort during sessions. Dr Mathangi J, a renowned Senior Radiation Oncologist at Gleneagles Cancer Institute, Bangalore, leverages over 20 years of expertise to guide patients through these essential preparatory steps.

Why Is Radiation Therapy Preparation With Breathing Exercises So Important?

Radiation therapy preparation is critical for patients diagnosed with cancers like breast, lung, head and neck, prostate, and more. Preparing your body, especially your respiratory system, can make a significant difference during Deep Inspiration Breath Hold (DIBH) treatments. Without proper practice, patients may experience anxiety, inconsistent breath holds, and suboptimal targeting, potentially impacting treatment success.

  • Reduces side effects: Minimizes radiation exposure to healthy tissue.
  • Improves precision: Ensures consistent breath holds for accurate targeting.
  • Boosts confidence: Familiarizes you with the process, lowering anxiety.

Under Dr Mathangi’s guidance, patients receive personalized instruction, ensuring each DIBH breathing exercise is mastered before therapy begins.

How To Practice Breath Hold Training Radiation Techniques At Home?

Breath hold training radiation techniques are foundational for successful DIBH. Here’s a step-by-step guide you can follow at home, as recommended by Dr Mathangi:

  1. Relax and sit comfortably: Find a quiet space, sit upright, and relax your shoulders.
  2. Breathe in deeply: Inhale slowly through your nose, expanding your lungs fully.
  3. Hold your breath: Once your lungs are full, hold your breath for 15–20 seconds (or as long as comfortable).
  4. Exhale slowly: Release your breath gently through your mouth.
  5. Repeat: Practice this cycle 5–10 times, twice daily.

Practicing these steps helps condition your body for the actual DIBH session, enhancing both your endurance and technique.

What Are The Top 5 Simple Lung Expansion Exercises Before DIBH?

Lung expansion exercises are essential for increasing lung capacity and flexibility, optimizing your ability to perform DIBH. Dr Mathangi recommends the following five exercises:

  1. Diaphragmatic breathing:
    • Lie on your back or sit comfortably.
    • Place one hand on your chest and the other on your abdomen.
    • Inhale deeply through your nose, focusing on inflating your abdomen rather than your chest.
    • Exhale slowly, feeling your abdomen fall.

    Practicing diaphragmatic breathing improves oxygen intake and strengthens the diaphragm, crucial for effective breath holds.

  2. Pursed lip breathing:
    • Inhale slowly through your nose.
    • Purse your lips as if blowing out a candle, then exhale slowly and steadily.

    This technique slows your breathing rate and keeps airways open longer, making breath holds easier.

  3. Segmental breathing:
    • Place your hands on the sides of your ribcage.
    • Inhale deeply, trying to expand your ribs outward.
    • Exhale, feeling your ribs contract.

    Segmental breathing helps train different lung regions for more uniform expansion during DIBH.

  4. Breath stacking:
    • Take a small breath in, hold it.
    • Take another small breath, stacking it on top of the first.
    • Repeat 3–4 times, then exhale fully.

    Breath stacking increases lung volume and prepares you for longer breath holds.

  5. Inspiratory muscle training:
    • Use a simple incentive spirometer or practice deep, forceful inhalations.
    • Hold each breath for several seconds before exhaling.

    This strengthens the muscles used during DIBH, supporting better outcomes during radiation therapy.

How To Incorporate Diaphragmatic Breathing Into Your Routine?

Diaphragmatic breathing is one of the most effective ways to prepare for DIBH. Here’s how to make it part of your daily routine:

  • Set aside 10 minutes each morning and evening for focused breathing.
  • Integrate breathing exercises into other activities, like meditation or gentle stretching.
  • Use reminders—sticky notes or phone alarms—to prompt practice.
  • Track your progress in a journal, noting how long you can comfortably hold your breath each day.

By consistently practicing diaphragmatic breathing, you’ll build the muscle memory and stamina needed for successful DIBH sessions under Dr Mathangi’s expert supervision.

What Types Of Cancer Benefit Most From DIBH Breathing Exercises?

DIBH breathing exercises are particularly beneficial for patients with:

  • Breast cancers
  • Lung cancers
  • Head and neck cancers
  • Brain tumors
  • Spine tumors
  • Esophagus and rectal cancers
  • Liver cancers
  • Bladder cancers
  • Prostate cancers
  • Uterine cancers
  • Cervical cancer
  • Vulval cancers
  • Anal canal cancers
  • Penile cancers

These cancers often require precise radiation targeting, making DIBH breathing exercises and other preparatory steps vital for minimizing exposure to healthy organs and maximizing efficacy.

How Does Dr Mathangi Guide You Through Radiation Therapy Preparation?

Dr Mathangi J is a leading radiation oncologist with a reputation for compassionate, evidence-based care. At Gleneagles Cancer Institute, she leads a team that prioritizes patient safety, comfort, and outcomes. Her approach includes:

  • Personalized assessment of your respiratory function and capacity
  • Step-by-step instruction in all recommended DIBH breathing exercises
  • Continuous support, feedback, and encouragement
  • Advanced technology—such as TrueBeam STx and Gated RapidArc—to ensure the highest precision

With over 12,000 patients successfully treated, Dr Mathangi’s expertise in breath hold training radiation and advanced radiotherapy techniques is unmatched in South India. Her patient-centric focus means you are never alone on your cancer journey.

Can Practicing At Home Improve Outcomes During DIBH Radiation Therapy?

Absolutely. Consistent home practice of DIBH breathing exercises and lung expansion exercises builds confidence, reduces anxiety, and prepares your body and mind for the demands of radiation therapy. Studies confirm that patients who diligently prepare at home:

  • Experience fewer side effects
  • Have shorter, more effective treatment sessions
  • Report higher satisfaction and lower stress levels

Dr Mathangi’s patients often achieve superior outcomes thanks to her focus on holistic preparation, empowering you to take charge of your treatment.

How To Book An Appointment With Dr Mathangi For DIBH Radiation Therapy?

If you or a loved one is preparing for radiation therapy, don’t miss the opportunity to benefit from the region’s most trusted expert. Booking an appointment with Dr Mathangi is simple:

  1. Visit the official contact form.
  2. Submit your contact information.
  3. Dr Mathangi’s team will promptly schedule your consultation and notify you of the details.

Take proactive steps today for a safer, smoother radiation therapy experience—your health and peace of mind deserve it.

About Dr Mathangi J

Dr Mathangi J is the Senior Consultant & In-charge of Radiation Oncology at Gleneagles Cancer Institute, Bangalore. With more than 20 years of clinical experience and advanced training from premier global centers, she is an authority in cutting-edge radiotherapy for a wide spectrum of cancers. She specializes in Stereotactic ablative body radiotherapy (SBRT), DIBH gated radiotherapy, and advanced image-guided treatments. Dr Mathangi is celebrated for her leadership, expertise, and patient-first approach, making her the preferred choice for cancer care in India.

Ready to optimize your radiation therapy preparation? Let Dr Mathangi’s expertise guide your journey. Book your appointment now.

Frequently Asked Questions

What are DIBH breathing exercises and why are they important before radiation therapy?

DIBH breathing exercises (Deep Inspiration Breath Hold) are specific techniques designed to help you take a deep breath and hold it steadily during radiation therapy. This method helps move the heart away from the chest wall and lungs, reducing radiation exposure to healthy tissues. Practicing these exercises before your treatment, as recommended by Dr. Mathangi, ensures you can perform the breath hold safely and effectively, improving the overall safety and precision of your radiation therapy.

How do lung expansion exercises help with radiation therapy preparation?

Lung expansion exercises are simple practices that help increase your lung capacity and control your breathing. By regularly doing these exercises before your radiation sessions, you prepare your lungs to expand more fully and hold air longer, making it easier to comply with breath hold instructions. Dr. Mathangi guides patients through these techniques to ensure they are ready for the demands of DIBH radiation therapy.

What role does diaphragmatic breathing play in breath hold training radiation?

Diaphragmatic breathing, or "belly breathing," involves using your diaphragm to take deeper, more efficient breaths. This technique is essential for breath hold training radiation, as it allows you to maximize your inhalation and sustain a breath hold comfortably. Dr. Mathangi emphasizes practicing diaphragmatic breathing so patients can develop better breath control and relaxation during therapy.

How often should I practice the 5 simple breathing exercises before my DIBH session?

It's best to practice the recommended breathing exercises at least once or twice daily in the week leading up to your DIBH session. Regular practice helps you build muscle memory and confidence, ensuring you can perform the breath hold correctly during your actual treatment. Dr. Mathangi provides personalized schedules and tips based on your comfort and lung health.

Can these breathing exercises help reduce anxiety before radiation therapy?

Yes, the breathing exercises recommended by Dr. Mathangi not only prepare your lungs physically but also help calm your mind. Controlled breathing activates the parasympathetic nervous system, which can lower stress and anxiety levels. This makes you feel more relaxed and confident during your radiation therapy preparation.

What if I struggle to hold my breath during DIBH radiation therapy?

If you find it difficult to hold your breath, don't worry—this is common at first. Dr. Mathangi works closely with you to assess your breath hold ability and to tailor the DIBH breathing exercises to your needs. With consistent practice and support, most patients are able to improve their breath hold duration and comfort over time.

Are these exercises safe for everyone to do at home?

The 5 simple breathing exercises provided by Dr. Mathangi are generally safe for most people and can be performed at home without supervision. However, if you have any pre-existing lung or heart conditions, it's important to consult with your healthcare provider before starting. Dr. Mathangi customizes exercise plans to suit each patient’s health status and comfort.

How do I know if I'm performing the breathing exercises correctly?

Dr. Mathangi provides detailed instructions and, if needed, demonstration videos to ensure you are practicing each exercise with proper form. You should feel your abdomen rise with diaphragmatic breathing and be able to sustain a comfortable breath hold without strain. If you are unsure, you can discuss your technique during your consultation for further guidance.

Can these breathing exercises improve my overall lung health beyond radiation therapy?

Absolutely. Consistent practice of lung expansion exercises and diaphragmatic breathing can enhance your overall lung capacity, respiratory efficiency, and relaxation even outside of radiation therapy. Many patients find these techniques beneficial for general wellbeing and stress relief long after their treatment.


DIBH vs Free Breathing Radiation: Which is Best for Breast Cancer Care?


Which is better for breast cancer care: DIBH vs free breathing radiation? In breast cancer radiation, up to 90% of early-stage patients can achieve excellent local control, but the risk to the heart and lungs remains a concern—especially for left-sided cancers. With advanced radiation planning and innovative techniques, Dr Mathangi at Gleneagles Cancer Institute offers solutions tailored to maximize cancer cure while protecting vital organs.

What is the difference between DIBH vs free breathing radiation?

Deep inspiration breath hold (DIBH) and free breathing radiotherapy are two major approaches in breast cancer radiation options. DIBH involves the patient holding a deep breath during radiation delivery, expanding the chest and moving the heart away from the breast. In contrast, free breathing radiotherapy delivers radiation while the patient breathes normally.

The core difference is in how each technique manages the movement of the heart and lungs during treatment. DIBH provides superior respiratory motion management, reducing unintended radiation exposure to the heart. This is particularly crucial for left-sided breast cancers, where the proximity of the heart poses a significant risk.

Why is DIBH important in breast cancer radiation options?

DIBH vs free breathing radiation is a vital decision because DIBH can significantly reduce cardiac dose, thereby lowering long-term heart complications after breast cancer treatment.

  • Heart protection: DIBH moves the heart downward and posteriorly, away from the radiation field.
  • Improved lung sparing: By expanding the lungs, DIBH reduces the volume of lung receiving radiation.
  • Enhanced tumor targeting: With reduced organ motion, radiation can be delivered more accurately to the cancerous tissue.

Several studies show that using DIBH can cut the mean heart dose by 50% or more compared to free breathing radiotherapy. This translates to fewer cardiac events and better long-term survival.

How does free breathing radiotherapy compare?

Free breathing radiotherapy is the traditional technique, suitable for patients who cannot tolerate breath-hold or in cases where the heart is not close to the radiation field.

Its advantages include simplicity, comfort, and faster treatment times, but it lacks the nuanced respiratory motion management of DIBH. This can lead to higher incidental doses to the heart and lungs, especially in left-sided breast cancers or when treating the internal mammary lymph nodes.

  • Pros: Easier for patients, requires less training, suitable for right-sided breast cancers or when physical/medical limitations preclude DIBH.
  • Cons: Increased risk of late cardiac and pulmonary toxicity for left-sided cases.

Who benefits most from DIBH vs free breathing radiation?

Patients with left-sided breast cancers, those with pre-existing heart conditions, or those requiring radiation to internal mammary nodes benefit the most from DIBH.

At Gleneagles Cancer Institute, Dr Mathangi uses advanced imaging and simulation to decide which technique is best for each patient. Her personalized approach ensures that breast cancer radiation options are tailored for maximum efficacy with minimum side effects.

What does advanced radiation planning involve?

Advanced radiation planning is a cornerstone of high-precision breast cancer care. It integrates 3D imaging, computerized dose calculations, and motion management to customize treatment for each patient.

  • CT-based simulation in both free breathing and DIBH positions
  • Comparative planning to select the safest and most effective approach
  • Use of technologies like Gated RapidArc, image-guided radiotherapy, and intensity-modulated techniques
  • Ongoing monitoring and plan adaptation if needed

Dr Mathangi’s expertise in advanced radiation planning ensures that each patient’s anatomy and risk factors are considered, enabling optimal respiratory motion management and dose delivery.

What is respiratory motion management in breast cancer radiotherapy?

Respiratory motion management refers to strategies that control or account for chest and organ movement during radiation. This is critical for accuracy, especially when treating cancers close to the heart or lungs.

Techniques include:

  • DIBH (Deep Inspiration Breath Hold) – voluntary breath-hold guided by visual/audio feedback
  • Respiratory gating – radiation is only delivered during specific phases of the breathing cycle
  • Active breathing control devices – mechanical systems to stabilize breathing

Dr Mathangi utilizes state-of-the-art respiratory motion management tools to ensure the safest, most accurate treatment for her patients.

When should you choose DIBH vs free breathing radiation with Dr Mathangi?

The decision between DIBH vs free breathing radiation is individualized, balancing the benefits of heart and lung protection with comfort, convenience, and patient ability.

Comparison: DIBH vs Free Breathing Radiotherapy
Feature DIBH Free Breathing Radiotherapy
Heart Dose Significantly reduced (up to 50%) Higher, especially for left-sided cancers
Lung Dose Reduced Slightly higher
Patient Comfort Requires cooperation, training More comfortable, no special training
Suitability Best for left-sided, high-risk patients Suitable for right-sided or those unable to breath-hold
Treatment Time May be longer Usually shorter

Dr Mathangi’s approach begins with a comprehensive evaluation, simulation in both breathing modes, and a clear explanation of the pros and cons—empowering you to make an informed choice.

What makes Dr Mathangi a leader in breast cancer radiation options?

Dr Mathangi is a Senior Consultant & In-charge of Radiation Oncology at Gleneagles Cancer Institute, Bangalore, with over 20 years of experience in treating complex cancers, including breast cancer.

  • 12,000+ patients successfully treated
  • Expert in advanced techniques: Stereotactic radiotherapy, Gated RapidArc, DIBH gated radiotherapy, and image-guided interstitial brachytherapy
  • Asia Pacific’s first TrueBeam STx Machine installed at her center
  • Director of Fellowship in Advanced Radiotherapy Techniques (RGUHS)
  • Specializes in breast, head and neck, brain, lung, prostate, and women’s cancers

Her training from top international centers in Germany and Denmark ensures the most up-to-date, evidence-based care. At Gleneagles, every patient benefits from a multidisciplinary tumor board review and access to the latest technology.

How to book an appointment with Dr Mathangi?

If you or your loved one is facing a decision regarding breast cancer radiation options, don’t leave your heart and lungs to chance. Experience the advantage of advanced radiation planning and personalized care from South India’s leading oncologist.

  1. Visit https://drmathangi.com/contact/
  2. Submit your contact information using the online form
  3. Dr Mathangi’s expert team will schedule your appointment and notify you promptly

Take the first step towards safer, more effective breast cancer treatment today.

About Dr Mathangi

Dr Mathangi J is a pioneering radiation oncologist based in Bangalore, India, specializing in advanced cancer care at Gleneagles Cancer Institute. With a distinguished record in breast, head and neck, brain, lung, prostate, and women’s cancers, she is recognized for her patient-centric approach and cutting-edge expertise.

For the very best in breast cancer radiation options, trust your care to Dr Mathangi—where compassion meets clinical excellence.

Frequently Asked Questions

What is the main difference between DIBH and free breathing radiation for breast cancer?

DIBH (Deep Inspiration Breath Hold) and free breathing radiation are two respiratory motion management techniques used during breast cancer radiation. DIBH involves patients holding a deep breath during treatment, which increases the distance between the heart and the chest wall, thereby reducing heart and lung exposure to radiation. In contrast, free breathing radiation (or free breathing radiotherapy) delivers radiation while the patient breathes normally. The choice between these depends on individual anatomy, cancer location, and risk factors, all of which Dr. Mathangi considers during advanced radiation planning.

Who is an ideal candidate for DIBH in breast cancer care?

DIBH is especially beneficial for patients with left-sided breast cancer, as it helps to move the heart away from the radiation field, minimizing cardiac risks. However, not all patients can comfortably hold their breath or may not need DIBH if the heart is already well separated from the chest wall. Dr. Mathangi assesses each patient individually to determine if DIBH or free breathing radiotherapy will provide the best protection and treatment outcome.

How does advanced radiation planning impact the choice between DIBH vs free breathing radiation?

Advanced radiation planning involves detailed imaging and simulation to precisely map the tumor and surrounding organs. This allows Dr. Mathangi to compare DIBH vs free breathing radiation for each patient, measuring dose distributions to the heart, lungs, and breast tissue. The technique that best spares healthy organs while ensuring effective cancer control is chosen for optimal patient care.

Are there any risks or downsides with DIBH or free breathing radiotherapy?

Both techniques are safe when properly implemented. DIBH may be challenging for patients who have difficulty holding their breath, and requires training and practice. Free breathing radiotherapy is more convenient but may expose the heart and lungs to higher radiation doses in some patients. Dr. Mathangi's expertise ensures that each patient receives the safest and most effective approach from the available breast cancer radiation options.

What technology does Dr. Mathangi use for respiratory motion management during treatment?

Dr. Mathangi employs state-of-the-art equipment for respiratory motion management, including real-time monitoring systems that track the patient’s breathing cycle and ensure accurate radiation delivery. This technology is essential for both DIBH and free breathing radiotherapy, improving precision and minimizing radiation exposure to healthy tissues.

How does Dr. Mathangi personalize breast cancer radiation options for her patients?

Every patient undergoes a thorough assessment, including advanced imaging, risk evaluation, and simulations. Based on these findings, Dr. Mathangi discusses the merits of DIBH vs free breathing radiation, ensuring that each patient understands their options. The chosen technique is always tailored to maximize effectiveness and minimize side effects, reflecting the latest evidence and best practices.

Can DIBH be combined with other advanced radiation planning techniques?

Yes. DIBH can be integrated with other advanced radiation planning strategies such as IMRT (Intensity-Modulated Radiation Therapy) and VMAT (Volumetric Modulated Arc Therapy) for even greater precision. Dr. Mathangi leverages these technologies to further reduce radiation to healthy organs and improve overall treatment outcomes in breast cancer care.

How can I prepare for a consultation about DIBH vs free breathing radiation with Dr. Mathangi?

Bring your medical history, imaging reports, and any questions you have about breast cancer radiation options. Dr. Mathangi will guide you through the benefits and limitations of each approach, including a demonstration of respiratory motion management techniques, so you can make an informed decision that fits your needs and lifestyle.


Neoadjuvant vs Adjuvant Radiation Therapy for Rectal Cancer: Staging Frameworks and Treatment Decisions

Why Is Accurate Staging Essential In Rectal Cancer Radiation Therapy?

Rectal cancer radiation therapy forms a cornerstone in the multidisciplinary management of rectal cancer, contributing significantly to improved local control, sphincter preservation, and overall survival. According to the World Health Organization, colorectal cancer ranks as the third most common cancer worldwide, with rectal cancer accounting for a large proportion of these cases. In India, the incidence is steadily rising, making timely access to expert-driven, evidence-based care crucial.

Accurate staging is the linchpin for tailoring treatment—determining the sequence and modality of radiation therapy. Pelvic MRI staging is now the global gold standard, offering unparalleled detail in assessing tumor depth, lymph node involvement, and relationship to critical anatomical structures such as the circumferential resection margin (CRM). These insights directly influence whether a patient is best suited for neoadjuvant (preoperative) or adjuvant (postoperative) radiation therapy, and whether advanced surgical approaches like total mesorectal excision can be safely performed.

How Do Staging Frameworks Guide Treatment Decisions In Rectal Cancer?

Staging frameworks integrate clinical, radiological, and pathological data to stratify patients into optimal treatment pathways. The TNM system—emphasizing Tumor (T), Node (N), and Metastasis (M)—remains the foundation, but modern practice employs MRI-based subcategories:

The proximity of the tumor to the circumferential resection margin is meticulously evaluated. CRM clearance—defined as a margin of at least 1mm between tumor and mesorectal fascia—is a critical predictor of local recurrence. Tumors threatening or involving the CRM generally necessitate neoadjuvant therapy for downsizing and better surgical outcomes.

What Is Neoadjuvant (Preoperative) Radiation Therapy?

Neoadjuvant radiation therapy—administered before surgical intervention—aims to shrink the tumor, facilitate resection, and reduce recurrence risk. There are two main approaches:

Indications for neoadjuvant therapy typically include cT3 rectal cancer, cT4 rectal cancer, node-positive disease, and tumors close to the mesorectal fascia or anal sphincter.

The primary benefits of neoadjuvant therapy are:

Preoperative radiotherapy for rectal cancer is now the standard of care for locally advanced cases, as endorsed by leading international guidelines and substantiated by robust clinical trial evidence.

When Is Adjuvant (Postoperative) Radiation Therapy Indicated?

Adjuvant radiation therapy is considered when high-risk pathological features are discovered after surgery. These may include positive margins, extensive nodal involvement, or upstaged disease not identified during initial staging. However, the trend is to minimize adjuvant therapy in favor of preoperative approaches, as postoperative radiation is associated with higher rates of toxicity and lower efficacy in reducing local recurrence.

In scenarios where neoadjuvant therapy was not feasible or if unexpected adverse features are found postoperatively, adjuvant therapy remains a vital tool in the oncologist’s armamentarium.

Comparing Neoadjuvant And Adjuvant Radiation Therapy: Which Is Superior?

Which is better: neoadjuvant or adjuvant radiation therapy for rectal cancer?
Neoadjuvant radiation therapy is generally preferred for locally advanced rectal cancer due to superior local control, increased sphincter preservation, and lower toxicity, as confirmed by multiple randomized trials and guidelines.
Aspect Neoadjuvant Radiation Therapy Adjuvant Radiation Therapy
Timing Before surgery After surgery
Tumor Downstaging Yes (significant) No
Sphincter Preservation Higher rates Lower rates
Toxicity Lower Higher
CRM Clearance Improved Variable
Guideline Recommendation Preferred for locally advanced disease For select high-risk cases only

How Does Dr Mathangi Individualize Treatment Planning For Rectal Cancer?

At Gleneagles Cancer Institute, Dr Mathangi leverages her advanced training and extensive experience to deliver personalized, evidence-driven care. She combines:

Dr Mathangi’s approach ensures every patient receives a treatment plan tailored to their cancer stage, anatomical considerations, and personal preferences—maximizing survival and minimizing side effects.

What Are The Steps Involved In Preoperative Radiotherapy For Rectal Cancer?

  1. Comprehensive Assessment: Clinical evaluation, colonoscopy, and pelvic MRI staging
  2. Tumor Board Review: Multidisciplinary discussion for consensus on the best treatment sequence
  3. Preoperative Radiotherapy: Choice of preoperative short course radiation or long-course chemoradiation based on tumor stage and location
  4. Interval To Surgery: Surgery (usually total mesorectal excision) is timed post-radiation for optimal downstaging
  5. Pathological Review: Assessment of CRM clearance and nodal status to determine if further therapy is needed

Why Is CRM Clearance Crucial For Long-Term Outcomes?

CRM clearance is a major determinant of local recurrence and survival in rectal cancer. Failure to achieve an adequate margin (<1mm) is associated with a significantly higher risk of cancer returning in the pelvis. Neoadjuvant therapy, by shrinking tumors away from the fascia, increases the likelihood of achieving a negative CRM and thus long-term cure.

Which Cancers Benefit From Radiation Therapy According To Dr Mathangi?

If you or a loved one is facing a diagnosis of rectal or any of the above cancers, timely expert intervention can change the trajectory of your care and outcomes.

Ready To Take The Next Step?
Entrust your care to Dr Mathangi, whose expertise, advanced technology, and compassionate approach ensure you receive the best possible outcome.
Book your appointment here and join the thousands of patients who have benefited from her exceptional care at Gleneagles Cancer Institute, Bangalore. Her team will promptly schedule your consultation and notify you with all necessary details.

About Dr Mathangi: A Leader In Oncology

Dr Mathangi J is a highly respected senior radiation oncologist, educator, and innovator in cancer care across South and North India. Her academic credentials, clinical experience, and pioneering achievements—including the installation of Asia Pacific’s first TrueBeam STx Machine—set her apart as a top choice for patients seeking state-of-the-art, personalized oncological care.

Her holistic, patient-focused philosophy is reflected in her leadership at Gleneagles Cancer Institute and her role as Director of Fellowship in Advanced Radiotherapy Techniques. When you choose Dr Mathangi, you are opting for the gold standard in cancer management.

Frequently Asked Questions

What is the difference between neoadjuvant and adjuvant radiation therapy for rectal cancer?

Neoadjuvant radiation therapy is given before surgery, while adjuvant therapy is delivered after surgery. For rectal cancer radiation therapy, neoadjuvant (preoperative) approaches are often preferred because they can shrink the tumor, improve surgical outcomes, and reduce the risk of local recurrence. Dr. Mathangi emphasizes that the decision is based on tumor stage, imaging findings, and patient-specific factors.

How does pelvic MRI staging influence treatment planning in rectal cancer?

Pelvic MRI staging is crucial for accurately determining the tumor's local extent, involvement of surrounding structures, and the status of the circumferential resection margin (CRM). Dr. Mathangi utilizes pelvic MRI staging to guide whether preoperative radiotherapy for rectal cancer is indicated, and to tailor the surgical and radiation approach to maximize outcomes and minimize unnecessary treatment.

When is preoperative short course radiation used in rectal cancer treatment?

Preoperative short course radiation is typically used for resectable rectal tumors at intermediate risk, such as mid or low cT3 rectal cancer without threatened CRM. Dr. Mathangi explains that this approach offers effective tumor downstaging, can be completed quickly (usually within one week), and is followed by timely surgery, making it ideal for selected patients.

What is the significance of CRM clearance in rectal cancer surgery?

CRM (circumferential resection margin) clearance means that no tumor is found close to the outer edge of the tissue removed during total mesorectal excision. Achieving CRM clearance is vital because it reduces the risk of local recurrence. Dr. Mathangi uses advanced imaging and preoperative radiotherapy for rectal cancer to help secure CRM clearance, especially in borderline cases.

How does Dr. Mathangi approach sphincter preservation in rectal cancer?

Sphincter preservation rectal cancer strategies focus on avoiding permanent colostomy when possible. Dr. Mathangi integrates neoadjuvant therapies, detailed pelvic MRI staging, and precise surgical planning to shrink tumors and allow for sphincter-saving surgery, always prioritizing patient quality of life and oncological safety.

What are the differences in treatment for cT3 and cT4 rectal cancer?

cT3 rectal cancer indicates tumor invasion through the muscularis propria but not into nearby organs, while cT4 rectal cancer invades adjacent organs or structures. Dr. Mathangi tailors the treatment: cT3 cases may be managed with short or long course preoperative radiation, while cT4 cases often require long course chemoradiation and multidisciplinary planning to optimize surgical resection and maximize CRM clearance.

Why is total mesorectal excision important in rectal cancer management?

Total mesorectal excision (TME) is a surgical technique that removes the rectum along with the surrounding mesorectal fat and lymph nodes. This method is the gold standard for rectal cancer surgery, as it improves local control and reduces recurrence. Dr. Mathangi ensures TME is combined with the most appropriate neoadjuvant or adjuvant therapy based on the patient's staging and risk profile.

How does Dr. Mathangi decide between neoadjuvant and adjuvant therapy for individual patients?

Dr. Mathangi utilizes a comprehensive assessment—combining clinical examination, pelvic MRI staging, and multidisciplinary input—to determine if a patient would benefit more from neoadjuvant or adjuvant therapy. The goal is to maximize local control, facilitate sphincter preservation rectal cancer options, and minimize toxicity, always individualizing care for the best outcomes.

What are the main goals of rectal cancer radiation therapy?

The main goals of rectal cancer radiation therapy are to reduce tumor size (downstaging), improve surgical success, achieve CRM clearance, lower recurrence risks, and preserve sphincter function when possible. Dr. Mathangi offers advanced protocols and multidisciplinary collaboration to achieve these objectives, ensuring patient-centric, evidence-based care.


ctDNA Clearance After Radiation Therapy: What Cancer Patients Should Know

Recent studies have shown that circulating tumor DNA (ctDNA) can often be detected months before conventional imaging identifies recurrence in certain cancers, making it one of the most promising developments in modern oncology. Understanding ctDNA clearance after radiation therapy is becoming increasingly important because it may provide valuable insights into whether treatment is working, how effectively tumors are responding, and whether additional intervention may be required. For cancer patients and families navigating a complex treatment journey, this emerging technology offers a new layer of information that can complement traditional scans and clinical evaluations.

When facing cancer, one of the most pressing concerns is whether the treatment is truly eliminating cancer cells. Radiation therapy remains one of the most effective treatment modalities for a wide range of cancers, including head and neck cancers, brain tumors, spine tumors, esophageal cancers, rectal cancers, lung cancers, liver cancers, breast cancers, bladder cancers, prostate cancers, uterine cancers, cervical cancer, vulval cancers, anal canal cancers, and penile cancers. However, patients often find themselves waiting anxiously for imaging results. Advances in molecular diagnostics are changing that reality by offering additional tools that help physicians understand treatment effectiveness more precisely.

What is ctDNA and why is it important after radiation therapy?

ctDNA refers to small fragments of genetic material shed by cancer cells into the bloodstream. These fragments can be detected through specialized blood tests and may provide real-time information about tumor activity.

Unlike traditional biopsies that require tissue sampling, ctDNA testing is minimally invasive. Cancer cells continuously release fragments of DNA into circulation. By analyzing these fragments, oncologists can gain insight into tumor burden, treatment effectiveness, and potential recurrence risks.

The growing importance of ctDNA lies in its ability to function as one of the emerging oncology biomarkers that help physicians personalize treatment decisions. Instead of relying solely on scans that may take weeks or months to show changes, ctDNA testing can sometimes reveal molecular responses earlier.

What does ctDNA clearance after radiation therapy mean?

In simple terms, ctDNA clearance after radiation therapy refers to the disappearance or significant reduction of detectable tumor DNA from the bloodstream following treatment.

When radiation therapy successfully destroys cancer cells, fewer malignant cells remain available to shed DNA into circulation. As a result, ctDNA levels may decrease substantially or become undetectable. This reduction can potentially serve as one of the important radiation success indicators being studied by researchers worldwide.

However, it is essential to understand that ctDNA testing is not a standalone diagnostic tool. Results must always be interpreted alongside imaging studies, pathology reports, clinical examinations, and the patient's overall medical condition.

How does ctDNA help evaluate cancer treatment response?

A decrease in ctDNA levels after treatment may indicate that cancer cells are responding to therapy. Persistently elevated levels may suggest residual disease that requires closer observation.

Assessing cancer treatment response has traditionally depended on imaging modalities such as CT scans, MRI scans, and PET scans. While these technologies remain essential, molecular monitoring introduces a complementary layer of precision.

  • Provides earlier indications of treatment effectiveness.
  • May help identify residual disease.
  • Can support personalized follow-up strategies.
  • May assist in predicting recurrence risk.
  • Offers a minimally invasive monitoring option.

For many patients, this additional information can help reduce uncertainty and facilitate more informed discussions with their oncology team.

Why is liquid biopsy monitoring gaining attention in oncology?

Liquid biopsies allow physicians to evaluate tumor-related genetic material through blood samples rather than invasive tissue procedures.

liquid biopsy monitoring is transforming cancer care because it can be repeated multiple times throughout treatment and follow-up. Traditional tissue biopsies often provide information from a single point in time, whereas liquid biopsies can help track disease evolution continuously.

This approach is especially valuable in situations where obtaining tissue samples may be difficult or risky. Ongoing monitoring can reveal changes in tumor biology and help clinicians understand how cancer responds over time.

What factors influence ctDNA clearance after radiation therapy?

Several variables affect whether ctDNA becomes undetectable after radiation treatment.

Factor Potential Impact
Tumor Type Different cancers release varying amounts of ctDNA.
Tumor Burden Larger tumors may generate higher ctDNA levels.
Radiation Dose Treatment intensity may influence response.
Combined Therapies Chemotherapy or immunotherapy may affect clearance.
Patient Biology Individual metabolic and immune factors play a role.

Because every patient is unique, ctDNA trends should always be interpreted by experienced oncology specialists who understand the broader clinical context.

Which cancers may benefit most from ctDNA-based monitoring?

Research continues to expand, but promising applications have been identified across multiple cancer types.

Dr. Mathangi frequently manages cancers where advanced treatment assessment and follow-up strategies are critically important, including:

  • Head and neck cancers
  • Brain tumors
  • Spine tumors
  • Lung cancers
  • Breast cancers
  • Prostate cancers
  • Cervical cancer
  • Uterine cancers
  • Liver cancers
  • Bladder cancers
  • Anal canal cancers
  • Esophageal cancers
  • Rectal cancers

As research progresses, ctDNA assessment may become increasingly integrated into individualized cancer management plans for many of these conditions.

How does advanced radiation therapy contribute to molecular response?

Modern radiation techniques are designed to maximize tumor control while minimizing damage to surrounding healthy tissues.

Dr. Mathangi brings more than two decades of expertise in advanced radiation oncology and has successfully treated over 12,000 patients. Her specialized training includes stereotactic radiosurgery (SRS), stereotactic body radiotherapy (SBRT), IGRT, RapidArc, DIBH-gated radiotherapy, and image-guided brachytherapy.

These sophisticated technologies enable highly accurate radiation delivery. Improved targeting may contribute to better local tumor control, which can ultimately influence biological outcomes observed through ctDNA testing and other molecular assessments.

Can ctDNA replace scans after radiation therapy?

No. ctDNA testing complements imaging rather than replacing it.

While ctDNA provides valuable molecular information, imaging remains essential for visualizing anatomical changes, evaluating treatment-related effects, and identifying structural abnormalities. The most effective cancer management strategies often integrate:

  1. Clinical examination
  2. Imaging studies
  3. Pathology findings
  4. Molecular testing
  5. Patient symptoms and quality-of-life assessments

Combining these data points creates a comprehensive picture of treatment effectiveness and future care requirements.

Why should patients discuss ctDNA monitoring with an experienced radiation oncologist?

Interpreting ctDNA results requires specialized expertise because molecular findings must be correlated with treatment plans, imaging studies, and disease-specific characteristics.

A result showing persistent ctDNA does not automatically mean treatment failure. Similarly, ctDNA clearance alone does not guarantee permanent remission. Expert interpretation is crucial to avoid unnecessary anxiety or false reassurance.

This is where the experience of a seasoned radiation oncologist becomes particularly valuable. Patients who work with specialists deeply involved in modern radiation techniques and evidence-based cancer care gain access to comprehensive treatment planning and informed guidance regarding emerging technologies.

What should patients do if they are considering advanced radiation therapy?

Patients should seek consultation with an experienced radiation oncologist who can evaluate their diagnosis, stage, treatment goals, and available technologies.

The field of radiation oncology continues to evolve rapidly. New insights into oncology biomarkers, molecular diagnostics, and treatment personalization are reshaping how cancer care is delivered. Missing opportunities to benefit from these advancements may mean missing valuable information that could influence treatment decisions and long-term outcomes.

For individuals diagnosed with cancers requiring radiation therapy, consulting an expert who remains actively engaged with modern treatment innovations can make a meaningful difference in care quality and confidence throughout the treatment journey.

About Dr. Mathangi

Dr. Mathangi J is a Senior Consultant and In-charge of Radiation Oncology with more than 20 years of experience in cancer care. Based in Bengaluru, she leads advanced radiation oncology services and is recognized for expertise in stereotactic radiotherapy, IGRT, RapidArc, DIBH-gated radiotherapy, and image-guided brachytherapy.

She has successfully treated over 12,000 patients and serves as Director of Fellowship in Advanced Radiotherapy Techniques affiliated with RGUHS. Her extensive international training and leadership in implementing advanced radiation technologies have positioned her among the respected specialists in the field of radiation oncology.

Patients seeking expert guidance regarding radiation therapy, treatment planning, follow-up strategies, and emerging advances such as ctDNA assessment can request an appointment through the contact form at https://drmathangi.com/contact/. Once the information is submitted, Dr. Mathangi's team will schedule the appointment and provide further details.

Key takeaways

  • ctDNA clearance after radiation therapy may indicate a favorable molecular response.
  • ctDNA testing is an emerging tool for assessing cancer treatment response.
  • Researchers continue evaluating ctDNA as one of the promising radiation success indicators.
  • liquid biopsy monitoring provides a minimally invasive method for tracking disease activity.
  • Modern oncology biomarkers are helping personalize cancer treatment and follow-up strategies.
  • Expert interpretation by an experienced radiation oncologist remains essential.

Frequently Asked Questions

What does ctDNA clearance after radiation therapy mean?

ctDNA clearance after radiation therapy refers to the reduction or disappearance of circulating tumor DNA (ctDNA) from a patient's bloodstream following radiation treatment. Tumor cells release tiny fragments of genetic material into the blood, and advanced testing can detect these fragments through a blood sample.

When ctDNA levels decline significantly or become undetectable, it may suggest that radiation therapy has successfully destroyed a substantial number of cancer cells. However, ctDNA results should always be interpreted alongside imaging studies, clinical examinations, pathology findings, and the overall treatment plan.

Dr. Mathangi carefully evaluates ctDNA trends together with other diagnostic information to develop a comprehensive understanding of each patient's progress and ongoing care needs.

Why is ctDNA testing becoming important in modern cancer care?

ctDNA testing offers a minimally invasive way to monitor cancer activity through a simple blood draw. Unlike some traditional methods that may require tissue sampling, ctDNA analysis can often be repeated over time to track changes during and after treatment.

This approach has become valuable because it may provide earlier insights into disease response, residual cancer cells, or potential recurrence. Many specialists now consider ctDNA among the most promising oncology biomarkers being studied for personalized cancer management.

Dr. Mathangi integrates evidence-based molecular assessment strategies when appropriate, helping patients understand how emerging technologies may complement established cancer treatments.

Can ctDNA levels help measure cancer treatment response?

Yes. Changes in ctDNA levels may provide useful information about cancer treatment response. Falling ctDNA levels often indicate that treatment is reducing tumor burden, while stable or rising levels may prompt further evaluation.

It is important to remember that no single test should be used in isolation. Factors such as cancer type, stage, treatment timing, and individual biological differences can influence results. Physicians typically combine ctDNA findings with scans, laboratory investigations, and clinical assessments before making treatment decisions.

Dr. Mathangi emphasizes a personalized interpretation of all available data to ensure that treatment recommendations are accurate and tailored to each patient's situation.

Are ctDNA results considered reliable radiation success indicators?

ctDNA trends are increasingly being investigated as radiation success indicators, particularly when monitored over time. A substantial decline or complete clearance of ctDNA after radiation may suggest that treatment has been effective against the targeted cancer cells.

Nevertheless, radiation outcomes are still assessed through multiple methods, including imaging scans, symptom evaluation, physical examination, and laboratory findings. ctDNA should be viewed as one valuable piece of the overall clinical picture rather than a standalone answer.

Dr. Mathangi helps patients understand the strengths and limitations of ctDNA testing so that expectations remain realistic and medically appropriate.

What is the role of liquid biopsy monitoring after radiation therapy?

liquid biopsy monitoring allows physicians to evaluate cancer-related genetic material in blood samples without requiring invasive procedures. Following radiation therapy, periodic testing may help track molecular changes that occur as the body responds to treatment.

In some situations, liquid biopsy monitoring may identify molecular evidence of response or recurrence before changes become visible on imaging studies. This can support more informed discussions regarding follow-up schedules and future treatment strategies.

Dr. Mathangi stays informed about evolving advances in molecular oncology and advises patients on whether such monitoring approaches may be relevant to their specific diagnosis.

Does undetectable ctDNA mean the cancer is completely cured?

Not necessarily. While undetectable ctDNA is generally an encouraging sign, it does not automatically guarantee that every cancer cell has been eliminated. Current testing technologies have detection limits, and some microscopic disease may remain below measurable thresholds.

For this reason, patients should continue recommended follow-up visits, imaging studies, and surveillance testing even when ctDNA results appear favorable. Long-term monitoring remains an essential component of cancer care.

Dr. Mathangi provides ongoing surveillance plans designed to balance reassurance with appropriate medical vigilance.

Who may benefit most from ctDNA testing after radiation treatment?

The usefulness of ctDNA testing depends on the type of cancer, stage of disease, treatment goals, and availability of validated testing methods. Certain cancers have stronger evidence supporting ctDNA assessment than others.

Patients undergoing radiation therapy for cancers where molecular monitoring has demonstrated clinical value may benefit from discussions about incorporating ctDNA into their follow-up strategy. The decision should always be individualized.

Dr. Mathangi evaluates each patient's diagnosis, treatment history, and clinical objectives before recommending advanced molecular testing approaches.

How does Dr. Mathangi support patients in understanding ctDNA results?

Cancer patients often receive complex reports containing genetic and molecular information that can be difficult to interpret. Dr. Mathangi takes a patient-centered approach by explaining what ctDNA findings mean, how they relate to treatment outcomes, and whether any additional testing or monitoring is warranted.

By combining clinical expertise, evidence-based oncology practices, imaging review, and molecular insights, Dr. Mathangi helps patients make informed decisions regarding follow-up care, surveillance, and future treatment planning.

This comprehensive approach ensures that advanced oncology biomarkers are used thoughtfully and in context with the patient's complete medical picture.


Liquid Biopsy for Hard-to-Biopsy Tumors: Modern Cancer Monitoring Solutions

Liquid biopsy for hard-to-biopsy tumors is emerging as one of the most important breakthroughs in modern oncology because it allows cancer-related genetic material to be detected through a simple blood sample rather than relying solely on invasive tissue procedures. According to research published in leading oncology journals, liquid biopsy technologies are increasingly being integrated into precision cancer care due to their ability to identify tumor DNA, monitor treatment response, and detect disease progression in real time. For patients facing difficult-to-access cancers, this advancement can provide critical insights when traditional biopsies are challenging, risky, or impractical.

For many patients and families, one of the greatest challenges in cancer care is uncertainty. Questions such as whether treatment is working, whether the cancer has changed genetically, or whether recurrence is occurring can create significant anxiety. Modern oncology now offers new pathways to obtain these answers. Under the leadership of Dr Mathangi J, Senior Consultant and In-charge of Radiation Oncology at Gleneagles Cancer Institute, Bangalore, patients gain access to evidence-based cancer management strategies that combine clinical expertise, advanced radiotherapy, and the latest developments in precision oncology.

What is liquid biopsy and why is it important?

Liquid biopsy is a minimally invasive diagnostic technique that analyzes cancer-related biomarkers found in blood or other body fluids. Unlike conventional biopsies that require tissue removal, liquid biopsy identifies circulating tumor DNA (ctDNA), circulating tumor cells, and other molecular markers that may provide valuable information about cancer behavior.

The significance of liquid biopsy extends beyond convenience. In many cancers, obtaining tissue samples repeatedly can be difficult, painful, expensive, or medically risky. Certain tumors are located in sensitive anatomical regions where traditional biopsy procedures carry additional complications. This is where liquid biopsy becomes a valuable complement to conventional cancer assessment.

Benefits may include:

  • Reduced invasiveness
  • Faster access to molecular information
  • Improved patient comfort
  • Potential for repeated monitoring over time
  • Enhanced treatment personalization
  • Earlier detection of disease changes

Why are some tumors difficult to biopsy?

Hard-to-biopsy tumors are cancers located in areas where tissue collection may be technically challenging, medically risky, or limited by patient-specific factors.

Examples include tumors involving:

  • Deep brain structures
  • Certain lung locations
  • Spinal regions
  • Complex head and neck areas
  • Metastatic sites that are difficult to access safely

In such situations, obtaining sufficient tissue may require highly specialized procedures. Even when a tissue biopsy is successfully performed, repeating the procedure multiple times during treatment may not always be practical. Consequently, clinicians often explore tumor monitoring alternatives that can provide additional information while minimizing patient burden.

How does liquid biopsy support cancer monitoring?

Liquid biopsy supports ongoing cancer monitoring by helping clinicians track molecular changes occurring within the tumor over time.

Cancer is not static. Tumors evolve, adapt, and may develop resistance to therapies. A treatment that initially works well can become less effective as cancer cells acquire new genetic alterations.

Through serial testing, liquid biopsy may help:

  • Monitor treatment effectiveness
  • Identify emerging mutations
  • Detect molecular evidence of progression
  • Support precision medicine decisions
  • Evaluate disease dynamics during follow-up

While tissue biopsy remains the gold standard in many circumstances, liquid biopsy has become an increasingly valuable addition to comprehensive cancer management strategies.

Which cancers may benefit from advanced monitoring approaches?

Several cancer types may benefit from advanced molecular monitoring, particularly when precision treatment decisions are required.

Dr Mathangi specializes in the treatment and management of multiple cancers that frequently require sophisticated evaluation and monitoring approaches, including:

  • Head and neck cancers
  • Brain tumors
  • Spine tumors
  • Esophageal cancers
  • Rectal cancers
  • Lung cancers
  • Liver cancers
  • Breast cancers
  • Bladder cancers
  • Prostate cancers
  • Uterine cancers
  • Cervical cancer
  • Vulval cancers
  • Anal canal cancers
  • Penile cancers

For many of these conditions, ongoing surveillance plays a critical role in determining whether treatment objectives are being achieved and whether additional interventions may be necessary.

How is cancer diagnostics innovation transforming oncology?

Cancer diagnostics innovation is fundamentally changing how clinicians detect, characterize, and monitor cancer.

Historically, oncologists relied heavily on imaging studies, tissue biopsies, and clinical examinations. While these remain essential tools, molecular technologies are now adding an entirely new dimension to patient care.

Recent innovations include:

Innovation Potential Clinical Value
Liquid Biopsy Molecular monitoring through blood samples
Genomic Profiling Identification of actionable mutations
Precision Oncology Individualized treatment planning
Artificial Intelligence Enhanced imaging analysis
Advanced Radiotherapy Highly targeted cancer treatment

As a recognized leader in advanced radiotherapy and precision cancer care, Dr Mathangi continuously incorporates evidence-based developments that improve treatment accuracy and patient outcomes.

What role does precision radiation oncology play alongside liquid biopsy?

Liquid biopsy and advanced radiation oncology often work together to create a more comprehensive cancer management strategy.

Dr Mathangi is widely recognized for her expertise in sophisticated radiotherapy technologies, including:

  • Stereotactic Ablative Body Radiotherapy (SBRT)
  • Stereotactic Radiosurgery (SRS)
  • Image Guided Radiation Therapy (IGRT)
  • RapidArc Technology
  • Gated Radiotherapy
  • DIBH Gated Radiotherapy
  • Image-Guided Interstitial Brachytherapy
  • Intraoperative Radiotherapy (IORT)

These technologies allow radiation delivery with exceptional precision, helping protect surrounding healthy tissues while maximizing treatment effectiveness.

When combined with molecular insights derived from modern diagnostic techniques, clinicians gain a more complete understanding of disease behavior and treatment response.

Why do patients seek advanced oncology solutions?

Patients increasingly seek advanced oncology solutions because they want personalized care, accurate monitoring, and access to modern treatment technologies.

The emotional burden of cancer extends far beyond the diagnosis itself. Patients often worry about:

  • Whether treatment is working
  • Potential recurrence
  • Treatment side effects
  • Long-term outcomes
  • Future quality of life

Modern oncology aims to reduce this uncertainty through data-driven decision-making. By integrating advanced imaging, molecular diagnostics, precision radiotherapy, and multidisciplinary expertise, patients can receive care that is tailored to their unique disease characteristics.

This approach reflects the growing demand for advanced oncology solutions that move beyond one-size-fits-all treatment models.

Why choose Dr Mathangi for comprehensive cancer care?

Experience, technology, and clinical leadership are among the key factors patients consider when choosing an oncologist.

Dr Mathangi brings more than two decades of oncology experience and has successfully treated over 12,000 patients. Her extensive training includes international exposure to advanced radiation oncology techniques in Germany and Denmark.

Notable professional achievements include:

  • Senior Consultant and In-charge of Radiation Oncology
  • Director of Fellowship in Advanced Radiotherapy Techniques
  • Installation of the Asia Pacific region's first TrueBeam STx machine
  • Specialized expertise in complex cancer management
  • Leadership in precision radiotherapy implementation

For patients seeking expert guidance, her combination of clinical experience and technological expertise provides reassurance during one of life's most challenging journeys.

What should patients know about modern cancer monitoring?

Modern cancer monitoring increasingly combines imaging, clinical evaluation, pathology, molecular testing, and multidisciplinary review.

The future of oncology is moving toward earlier detection, more personalized treatment pathways, and continuous monitoring of disease biology. Technologies such as liquid biopsy are helping clinicians gain valuable insights that were difficult to obtain just a decade ago.

For patients with challenging cancers, staying informed about emerging options can be an important part of achieving the best possible outcomes. Early evaluation by an experienced oncology specialist helps determine which diagnostic and treatment strategies may be appropriate based on individual circumstances.

About Dr Mathangi

Dr Mathangi J is a leading Radiation Oncologist based in Bangalore and serves as Senior Consultant and In-charge of Radiation Oncology at Gleneagles Cancer Institute. She holds MBBS, DMRT, and DNB qualifications and has dedicated more than 20 years to advancing cancer treatment. Her areas of expertise include head and neck cancers, brain tumors, lung cancers, prostate cancers, breast cancers, cervical cancers, uterine cancers, and several other complex malignancies.

Known for her commitment to precision oncology, patient-centered care, and advanced radiotherapy technologies, Dr Mathangi continues to help patients access world-class cancer treatment strategies. Patients wishing to consult with Dr Mathangi may submit their details through the contact form at https://drmathangi.com/contact/, after which her team will coordinate scheduling and appointment confirmation.

Frequently Asked Questions

What is a liquid biopsy and how does it help with difficult cancer cases?

A liquid biopsy is a minimally invasive test that analyzes cancer-related material, such as circulating tumor DNA (ctDNA), from a blood sample. It can provide valuable information about tumor behavior, genetic mutations, treatment response, and disease progression without requiring a traditional tissue biopsy.

For patients who have tumors located in difficult or high-risk anatomical areas, a liquid biopsy for hard-to-biopsy tumors can offer an important diagnostic and monitoring option. Dr. Mathangi evaluates each patient's clinical situation to determine whether liquid biopsy testing may complement existing imaging, pathology, and treatment strategies.

Which tumors are considered hard to biopsy?

Tumors located deep within the body or near critical organs may be challenging to access safely through conventional biopsy procedures. Examples can include certain lung lesions, brain tumors, bone tumors, pancreatic cancers, and metastatic lesions in sensitive locations.

In these situations, physicians may explore additional tumor monitoring alternatives that reduce procedural risks while still providing clinically meaningful molecular information. Dr. Mathangi helps patients understand the benefits and limitations of each available approach.

Can a liquid biopsy replace a traditional tissue biopsy?

Not always. Tissue biopsy remains the gold standard in many cancer diagnoses because it provides direct examination of tumor cells and surrounding tissue architecture.

However, liquid biopsy can be extremely useful when tissue sampling is difficult, risky, or insufficient. In many cases, it serves as a complementary tool that enhances clinical decision-making. Dr. Mathangi develops individualized diagnostic pathways that combine the most appropriate tests for each patient's condition.

How does liquid biopsy help monitor cancer treatment?

Liquid biopsy can detect molecular changes in circulating tumor DNA over time. This allows oncologists to evaluate how well a treatment is working, identify emerging resistance mutations, and monitor disease progression with greater precision.

Regular monitoring may help guide treatment adjustments before significant changes become visible on imaging studies. Dr. Mathangi incorporates evidence-based monitoring strategies to support timely and informed treatment decisions whenever appropriate.

What role does liquid biopsy play in personalized cancer care?

Personalized oncology relies on understanding the unique molecular profile of a patient's cancer. Liquid biopsy can identify specific genetic alterations that may influence treatment selection, targeted therapy eligibility, or participation in clinical trials.

As part of ongoing cancer diagnostics innovation, these technologies are helping oncologists obtain actionable insights with less burden on patients. Dr. Mathangi focuses on integrating molecular diagnostics with comprehensive clinical evaluation to create individualized treatment plans.

Is liquid biopsy useful for detecting cancer recurrence?

In selected clinical situations, liquid biopsy may help identify molecular evidence of disease recurrence before symptoms develop or before changes become apparent on imaging studies.

While it is not a substitute for comprehensive follow-up care, it can provide an additional layer of surveillance that supports more proactive cancer management. Dr. Mathangi carefully assesses whether such testing may be beneficial based on cancer type, treatment history, and overall clinical goals.

Are liquid biopsy tests safe and convenient for patients?

Because liquid biopsy generally requires only a blood sample, it is considered far less invasive than many surgical or needle-based biopsy procedures. This often results in reduced discomfort, lower procedural risk, and faster recovery for patients.

The simplicity of sample collection can also make repeated testing more feasible when ongoing molecular monitoring is required during treatment.

How does Dr. Mathangi use advanced oncology solutions for cancer monitoring?

Dr. Mathangi takes a multidisciplinary approach that combines clinical expertise, modern molecular testing, imaging studies, pathology review, and patient-centered treatment planning. When appropriate, advanced oncology solutions such as liquid biopsy may be incorporated to improve diagnostic clarity and support ongoing disease monitoring.

The goal is to provide patients with access to contemporary cancer care strategies that are tailored to their individual needs, helping them make informed decisions throughout their treatment journey.


High-Risk Cancer Surveillance Using Sequential ctDNA Monitoring

What is high-risk cancer surveillance and how does sequential ctDNA analysis transform early detection? High-risk cancer surveillance refers to the proactive and systematic monitoring of individuals at greater risk of cancer recurrence or progression. Sequential ctDNA analysis—tracking circulating tumor DNA through blood samples over time—offers a minimally invasive, highly sensitive method to detect cancer recurrence earlier than conventional imaging or biomarkers. This advanced approach is revolutionizing cancer monitoring strategies, enabling oncologists like Dr Mathangi at Gleneagles Cancer Institute, Bangalore, to make timely, life-saving interventions and deliver truly personalized care.

According to recent studies, up to 40% of cancer recurrences are now detected earlier with sequential ctDNA monitoring compared to traditional surveillance methods. Early detection through high-risk cancer surveillance not only improves survival rates but also significantly enhances quality of life for patients. However, many patients and families remain unaware of these transformative advances—potentially missing out on critical opportunities for early intervention.

Why is high-risk cancer surveillance essential in modern oncology?

High-risk cancer surveillance is a cornerstone in modern oncology because it enables clinicians to:

  • Identify relapse or metastasis long before symptoms or imaging changes become apparent
  • Tailor treatment plans proactively, often leading to less aggressive therapies and better outcomes
  • Reduce patient anxiety by providing ongoing reassurance and evidence-based follow-up
  • Improve survival rates by catching recurrence during its most treatable phase

For patients with cancers that are prone to recurrence—such as head and neck cancers, brain tumors, spine tumors, esophagus and rectal cancers, lung cancers, liver cancers, breast cancers, bladder cancers, prostate cancers, uterine cancers, cervical cancer, vulval cancers, anal canal cancers, and penile cancers—high-risk cancer surveillance is not just an option, but a necessity. Dr Mathangi, with her extensive expertise and leadership at Gleneagles Cancer Institute, is at the forefront of integrating these advanced surveillance protocols into routine oncology care in Bangalore and across India.

How does sequential ctDNA analysis work in cancer monitoring?

Sequential ctDNA analysis involves the regular collection and evaluation of blood samples to detect circulating tumor DNA—a reliable marker of cancer activity. By comparing ctDNA levels over time, oncologists can:

  1. Detect the presence of minimal residual disease (MRD) post-treatment
  2. Monitor for emerging resistance mutations
  3. Track tumor dynamics at a molecular level
  4. Guide decisions on adjuvant therapy, salvage treatment, or de-escalation of care

This method, when incorporated into high-risk cancer surveillance, provides a dynamic and individualized map of cancer behavior in real time. It is especially valuable in guiding MRD follow-up, ensuring that even the smallest traces of cancer are not missed after initial therapy.

Key benefits of sequential ctDNA analysis:

  • Non-invasive and repeatable—ideal for continuous monitoring
  • Detects recurrence earlier than imaging or conventional biomarkers
  • Enables personalized oncology surveillance programs
  • Supports precision medicine approaches for each patient

What are the most effective cancer monitoring strategies today?

Cancer monitoring strategies have evolved rapidly in the last decade, moving from static imaging-based protocols to dynamic, biology-driven approaches like sequential ctDNA analysis. The most effective strategies combine:

  1. Regular clinical assessments and physical examinations
  2. Advanced imaging (MRI, PET-CT, etc.) when indicated
  3. Biomarker surveillance, including ctDNA and protein markers
  4. Personalized oncology surveillance programs tailored to each patient’s risk profile and cancer subtype

Comparison of traditional vs. modern cancer monitoring strategies

Strategy Advantages Limitations
Imaging (CT, MRI) Visualizes structural changes
Widely available
May miss microscopic disease
Involves radiation exposure
Protein Biomarkers Simple blood tests
Useful in some cancers
Limited sensitivity/specificity
Not available for all cancer types
Sequential ctDNA Analysis Highly sensitive & specific
Detects recurrence earlier
Non-invasive
Requires specialized technology
Interpretation requires expert knowledge

How do oncology surveillance programs enhance patient outcomes?

Oncology surveillance programs are structured, evidence-based follow-up plans designed to:

  • Ensure timely detection of recurrence or metastasis
  • Facilitate early intervention and tailored therapy
  • Provide psychological support and education to patients and families
  • Integrate the latest advances, such as sequential ctDNA analysis, into routine care

With Dr Mathangi’s leadership at Gleneagles Cancer Institute, patients in Bangalore and from across India benefit from world-class oncology surveillance programs that adhere to international best practices, yet are customized for the unique needs of Indian patients. Her programs emphasize multidisciplinary collaboration, patient empowerment, and the judicious use of cutting-edge technologies for MRD follow-up and beyond.

What is the role of MRD follow-up in long-term cancer management?

MRD follow-up—the monitoring of minimal residual disease—plays a vital role in long-term cancer management by:

  • Detecting microscopic cancer cells that survive initial therapy
  • Predicting the likelihood of recurrence with high accuracy
  • Guiding decisions about additional treatment or maintenance therapy
  • Reassuring patients when no MRD is detected, potentially allowing for reduced surveillance frequency

Sequential ctDNA analysis has emerged as the gold standard for MRD follow-up in various solid tumors, providing actionable data that can directly impact survival outcomes. Dr Mathangi’s expertise ensures that MRD follow-up is seamlessly integrated into each patient’s care plan, maximizing the chances of long-term remission and peace of mind.

Why choose Dr Mathangi for high-risk cancer surveillance in India?

Entrusting your care to Dr Mathangi means choosing one of India’s most experienced and respected radiation oncologists for your high-risk cancer surveillance. Her credentials include:

  • Over 20 years of clinical experience and more than 12,000 patients treated
  • Leadership at Gleneagles Cancer Institute, a premier cancer care center in Bangalore
  • Expertise in advanced radiation oncology techniques (SRS, SBRT, IGRT, RapidArc, Interstitial Brachytherapy)
  • Pioneering the use of sequential ctDNA analysis in routine surveillance for Indian patients
  • A holistic, patient-first approach backed by international training and recognition
Don’t miss out on the opportunity for the most advanced, proactive cancer care available in India.
To book a high-risk cancer surveillance consultation with Dr Mathangi, submit your contact information here and her team will reach out to schedule your appointment.

Key cancers that benefit from advanced surveillance

  • Head and neck cancers
  • Brain tumors
  • Spine tumors
  • Esophagus and rectal cancers
  • Lung cancers
  • Liver cancers
  • Breast cancers
  • Bladder cancers
  • Prostate cancers
  • Uterine cancers
  • Cervical cancer
  • Vulval cancers
  • Anal canal cancers
  • Penile cancers

For these high-risk cancer types, sequential ctDNA analysis and structured oncology surveillance programs can make all the difference—delivering peace of mind and the promise of a healthier future.

About Dr Mathangi

Dr Mathangi J is a Senior Consultant & In-charge of Radiation Oncology at Gleneagles Cancer Institute in Bangalore. With MBBS, DMRT, and DNB qualifications and elite training in Stereotactic Radiotherapy, IGRT, RapidArc, and Intraoperative Radiotherapy from international centers, she is recognized as a pioneer in cancer care in India. Renowned for her patient-centric approach, Dr Mathangi’s expertise covers a broad spectrum of adult cancers, notably those requiring advanced radiation therapy. She is also the Director of the Fellowship in Advanced Radiotherapy techniques at RGUHS and led the installation of Asia Pacific's first TrueBeam STx Machine.

Her mission: To empower every cancer patient with access to world-class, personalized, and proactive cancer monitoring strategies—setting new benchmarks in high-risk cancer surveillance for India and beyond.

Frequently Asked Questions

What is high-risk cancer surveillance and who should consider it?

High-risk cancer surveillance is a proactive approach to closely monitor individuals with an elevated risk of developing cancer or experiencing recurrence. This includes those with a strong family history, known genetic mutations, or previous cancer diagnoses. Dr. Mathangi offers tailored oncology surveillance programs to ensure early detection and timely intervention, improving outcomes in these high-risk populations.

How does sequential ctDNA analysis enhance cancer monitoring strategies?

Sequential ctDNA analysis involves regularly testing blood samples for circulating tumor DNA, which allows for real-time detection of molecular changes associated with cancer. This method provides a highly sensitive and minimally invasive way to monitor disease progression or recurrence, making cancer monitoring strategies more dynamic and precise under Dr. Mathangi’s guidance.

What role does ctDNA play in MRD follow-up after treatment?

ctDNA is a valuable biomarker for minimal residual disease (MRD) follow-up, helping to identify small amounts of cancer that might remain after treatment. By integrating ctDNA testing into follow-up protocols, Dr. Mathangi’s approach enables earlier intervention in case of recurrence, ensuring patients receive the most appropriate care as soon as possible.

How is sequential ctDNA monitoring integrated into oncology surveillance programs?

Dr. Mathangi incorporates sequential ctDNA monitoring as a core component of her comprehensive oncology surveillance programs. By scheduling regular ctDNA tests, her team can track changes and detect recurrences much earlier than traditional imaging alone. This integration improves personalized care and allows for timely, data-driven decisions in patient management.

What advantages does sequential ctDNA analysis offer over traditional monitoring?

Sequential ctDNA analysis offers several advantages, including non-invasiveness, high sensitivity, and real-time tracking of tumor genetics. Unlike imaging, it can detect molecular changes before they manifest as physical tumors, allowing Dr. Mathangi to adjust treatment plans swiftly and improve patient outcomes in high-risk cancer surveillance.

How often should ctDNA be monitored for high-risk patients?

The frequency of ctDNA monitoring depends on individual risk factors, cancer type, and stage of treatment. Dr. Mathangi customizes surveillance intervals—sometimes every few months—to ensure optimal detection of recurrence or progression as part of her cancer monitoring strategies.

What types of cancers benefit most from ctDNA-based surveillance?

ctDNA-based surveillance is beneficial in a range of solid tumors, including breast, colorectal, lung, and ovarian cancers, especially in the context of high-risk cancer surveillance. Dr. Mathangi assesses each patient’s unique profile to recommend the most effective monitoring approach.

How does Dr. Mathangi personalize cancer monitoring strategies for her patients?

Dr. Mathangi tailors cancer monitoring strategies by considering the patient’s genetic background, cancer type, previous treatments, and risk profile. She uses advanced tools like sequential ctDNA analysis and combines them with imaging and clinical assessments to provide a comprehensive, patient-centered surveillance plan.

What should patients expect when enrolling in Dr. Mathangi’s surveillance programs?

Patients enrolling in Dr. Mathangi’s oncology surveillance programs can expect regular assessments, which may include sequential ctDNA analysis, imaging studies, and personalized consultations. The process is designed to be minimally invasive, data-driven, and focused on early detection and prevention, providing peace of mind and proactive care.


How Liquid Biopsy Helps Detect Cancer Recurrence Before Scans

By Dr Mathangi J, Senior Consultant & In-charge - Radiation Oncology, Gleneagles Cancer Institute, Bangalore

What Is Early Cancer Recurrence Detection And How Does Liquid Biopsy Help?

Early cancer recurrence detection refers to identifying the return of cancer cells in the body before they become visible on traditional imaging scans. According to recent studies, up to 30% of patients experience cancer recurrence within five years of successful primary treatment, and most recurrences are detected at advanced stages when treatment options are limited.1 Liquid biopsy is revolutionizing how oncologists like Dr Mathangi can detect these recurrences much earlier than scans, offering patients a vital head start in their fight against cancer.

  • Liquid biopsy analyzes blood samples to detect traces of cancer DNA, called circulating tumor DNA (ctDNA).
  • This technique enables real-time, non-invasive early cancer recurrence detection and offers actionable insights before tumors reappear on CT or MRI scans.
  • Dr Mathangi J at Gleneagles Cancer Institute uses this cutting-edge approach as part of her advanced cancer management protocol in Bangalore.

Why Is Early Detection Of Cancer Recurrence So Critical?

Early detection is key to improving cancer survival rates. Most relapses are caught late—often after symptoms develop or visible changes are seen on scans. By then, the cancer may have spread or become more aggressive, reducing the chances of successful treatment.

Liquid biopsy bridges this gap. By detecting minute genetic changes in blood, it enables oncologists to intervene up to 6–12 months before standard imaging detects a recurrence. This time advantage can mean less aggressive treatments, improved quality of life, and better long-term outcomes.

How Does CtDNA Recurrence Test Work?

The ctDNA recurrence test is a form of liquid biopsy that identifies fragments of DNA shed by cancer cells into the bloodstream. This test is highly sensitive, capable of detecting even tiny amounts of tumor DNA that indicate the earliest stages of relapse.

  • Blood draw: A simple blood sample is collected from the patient.
  • DNA analysis: The sample is analyzed in a specialized laboratory for specific genetic mutations or alterations associated with the patient’s cancer.
  • Result interpretation: If ctDNA is detected, it signals the potential return of cancer, even before imaging can reveal a tumor.

Dr Mathangi incorporates the ctDNA recurrence test into her cancer relapse monitoring protocol, ensuring her patients receive the most advanced and timely care possible.

What Makes Liquid Biopsy An Advanced Cancer Diagnostics Tool?

Liquid biopsy represents a leap forward in advanced cancer diagnostics. Unlike traditional biopsies, which require removing tissue directly from the tumor (often through invasive procedures), liquid biopsy is non-invasive, repeatable, and offers a window into the real-time behavior of cancer cells throughout the body.

Advantages Over Traditional Scans

  • Earlier detection: Finds recurrence months before imaging scans.
  • Less invasive: No surgical procedures are needed.
  • Dynamic monitoring: Tracks cancer evolution and treatment response over time.
  • Broader coverage: Detects changes in hard-to-scan areas (e.g., bone, brain, lymph nodes).
  • Personalized care: Identifies specific genetic mutations for targeted therapies.

At Gleneagles Cancer Institute, Dr Mathangi’s expertise in advanced cancer diagnostics ensures that patients have access to these groundbreaking technologies, leading to earlier interventions and tailored treatment strategies.

How Does Cancer Relapse Monitoring Benefit From Liquid Biopsy?

Cancer relapse monitoring is a continuous process that tracks patients after their initial treatment to catch any signs of returning disease. Traditionally, this has relied on scheduled scans and clinical symptoms, which may miss very early microscopic recurrences.

Liquid biopsy transforms this process by enabling:

  1. Proactive intervention: Oncologists can adjust treatment plans before symptoms or scan abnormalities appear.
  2. Reduced unnecessary treatment: Avoids overtreatment in patients with no molecular evidence of disease.
  3. Peace of mind: Patients benefit from the reassurance that their care team, led by Dr Mathangi, is monitoring for hidden threats with the latest technology.

This approach is especially beneficial for cancers that need RT (radiation therapy), including head and neck cancers, brain tumors, spine tumors, esophagus and rectal cancers, lung cancers, liver cancers, breast cancers, bladder cancers, prostate cancers, uterine cancers, cervical cancer, vulval cancers, anal canal cancers, and penile cancers.

What Is MRD Testing And Why Is It Important?

MRD testing stands for Minimal Residual Disease testing. It detects tiny amounts of cancer cells that remain in the body after treatment, which are too small to be seen on scans but can eventually lead to relapse.

  • Early warning: MRD testing, using liquid biopsy, can reveal molecular signs of cancer well before other methods.
  • Risk stratification: Helps identify patients at higher risk of recurrence, enabling more aggressive monitoring or therapy.
  • Better outcomes: Studies show MRD-guided care leads to improved survival and decreased relapse rates.

As part of her commitment to advanced cancer diagnostics, Dr Mathangi integrates MRD testing for select patients, ensuring even the smallest traces of disease are not overlooked.

Who Should Consider Liquid Biopsy For Early Cancer Recurrence Detection?

Patients who have completed primary cancer treatment are at risk for recurrence, particularly those with cancers prone to relapse or with a history of aggressive disease. Liquid biopsy is especially recommended for:

  • Individuals treated for cancers that need RT, including breast, lung, prostate, cervical, head and neck, brain, and colorectal cancers.
  • Patients with difficult-to-monitor tumors or those with a high risk of recurrence.
  • Anyone seeking proactive, personalized follow-up care tailored to their unique genetic and clinical profile.

Under Dr Mathangi’s expert supervision, patients benefit from a comprehensive, evidence-based approach to recurrence surveillance.

Why Choose Dr Mathangi For Advanced Cancer Diagnostics In Bangalore?

Dr Mathangi J is a leading authority in radiation oncology, with over 20 years of clinical experience and more than 12,000 patients successfully treated. As the Senior Consultant and In-charge at Gleneagles Cancer Institute, Bangalore, she specializes in integrating the latest diagnostic and therapeutic advances for optimal cancer care.

  • Extensively trained in advanced radiation techniques from renowned global institutions.
  • Pioneered the installation of Asia Pacific’s first TrueBeam STx Machine.
  • Director of Fellowship in Advanced Radiotherapy techniques affiliated with RGUHS.

Her unique expertise, combined with a compassionate, patient-centric approach, ensures every individual receives state-of-the-art care—including liquid biopsy, ctDNA recurrence test, and MRD testing for early cancer recurrence detection.

How To Book A Liquid Biopsy Assessment With Dr Mathangi

Don’t wait for cancer to return before taking action. If you or a loved one has completed cancer treatment, now is the time for proactive surveillance.

  1. Visit https://drmathangi.com/contact/
  2. Fill in your contact information.
  3. Dr Mathangi’s team will schedule your appointment and notify you promptly.

Secure your future health with the most advanced tools for early cancer recurrence detection in Bangalore, guided by one of India’s foremost cancer specialists.

About Dr Mathangi J

Dr Mathangi J is a highly respected Senior Radiation Oncologist and In-Charge of the Gleneagles Cancer Institute, Bangalore—a leading center for comprehensive cancer care in India. With international training and a proven record in advanced oncology techniques, she is dedicated to delivering personalized, evidence-based care for patients with head and neck cancers, brain tumors, spine tumors, esophagus and rectal cancers, lung cancers, liver cancers, breast cancers, bladder cancers, prostate cancers, uterine cancers, cervical cancer, vulval cancers, anal canal cancers, and penile cancers.

To experience the benefits of liquid biopsy and ensure the best possible outcomes for yourself or your loved ones, book a consultation with Dr Mathangi today.

Frequently Asked Questions

What is a liquid biopsy and how does it help with early cancer recurrence detection?

A liquid biopsy is a minimally invasive blood test that detects tiny fragments of cancer DNA, known as circulating tumor DNA (ctDNA), in the bloodstream. This advanced cancer diagnostics tool can identify the return of cancer, or recurrence, much earlier than traditional imaging scans. By catching signs of recurrence early, patients and their doctors, like Dr. Mathangi, can make timely decisions about treatment adjustments and follow-up care.

How does a ctDNA recurrence test work for cancer relapse monitoring?

A ctDNA recurrence test analyzes a blood sample to look for genetic material released by cancer cells. These tests are highly sensitive and can detect molecular signs of cancer relapse even before symptoms or changes appear on scans. For patients under Dr. Mathangi’s care, ctDNA testing becomes a valuable part of ongoing cancer relapse monitoring, enabling proactive management.

Why is liquid biopsy more effective than scans alone for monitoring cancer recurrence?

Scans can only detect tumors once they reach a certain size, but a liquid biopsy can reveal molecular evidence of recurrence much earlier. This means that with tools like MRD testing (Minimal Residual Disease testing), patients get a crucial head start, often detecting recurrence months before a scan would show any abnormality. Dr. Mathangi uses this approach to ensure that any signs of relapse are addressed immediately.

What is MRD testing and how does it relate to liquid biopsy?

MRD testing stands for Minimal Residual Disease testing. It’s a highly sensitive technique, often performed using liquid biopsy, to detect trace amounts of cancer cells that remain in the body after treatment. MRD testing can help determine how effective treatment has been and whether there are signs of recurrence at a stage too early for imaging to detect. Dr. Mathangi incorporates MRD testing into her follow-up protocols for personalized and precise care.

How often should cancer survivors have liquid biopsy or ctDNA testing?

The frequency of liquid biopsy or ctDNA recurrence test depends on the type of cancer, risk of recurrence, and individual patient factors. Dr. Mathangi customizes a surveillance plan for each patient, which may include periodic liquid biopsies at regular intervals for optimal early cancer recurrence detection and cancer relapse monitoring.

Can liquid biopsy replace traditional scans for all cancer patients?

While liquid biopsy is a powerful tool for advanced cancer diagnostics, it is usually used in combination with imaging scans rather than as a complete replacement. Dr. Mathangi recommends integrating liquid biopsy with other monitoring methods to achieve the most accurate and comprehensive picture of a patient’s health.

How does Dr. Mathangi utilize liquid biopsy in her practice?

Dr. Mathangi offers advanced cancer diagnostics, including liquid biopsy, to patients at risk of recurrence. She tailors testing schedules and interprets ctDNA and MRD results alongside clinical findings, ensuring early intervention and the best possible outcomes for patients. Her expertise ensures that each patient receives individualized follow-up using cutting-edge technology.

What are the benefits of early cancer recurrence detection for survivors?

Early cancer recurrence detection allows for prompt intervention, which can improve treatment effectiveness and outcomes. By identifying relapse at the molecular level before physical symptoms arise, patients have more options and a better chance at long-term remission. Liquid biopsy, ctDNA testing, and MRD testing are all vital components of Dr. Mathangi’s approach to proactive survivorship care.


Lymphoma vs Leukemia: Key Differences Explained


Blood cancers account for nearly 10% of all cancer diagnoses worldwide, making the topic of leukemia vs lymphoma more critical than ever for early detection and effective treatment. Yet, many patients remain confused about how these two major blood cancer types differ—and that confusion can delay life-saving care.

At the forefront of advanced cancer treatment, Dr Mathangi, Senior Consultant and In-charge of Radiation Oncology at Gleneagles Cancer Institute, Bangalore, brings over two decades of expertise and more than 12,000 successfully treated cases. Her approach combines precision, advanced radiotherapy technologies, and deeply personalized care—ensuring that patients receive not just treatment, but the right treatment at the right time.

What is leukemia vs lymphoma?

Leukemia vs lymphoma refers to a cancer comparison between two major categories of hematologic malignancies. Leukemia originates in the bone marrow and affects blood-forming cells, while lymphoma begins in the lymphatic system, impacting immune function and lymph nodes.

Understanding this distinction is crucial because although both fall under blood cancer types, their behavior, symptoms, and treatment approaches differ significantly. Ignoring these differences can lead to delayed diagnosis, incorrect assumptions, and missed opportunities for early intervention.

What are blood cancer types and where do these fit?

Blood cancer types broadly include leukemia, lymphoma, and myeloma. Among these, leukemia and lymphatic cancer (lymphoma) are the most commonly discussed due to their prevalence and overlapping symptoms.

  • Leukemia: Affects blood and bone marrow
  • Lymphoma: Affects lymph nodes and lymphatic system
  • Myeloma: Affects plasma cells

This classification helps clinicians like Dr Mathangi tailor treatment strategies based on disease origin and progression patterns.

How does lymphoma differ from leukemia in origin?

The key difference in leukemia vs lymphoma lies in where the cancer starts. Leukemia begins in the bone marrow, leading to abnormal white blood cell production. In contrast, lymphatic cancer originates in the lymphatic system, affecting lymph nodes, spleen, and immune pathways.

In rare cases, patients may even encounter complex presentations such as llymphoma, highlighting the importance of expert diagnosis and precise classification.

What are the symptoms of leukemia vs lymphoma?

Symptoms often overlap, which is why professional evaluation is essential. However, there are distinguishing signs that can guide early suspicion.

Common leukemia symptoms

  • Frequent infections
  • Fatigue and weakness
  • Easy bruising or bleeding
  • Bone pain

Common lymphoma symptoms

  • Swollen lymph nodes
  • Night sweats
  • Unexplained weight loss
  • Persistent fever

Because these symptoms can be subtle or mistaken for other conditions, early consultation with a specialist like Dr Mathangi becomes critical.

How is chronic lymphocytic leukemia icd 10 classified?

Chronic lymphocytic leukemia icd 10 falls under a specific medical classification system used globally for diagnosis and treatment planning. It represents a slow-growing leukemia that primarily affects older adults and requires careful monitoring and personalized therapy.

Accurate classification ensures that patients receive the most appropriate care pathway—something that Dr Mathangi emphasizes through advanced diagnostic protocols.

What diagnostic tests differentiate leukemia and lymphoma?

A precise cancer comparison requires a combination of advanced diagnostic tools:

  • Blood tests and complete blood count (CBC)
  • Bone marrow biopsy
  • Lymph node biopsy
  • Imaging (CT, PET scans)
  • Molecular and genetic testing

At Gleneagles Cancer Institute, these diagnostics are integrated seamlessly to ensure no delay in treatment initiation.

How are hematologic malignancies treated?

Treatment varies depending on whether the diagnosis is leukemia or lymphoma. However, modern oncology has evolved to offer highly targeted and effective solutions.

Dr Mathangi specializes in advanced radiation oncology techniques including:

  • Stereotactic ablative body radiotherapy (SBRT)
  • Gated RapidArc technology
  • DIBH gated Radiotherapy
  • Image-guided interstitial brachytherapy

These technologies allow for:

  • Higher precision targeting of cancer cells
  • Reduced damage to surrounding healthy tissues
  • Shorter treatment durations
  • Improved patient outcomes

Why early cancer comparison matters for survival?

One of the biggest problems patients face is delaying medical consultation due to confusion around leukemia vs lymphoma. This delay can allow cancer to progress silently.

The reality is:

  • Early-stage detection dramatically improves survival rates
  • Advanced treatment options are more effective when started early
  • Personalized therapy becomes more precise with early diagnosis

This is where choosing the right oncologist becomes a decisive factor.

What cancers can be treated with radiation therapy?

Radiation therapy plays a vital role in treating multiple cancers, including:

  • Head and neck cancers
  • Brain tumors
  • Spine tumors
  • Esophagus and rectal cancers
  • Lung cancers
  • Liver cancers
  • Breast cancers
  • Bladder cancers
  • Prostate cancers
  • Uterine cancers
  • Cervical cancer
  • Vulval cancers
  • Anal canal cancers
  • Penile cancers

Dr Mathangi’s expertise ensures that radiation therapy is not just administered—but optimized for each individual patient.

Why choose Dr Mathangi for lymphoma and leukemia care?

Dr Mathangi is a Senior Radiation Oncologist based in Bangalore, specializing in advanced cancer care with a focus on precision radiotherapy. With international training from Germany and Denmark, and leadership at Gleneagles Cancer Institute, she offers unmatched expertise in treating complex hematologic malignancies.

Her achievements include installing the Asia Pacific’s first TrueBeam STx Machine—bringing world-class technology closer to patients in India.

Patients who delay choosing the right specialist often miss out on:

  • Access to advanced technologies
  • Personalized treatment planning
  • Better survival outcomes
  • Comprehensive care coordination

This is not just treatment—it is an opportunity to take control of your health before the disease progresses further.

How to book an appointment with Dr Mathangi?

Taking the first step toward accurate diagnosis and effective treatment is simple. Patients can submit their details through the official contact form:

https://drmathangi.com/contact/

Once submitted, her team will promptly schedule an appointment and guide you through the next steps.

About Dr Mathangi

Dr Mathangi J is a Senior Consultant and In-charge of Radiation Oncology with over 20 years of experience. She has successfully treated more than 12,000 patients and is recognized for her expertise in cutting-edge radiotherapy techniques.

She completed her MBBS, DMRT, and DNB, with advanced international training in SRS/SBRT, IGRT, RapidArc, and intraoperative radiotherapy. She currently heads the radiation oncology department and serves as Director of Fellowship in Advanced Radiotherapy techniques.

Her specialization includes:

  • Head and neck cancers
  • Brain tumors
  • Lung cancers
  • Prostate cancers
  • Women cancers (breast, cervix, endometrium)

Her commitment is not just to treat cancer—but to transform outcomes with precision, compassion, and innovation.

Frequently Asked Questions

What is the main difference in leukemia vs lymphoma?

The primary distinction in leukemia vs lymphoma lies in where the cancer originates. Leukemia begins in the bone marrow and affects blood cells, while lymphoma develops in the lymphatic system, particularly lymph nodes. Both are classified under blood cancer types, but their progression, symptoms, and treatment pathways differ significantly.

Is lymphoma considered a type of blood cancer?

Yes, lymphoma is one of the major blood cancer types. It specifically affects the lymphatic system and is often referred to as lymphatic cancer. This condition impacts immune cells called lymphocytes, which play a vital role in fighting infections.

What does chronic lymphocytic leukemia icd 10 mean?

The term chronic lymphocytic leukemia icd 10 refers to the standardized medical classification used for diagnosing and coding this specific type of leukemia. It helps healthcare providers maintain accurate records, streamline insurance processes, and ensure consistent diagnosis across healthcare systems.

How are hematologic malignancies diagnosed?

Hematologic malignancies are diagnosed using a combination of blood tests, bone marrow biopsies, imaging scans, and sometimes lymph node biopsies. Early and accurate diagnosis is crucial for determining whether a patient has leukemia, lymphoma, or another form of cancer.

What symptoms should I watch for in lymphatic cancer?

Common symptoms of lymphatic cancer include swollen lymph nodes, unexplained weight loss, night sweats, fatigue, and persistent fever. Recognizing these early signs can help in timely diagnosis and effective treatment.

How does Dr. Mathangi approach cancer comparison and treatment planning?

Dr. Mathangi uses a comprehensive cancer comparison approach to evaluate each patient’s condition. By carefully distinguishing between leukemia vs lymphoma and other hematologic malignancies, she designs personalized treatment plans that may include chemotherapy, targeted therapy, or immunotherapy based on the patient’s specific diagnosis.

Can lymphoma and leukemia be treated successfully?

Yes, many cases of lymphoma and leukemia can be treated effectively, especially when diagnosed early. Advances in medical science have significantly improved outcomes for patients with various blood cancer types, making long-term remission and even cure possible in some cases.

When should I consult Dr. Mathangi for blood cancer concerns?

If you experience persistent symptoms such as fatigue, abnormal bleeding, or swollen lymph nodes, it is advisable to consult Dr. Mathangi. Early evaluation helps identify conditions like lymphoma or leukemia and ensures timely intervention for better outcomes.


Lymph Nodes and Their Role in Cancer & Immunity

Did you know that the human body contains over 500–700 lymph nodes, acting as critical checkpoints in the body’s defense system? These tiny structures play a massive role in detecting infections, filtering harmful substances, and identifying cancer cells early. Understanding lymph nodes is not just a medical curiosity—it can be life-saving, especially when it comes to early cancer detection and treatment.

Yet, many individuals overlook subtle warning signs such as swelling or tenderness, often missing early indicators of disease progression. This is where expert guidance becomes crucial. Under the care of Dr Mathangi, a highly experienced radiation oncologist with over 20 years of expertise, patients receive not only advanced treatment but also clarity and confidence in navigating complex conditions involving the lymphatic system.

What are lymph nodes and why are they important?

Lymph nodes are small, bean-shaped structures that are part of the lymphatic system, a vital network responsible for maintaining fluid balance and defending the body against infections and diseases, including cancer.

The lymph node function primarily includes:

  • Filtering harmful substances such as bacteria and viruses
  • Producing immune cells like lymphocytes
  • Acting as checkpoints for abnormal or cancerous cells
  • Supporting the immune response lymph nodes activation

When functioning normally, lymph nodes silently protect the body. However, when something goes wrong, they often provide the earliest signals of trouble.

How does the lymphatic system support immunity?

The lymphatic system is a complex network of vessels, tissues, and organs that work alongside the circulatory system. It transports lymph—a fluid rich in infection-fighting white blood cells—throughout the body.

Key roles include:

  • Removing toxins and waste products
  • Transporting immune cells to areas of infection
  • Helping the body recognize and attack foreign invaders
  • Activating immune response lymph nodes during infections

This system acts as a surveillance network, ensuring that harmful agents are quickly detected and neutralized. When compromised, the body becomes more vulnerable to infections and malignancies.

What are common lymph node swelling causes?

Lymph node swelling causes can range from mild infections to serious underlying conditions such as cancer. Swelling is often a sign that the immune system is actively responding to a threat.

Common causes include:

  • Viral infections like the common cold
  • Bacterial infections such as tuberculosis
  • Autoimmune diseases
  • Cancer, particularly involving metastasis lymph nodes

Persistent swelling, especially when painless and progressive, should never be ignored. Early evaluation by a specialist like Dr Mathangi can make a significant difference in diagnosis and outcomes.

How does cancer spread through lymph nodes?

Cancer spread lymph nodes occurs when cancer cells break away from the primary tumor and travel through the lymphatic system. These cells can lodge in nearby lymph nodes and begin to grow, a process known as metastasis lymph nodes.

This spread is critical in determining:

  • The stage of cancer
  • The aggressiveness of the disease
  • The most effective treatment plan

For example, cancers such as breast cancer, lung cancer, and head and neck cancers often involve lymph nodes during progression. Identifying this spread early allows for targeted therapies that improve survival rates.

Why is early detection of lymph node involvement crucial?

Detecting cancer in lymph nodes early can significantly improve treatment outcomes. When caught early, cancer is more localized and easier to treat with advanced therapies such as radiation.

Delaying diagnosis can lead to:

  • Advanced metastasis lymph nodes involvement
  • Reduced treatment effectiveness
  • Increased risk of complications

This is where the expertise of Dr Mathangi becomes invaluable. With access to cutting-edge technologies such as SBRT, IGRT, and RapidArc, she ensures precise targeting of affected areas while preserving healthy tissues.

What cancers commonly involve lymph nodes?

Several cancers are known to spread through lymph nodes, making their evaluation essential in cancer management.

  • Head and neck cancers
  • Brain tumors
  • Spine tumors
  • Esophagus and rectal cancers
  • Lung cancers
  • Liver cancers
  • Breast cancers
  • Bladder cancers
  • Prostate cancers
  • Uterine cancers
  • Cervical cancer
  • Vulval cancers
  • Anal canal cancers
  • Penile cancers

Each of these cancers requires a tailored approach, especially when lymph nodes are involved. Dr Mathangi’s experience with over 12,000 patients ensures that each treatment plan is personalized and precise.

How are lymph node-related cancers treated?

Treatment depends on the type and stage of cancer, particularly the extent of cancer spread lymph nodes.

Common treatment approaches include:

  • Radiation therapy targeting affected lymph nodes
  • Stereotactic techniques (SRS/SBRT) for precision treatment
  • Image-guided therapies for accurate delivery
  • Combination therapies including surgery and chemotherapy

Dr Mathangi specializes in advanced radiation techniques such as:

  • Stereotactic ablative body radiotherapy (SBRT)
  • Gated RapidArc
  • DIBH gated Radiotherapy
  • Image-guided Interstitial Brachytherapy

These innovations allow for highly effective treatment with minimal side effects, giving patients a better quality of life during and after therapy.

Why choose Dr Mathangi for lymph node and cancer treatment?

Dr Mathangi is a Senior Radiation Oncologist and In-charge of Gleneagles Cancer Institute in Bangalore, known for delivering advanced and comprehensive cancer care. With international training and decades of experience, she stands at the forefront of modern oncology.

Patients under her care benefit from:

  • Evidence-based treatment protocols
  • Access to state-of-the-art technology
  • Personalized care plans
  • A compassionate, patient-centric approach

Choosing the right specialist is not just a decision—it is a turning point. Missing the opportunity to receive expert care at the right time can impact outcomes significantly.

When should you consult a specialist?

You should seek medical advice if you notice:

  • Persistent lymph node swelling causes without infection
  • Unexplained weight loss
  • Chronic fatigue
  • Pain or discomfort in lymph node regions

Early consultation can help identify whether the issue is benign or related to metastasis lymph nodes, ensuring timely intervention.

Take the next step toward better health

Ignoring early signs can lead to delayed diagnosis and limited treatment options. On the other hand, taking action today can open the door to advanced care, improved outcomes, and peace of mind.

To book an appointment with Dr Mathangi, visit: https://drmathangi.com/contact/

Once you submit your contact details, her team will promptly schedule your consultation and guide you through the next steps.

About Dr Mathangi

Dr Mathangi J is a Senior Consultant and In-charge of Radiation Oncology with over 20 years of experience. She leads the radiation oncology department at Gleneagles Cancer Institute, Bangalore, and serves as Director of Fellowship in Advanced Radiotherapy techniques affiliated with RGUHS.

Her international training includes advanced techniques from Germany and Denmark, and she is credited with installing the Asia Pacific’s first TrueBeam STx Machine. Her expertise spans multiple cancers, including head and neck, lung, prostate, brain, and women cancers.

With a track record of over 12,000 successfully treated patients, Dr Mathangi represents a blend of precision, innovation, and compassionate care—making her one of the most trusted names in oncology today.

Frequently Asked Questions

What are lymph nodes and why are they important?

lymph nodes are small, bean-shaped structures that play a critical role in the lymphatic system. They act as filters, trapping bacteria, viruses, and abnormal cells. Dr. Mathangi explains that these nodes are essential checkpoints where the body identifies threats and activates defense mechanisms to maintain overall health.

What is lymph node function in the body?

lymph node function includes filtering lymph fluid, producing immune cells, and helping the body fight infections. Under Dr. Mathangi’s care, patients receive detailed evaluations to ensure these functions are working optimally, especially when symptoms suggest abnormalities.

How does the lymphatic system support immunity?

The lymphatic system is a network of vessels and organs that transports lymph fluid and supports immune defense. It works closely with lymph nodes to identify harmful substances and trigger immune responses. Dr. Mathangi emphasizes early detection of any disruptions in this system for better long-term health outcomes.

What does cancer spread lymph nodes mean?

cancer spread lymph nodes refers to the movement of cancer cells from the primary tumor into nearby lymph nodes. This is often an early sign that cancer may be progressing. Dr. Mathangi uses advanced diagnostic approaches to assess this spread and guide personalized treatment strategies.

What are common lymph node swelling causes?

lymph node swelling causes can range from infections and inflammation to more serious conditions like cancer. Dr. Mathangi carefully evaluates swelling patterns, duration, and associated symptoms to determine the underlying cause and recommend appropriate care.

How do immune response lymph nodes work during infections?

immune response lymph nodes become active when the body detects infection. They produce and release white blood cells to fight pathogens, often causing temporary swelling. Dr. Mathangi monitors these responses to distinguish between normal immune activity and concerning signs.

What is metastasis lymph nodes and why is it significant?

metastasis lymph nodes refers to the spread of cancer cells into the lymph nodes from another part of the body. This is a key factor in cancer staging and treatment planning. Dr. Mathangi provides comprehensive assessments to detect metastasis early and improve treatment outcomes.

When should I consult Dr. Mathangi for lymph node concerns?

You should consult Dr. Mathangi if you notice persistent swelling, unexplained pain, or changes in lymph nodes. Early consultation helps in identifying issues related to the lymphatic system, immune disorders, or potential cancer risks, ensuring timely and effective care.


Oncology Explained: Definition, Branches, and Treatment Scope

Chat